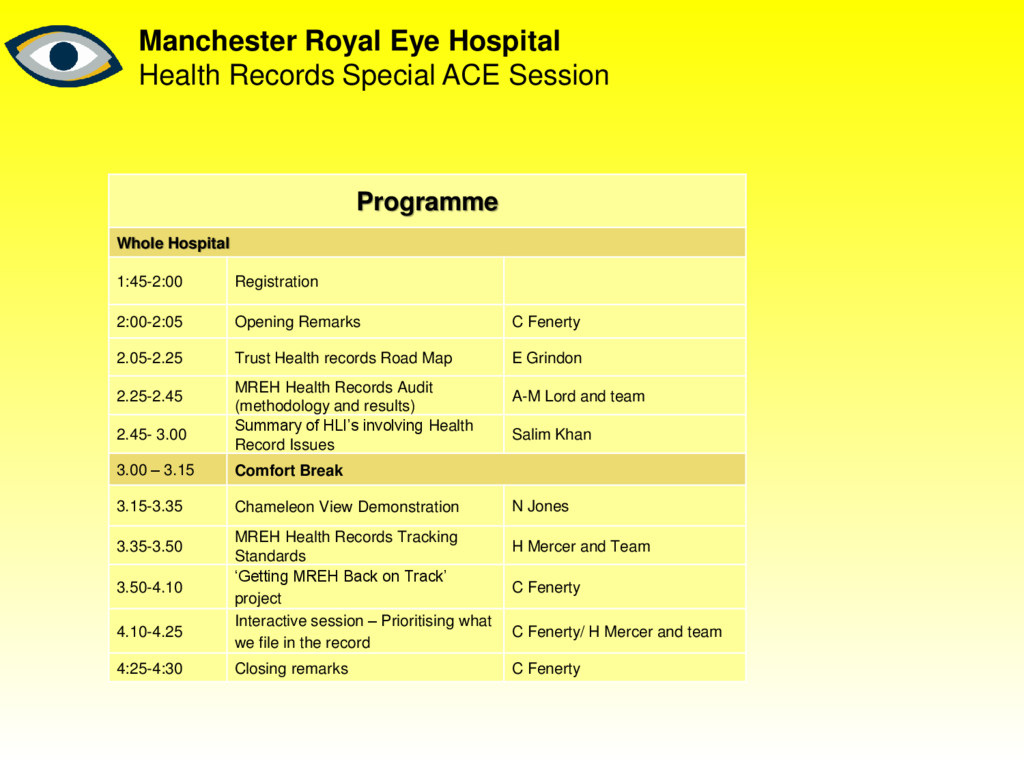
Whole Hospital 1:45-2:00 Registration 2:00-2:05 Opening Remarks C Fenerty 2.05-2.25 Trust Health records Road Map E Grindon 2.25-2.45 MREH Health Records Audit (methodology and results) A-M Lord and team 2.45- 3.00 Summary of HLI’s involving Health Record Issues Salim Khan 3.00 – 3.15 Comfort Break 3.15-3.35 Chameleon View Demonstration N Jones 3.35-3.50 MREH Health Records Tracking Standards H Mercer and Team 3.50-4.10 ‘Getting MREH Back on Track’ project C Fenerty 4.10-4.25 Interactive session – Prioritising what we file in the record C Fenerty/ H Mercer and team 4:25-4:30 Closing remarks C Fenerty
of all areas of Informatics. This review found the following issues relating to Health Records: – Lack of space for filing case notes – Tracking of case notes is poor – Destruction / retention review of case notes is not routinely completed (caused by poor reporting and resource issues) – Use of archive storage is not efficient – Availability of case notes can be low – Inefficiencies in the team – Low team morale
to the right person in the right place at the right time, whether that be paper or electronic • Improve the management of the Library and storage of health records • Reduce costs associated with the storage and administration of paper health records • Adherence to the standards for the management and storage of health records • Ensure actions taken as part of the Health Records Improvement Programme support the upcoming strategy for implementation of a Trust-wide EPR
Health Records Team and a small number of other teams (for example A&E, Maternity, Genetics) • Introduce bar code tracking of case notes using PAS • New case notes created will use the district number as case note number – M format case note numbers will no longer be used • Re-file the library in Terminal Digit File order • Review the management of the Library and use of the space (Gorton 1, Gorton 2, 3rd Floor RMCH, Archive Storage) • Update Processes and SOP’s based on any changes arising from the above activities • Review EDMS options and produce a Business Case
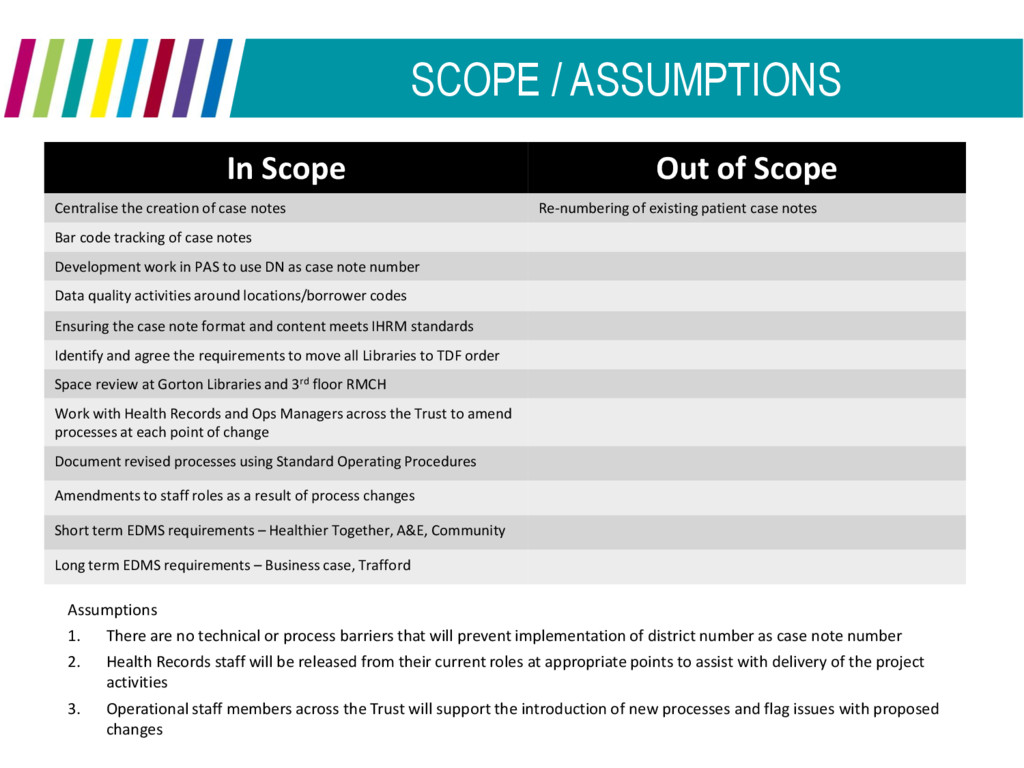
creation of case notes Re-numbering of existing patient case notes Bar code tracking of case notes Development work in PAS to use DN as case note number Data quality activities around locations/borrower codes Ensuring the case note format and content meets IHRM standards Identify and agree the requirements to move all Libraries to TDF order Space review at Gorton Libraries and 3rd floor RMCH Work with Health Records and Ops Managers across the Trust to amend processes at each point of change Document revised processes using Standard Operating Procedures Amendments to staff roles as a result of process changes Short term EDMS requirements – Healthier Together, A&E, Community Long term EDMS requirements – Business case, Trafford Assumptions 1. There are no technical or process barriers that will prevent implementation of district number as case note number 2. Health Records staff will be released from their current roles at appropriate points to assist with delivery of the project activities 3. Operational staff members across the Trust will support the introduction of new processes and flag issues with proposed changes
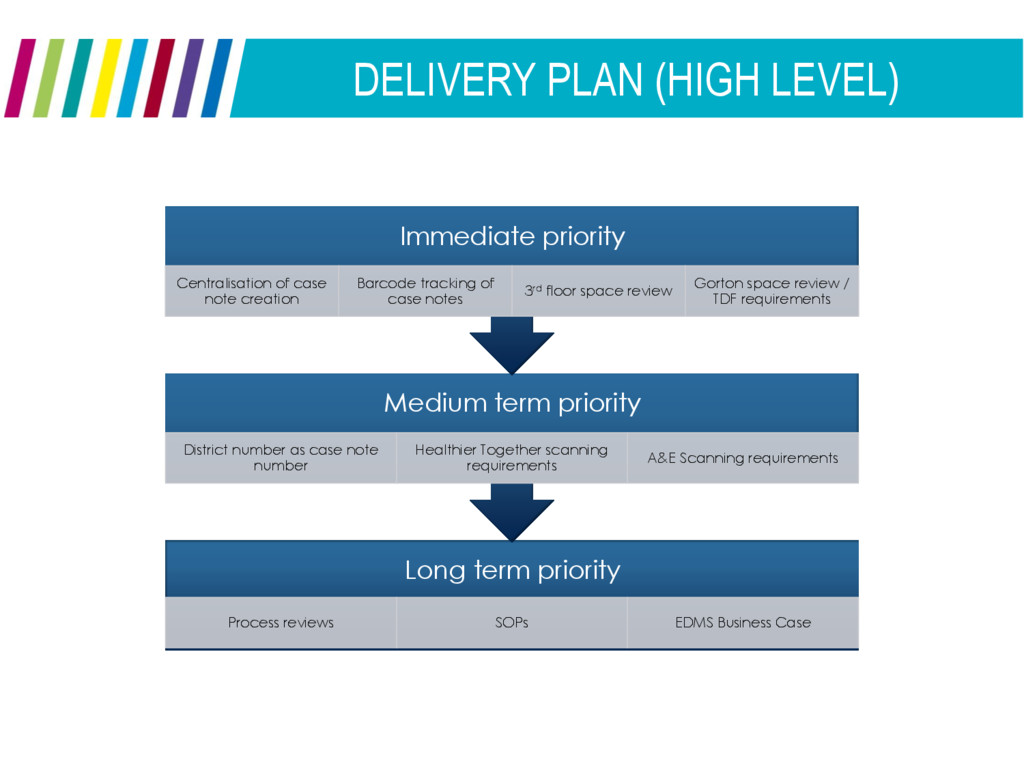
EDMS Business Case Medium term priority District number as case note number Healthier Together scanning requirements A&E Scanning requirements Immediate priority Centralisation of case note creation Barcode tracking of case notes 3rd floor space review Gorton space review / TDF requirements
ISB in Nov 16 Key knowledge people • Ben Dearden / Health Records Team • Ops Managers Next steps • Complete business case for sign off FINANCES / FUNDING (HIGH LEVEL)
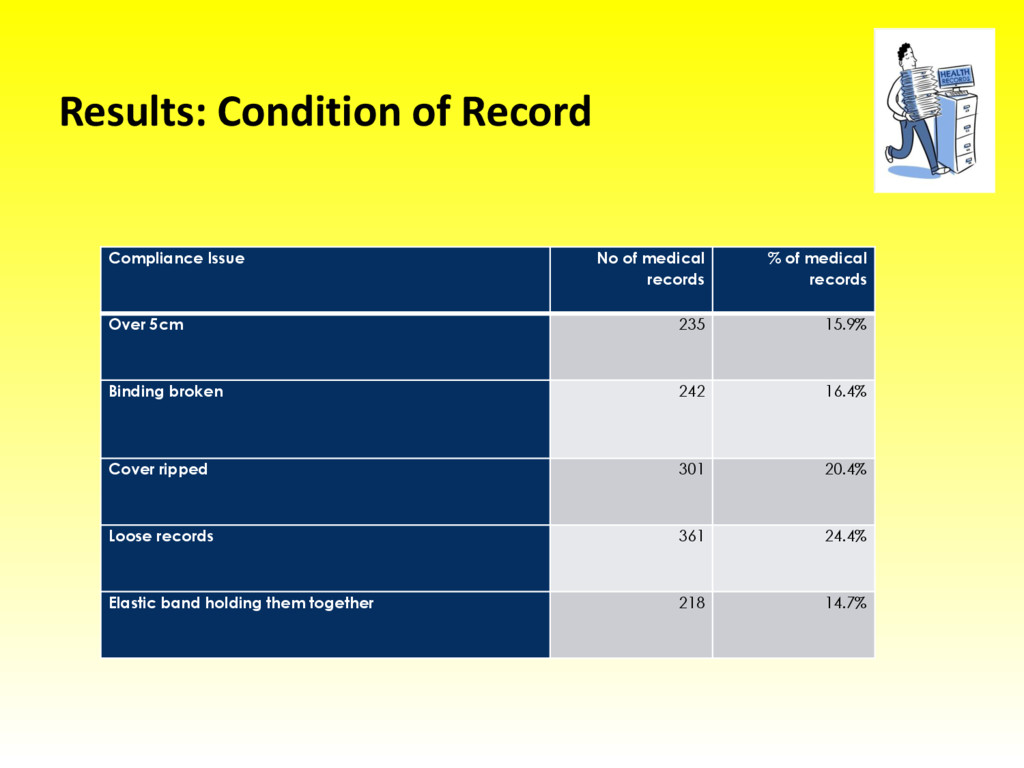
a label was attached to a proforma and a binary assessment made on: (i) the availability of the record (ii) the quality of the record using the following Trust stipulations: • Over 5cm • Binding broken • Cover ripped • Loose records • Elastic band holding them together Methodology
% of medical records Over 5cm 235 15.9% Binding broken 242 16.4% Cover ripped 301 20.4% Loose records 361 24.4% Elastic band holding them together 218 14.7%
5 • Severity • Moderate = 2 • Major = 3 • Actual Impact • No Harm = 3 • Moderate = 1 • Major = 1 • Main Cause • Missing Records • Poor Condition of Records • Misfiled Records • Stolen / Lost Paperwork • Communication (Failure within team)
Male, Uveitis and Glaucoma team since 2006 • Left Advance Glaucoma • Right Glaucoma Surgery • Incident Detection • Pt attending a Uveitis clinic, noted ↑IOP and ↓VA • No appointment by Glaucoma team for 4 months • VA in only seeing eye deteriorated to NPL
weekly appointments • Review appointment was now more than 3 months overdue • Booked for an urgent appointment with the Glaucoma team which he did not attend • Seen in the Uveitis clinic a month later, still no Glaucoma review, had laser treatment • Reviewed by Glaucoma team next day, VA was PL
available • resulting in gaps of knowledge for the reviewing clinician • clinical information continued to be recorded out of order in the medical record • When temps were merged in the medical record • records were then not able to be filed sequentially • made it more difficult for the reviewing clinician to understand the clinical picture
clinical specialties • failure of communication between clinical and administrative teams • Actions taken following a DNA • were not recorded in the medical record or on PAS
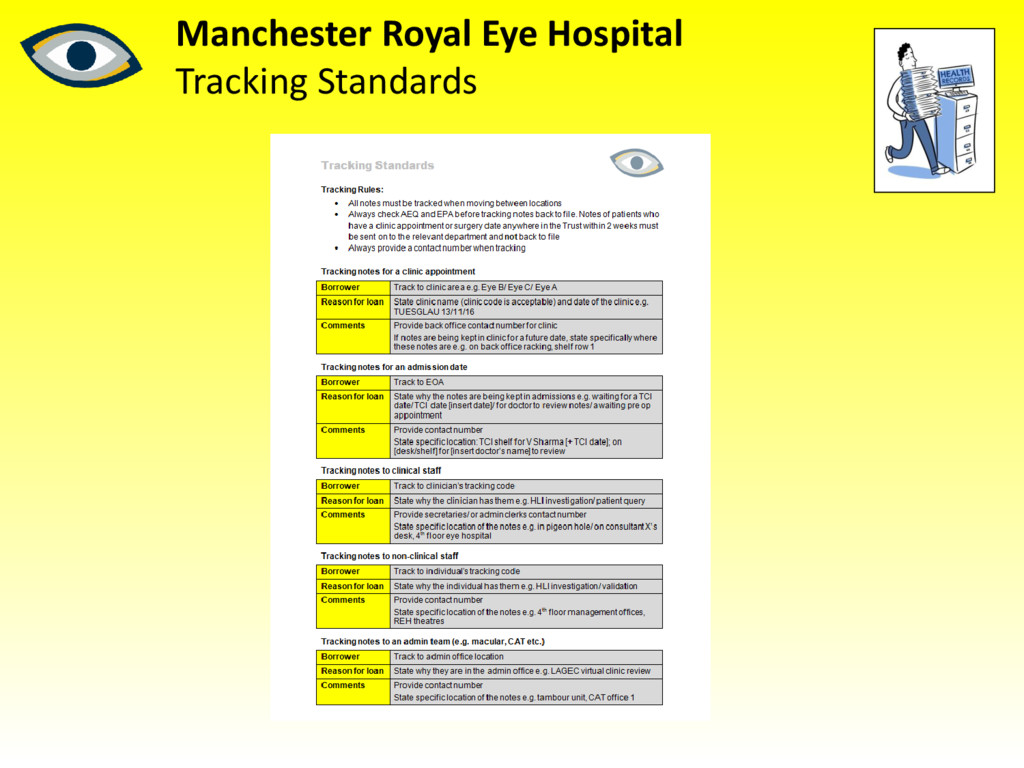
notes must be tracked when moving between locations • Always check AEQ and EPA before tracking notes back to file. Notes of patients who have a clinic appointment or surgery date anywhere in the Trust within 2 weeks must be sent on to the relevant department and not back to file • Always provide a contact number when tracking
CHFE: Cecilia Fenerty • FDSSEC: F D Scala secretary Locations: • EYEH – Eye H, Ground floor OPD • 55 – Ward 55 If you need a borrower code creating – please contact Carol McCormack on 0161 275 6807
have a tracking code • All admin and/or secretarial staff will be happy to track notes for clinicians if asked • Any clinician wishing to have their own access to PAS in order to track to request via Carol McCormack
to: – Your office for chasing results – Admissions to give urgent date for surgery – To Daycase/ward for admission for theatre • Notes passed from one clinician to another as referral or for opinion
• Records held for research • Records held for HLI/medico-legal/complaint/ report • Records required for GP or patient query • Records required for safeguarding • EVERYTHING!
return and filing at Gorton = 1 week • Lead time for record retrieval from Gorton = 1 week – Any records for patients with another episode booked within 2 weeks should have to notes tracked and sent to the next venue
OPA review? – Is patient due to see other subspecialty? – Is patient due for surgery/ pre-op assessment? – Are you sending a letter to a colleague who is likely to want to review the records? • In the ward (esp childrens’ ward) – do the staff know pt is returning soon? • In the office – are there any other imminent episodes on PAS?
to get ‘on track’ • Any records required for an episode within 2 weeks should be tracked and sent to the next venue • Outside clinical areas… • Think about offices, filing cabinets/ staff rooms etc • What records are being held and why? • Any records required for valid reason should be tracked • Any records required elsewhere for an episode within 2 weeks should be tracked and sent to the next venue • Anything not required should be given to a clerk or secretary who can track them back to file
any length of time for any reason can be returned to a member of clerical staff to track back to file • Amnesty cage available on 4th floor reception for any embarrassing finds! – No questions asked!
non-compliant records • Every room in every area will be searched • ‘Clean Areas’ marked • Non-compliant records – Will be tracked back to file – Will be added to log to feed back to individuals if necessary
– audit • Find case records which have been deemed ‘lost’ to reconcile them with current record or temps • Improve our position to take advantage of Trust Road Map for Record Improvement


 eileencodes
 mkilby
 sergeychernyshev
 chikuwait
 axbom
 rkendrick25
 schlessera
 techseoconnect
 baasie
 akademiya2063
 raygrieselhuber