It opened a new channel for blood borne diseases The first recorded outbreak (Later on identified as Hepatitis B) occurred in 1883 following smallpox vaccination. In 1943, Bigger and MacCalum showed that non sterile injections transmitted a pathogen that caused jaundice.. Disposable syringes came in 1950.
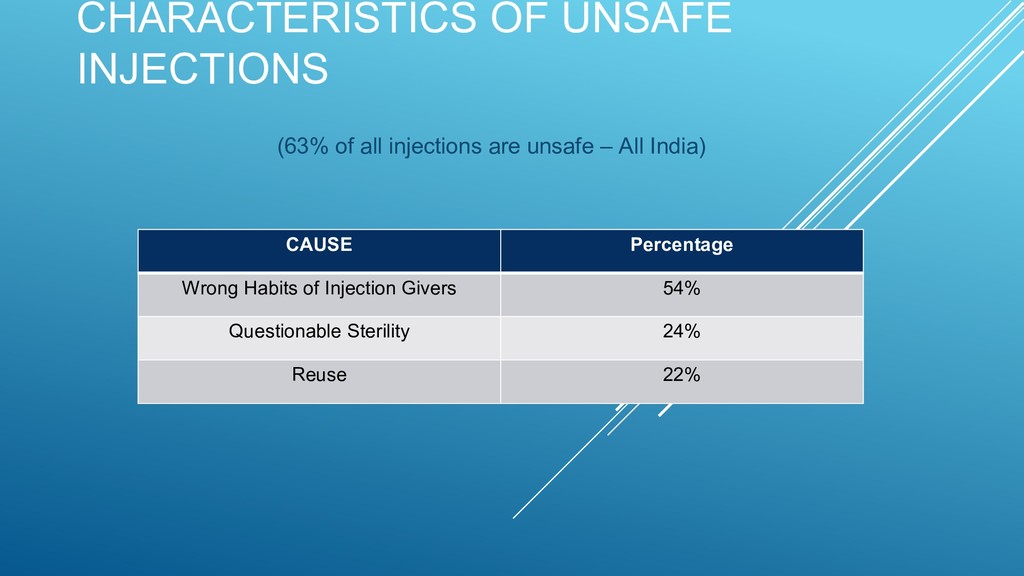
procedure • India contributes to ~30% of the 16 billion injections administered worldwide per year. • Average number of health care injection per person was estimated to be 3.7 per year • More than 95% injections are given for therapeutic purposes • 5% are given for preventive services including immunization and family planning. • Majority of them are unnecessary (90%) and unsafe (50%) • 63% of injections in India are estimated to be unsafe and nearly 27% of these are due to re-use.
injections only when necessary – oral medicines are effective in most cases. Indications for therapeutic injections are 1. Severe and life threatening illness 2. Inability to swallow 3. Profuse vomiting 4. Non availability of effective oral agent 5. Significantly altered absorption pattern 6. The issue of onset of action is clinically relevant only in life threatening illness
According to WHO definition: Safe injection 1. Does not harm the recipient 2. Does not expose the provider to any avoidable risk 3. Does not result in waste that is dangerous for the community
• The lack of awareness, • Social commitment • Lack of availability of sufficient resources in health care settings. • This problem is quite intense in the rural areas.
of disease, disability and death. • Can cause injuries and toxicities when wrong injection site, drug, diluent or dose is used. • The risk of transmission of infection after injury with contaminated sharps is: 1. 1:3 workers for HBV 2. 1:30 for HCV 3. 1:300 for HIV • HBV persists for up to seven days on surfaces.
are: 1. Transmission of other viral, bacterial, fungal or parasitic infections 2. Vaso vagal shock 3. Drug toxicities including Anaphylaxis 4. Injection abscess and infections 5. Nerve injury
and HCV sometimes do not appear and risks are unappreciated until ten or more years after infection, so many more patients may have been infected but are not yet aware of their condition. For example, an assessment of injection practices in India found that nearly one third of all injections carried a potential risk of transmitting a blood borne pathogen.
prevent transmission of infectious diseases • Between one patient and another • Between a patient and health care provider • Prevent harms such as needle stick injuries
infectivity of patient and assuming all body fluids infectious. • Use of sterile single-use needles and syringes for each procedure. • Prevention of any form of contamination to the medication or vaccine to be injected. • Prevention of sharps injuries and • Appropriate waste disposal to prevent reuse of needles and syringes.
issues like sterilization, storage and handling • Reusing syringe or needle for giving injection, for reconstitution of medication, or withdrawal from a multidose vial • Improper selection of length and bore of needle • Changing the needle but reusing the syringe.
supervision or monitoring with time, steam and temperature indicators. • Attempting to sterilize and reuse syringe. • Attempting to sterilize injection equipment without prior cleaning. • Boiling injection equipment in an open pan. (Still done by dentists) • Using only disinfectant on contaminated equipment to prepare them for reuse.
• Unsafe environment • Error in selection of type of medication • Not checking medication vial label and expiry date • Wiping the stopper with antiseptics (Use only spirit and allow it to dry) • Medication should be drawn up in a designated clean area. • Do not reconstitute it till the person to be immunized is ready
• Use of Incorrect diluent. (Diluents are vaccine specific) • Use of incorrect quantity of diluent. • Carelessly breaking the ampoule so as to injure oneself. • Mixing two partially opened vials of same vaccine. • Loading syringe with multiple doses and injecting multiple persons. • Mixing more than one medications in the same syringe. • WHEN IN DOUBT, THROW IT OUT
• Keeping freeze dried vaccines more than six hours after reconstitution. • Leaving a needle in the vial to withdraw additional doses. • Handling of Multidose vial (use new needle every time even if it has not been used) • Opened vial submerged in water.
following product specific recommendations for use, storage and handling, especially vaccines. • Single dose vial used for multiple patients. • Multidose vial when punctured, should be discarded within 28 days. • Always consider IV tubing, syringe and other components as a single inter connected unit. • Even if no blood is seen in IV tubing or syringe, they are always considered as contaminated.
Injection Equipment, Needle size, Air bubble, Wiping the needle 2. Position 3. Proper hand washing and Site preparation (cleansing) 4. Technique 5. Measures to alleviate discomfort and pain 6. Procedure: Insertion of needle, aspiration, pushing the medication 7. Withdrawal of syringe 8. Multiple injections 9. Post injection (Applying pressure to bleeding site with cotton or finger)
buttocks. • Giving injection to infants in gluteal region • Touching needle with finger while injecting (Use as a support) • Dividing the dose of same vaccine.
the ward boy in one so called multi specialty hospital injecting the patient and taking sutures. 1. Mixing tetanus toxoid and diclofenac in the same syringe. 2. Tetanus toxoid was not stored in refrigerator. 3. Giving that injection in gluteal region. (Vaccines are never ever to be given in gluteal region). 4. Took a previously used skin stapler lying in the open tray and took sutures. Just see how many issues have been compromised???
PREVENT SHARP INJURIES Magnitude of Sharp Injury (Needle Stick Injury-NSI): Considering it on an individual basis, according to WHO, it ranges from 0.93 to 4.68 injuries per person per year in developing countries as against only 0.18 to 0.74 in developed countries. Majority of sharp injuries occur between completing the procedure and disposing of the device.
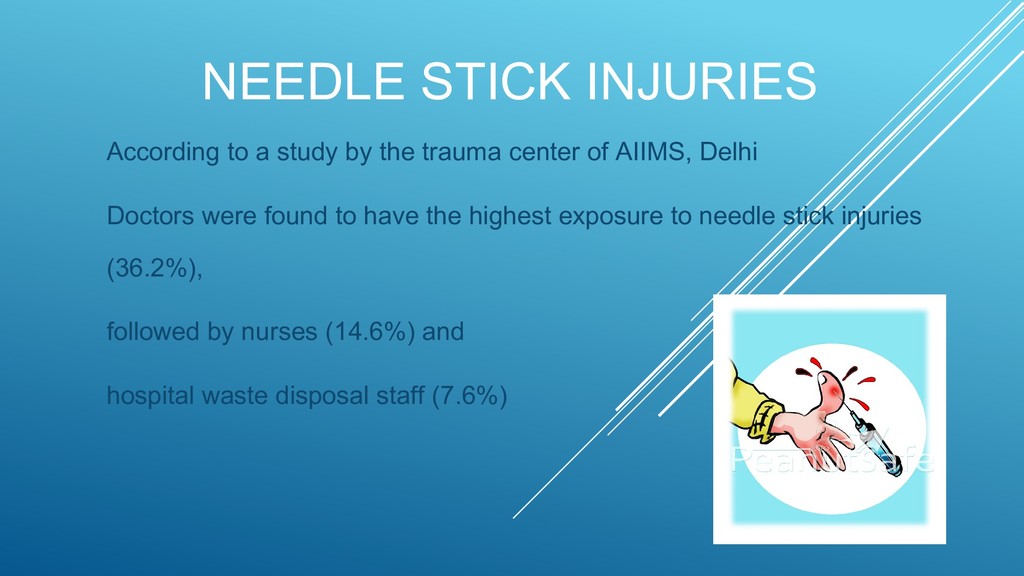
center of AIIMS, Delhi Doctors were found to have the highest exposure to needle stick injuries (36.2%), followed by nurses (14.6%) and hospital waste disposal staff (7.6%)
PREVENT SHARP INJURIES • Skin integrity is compromised by local infection or weeping dermatitis. (cover any small cut with water proof adhesives or wear gloves) • Moving around with a filled or used syringe in the hand. • Accidental injury while giving injection (Beware of unusual and abrupt movement by a child or patient)
PREVENT SHARP INJURIES • Trying to recap, bend or manually remove the needle from the syringe after use. • Reaching into a mass of used equipment (For cleaning or sorting waste) • Sharp container is kept at a distance from place of procedure. • Quality and standard of sharps container.
of job. • Imparting knowledge is not enough. • There is a need to change the behavior of both service provider and patients. • The risks can be drastically reduced by 84-100% through IEC, safer working place and using newer technology. • Minimum handling of injection equipment is key to preventing sharp injuries. • Use of Needle cutter and burner has been made mandatory by law.
• Discarding and dumping used injections in public places by drug users. • Home injections for diabetes, cancer, AIDS, osteoporosis etc. • SMBG by diabetics • Children, home health care providers, sanitation workers, rag pickers are at a risk of sharp injury. • Giving or selling used syringes to vendors who will resale them.
USED AT HOME, AT WORK, OR WHILE TRAVELING Do • Immediately place used needles and other sharps in a sharps disposal container to reduce the risk of needle-sticks, cuts, or punctures from loose sharps. • Keep all needles and other sharps and sharps disposal containers out of reach of children and pets • Be prepared — carry a portable sharps disposal container for travel.
USED AT HOME, AT WORK, OR WHILE TRAVELING DON’T throw loose needles and other sharps into the trash. DON’T flush needles and other sharps down the toilet. DON’T put needles and other sharps in your recycling bin -- they are not recyclable. DON’T try to remove, bend, break, or recap needles used by another person.
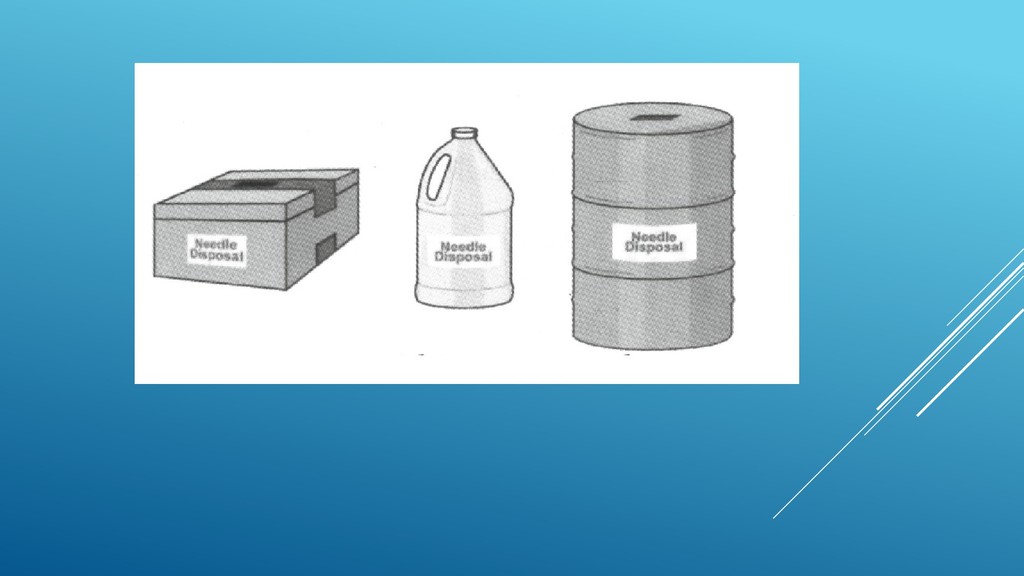
of a heavy-duty plastic • able to close with a tight-fitting, puncture-proof lid, without sharps being able to come out • upright and stable during use • leak-resistant • properly labeled.
safety boxes are not available, • Strong cardboard boxes, metal cans or thick plastic containers may be used. • Collect needles and syringes and transport them to a site where they can be properly treated (buried, incinerated or autoclaved and shredded). • Containers should be sealed when they are three-quarters full. • They should not be reused once filled. • Emptying sharps containers for reuse increases the risk of accidental needle-stick injuries and infections.
Downstream Reuse – After not properly discarding the syringes by the injection giver, someone else takes it for reuse. • Improper Disposal • Picked up by rag pickers • Sold to scrap dealers • Cleaned, Disinfected(?), Repacked • Resale in the market
reuse of the syringe • Lack of knowledge, education and awareness. • Ignorance and misconception • Altruism- disinterested and selfless concern for the well being of others • Lack of resources and corruption • Monitory gain "Most healthcare workers who do reuse syringes are really decent people, but the system forces them to."
not enough. There is a need to change the behavior of both service providers and their patients. In February 2015, the WHO issued a policy that urged all nations to switch to the use of "smart" single-use syringes by 2020. These are syringes that are specifically engineered to prevent their re-use. The transition could potentially help save millions of lives.
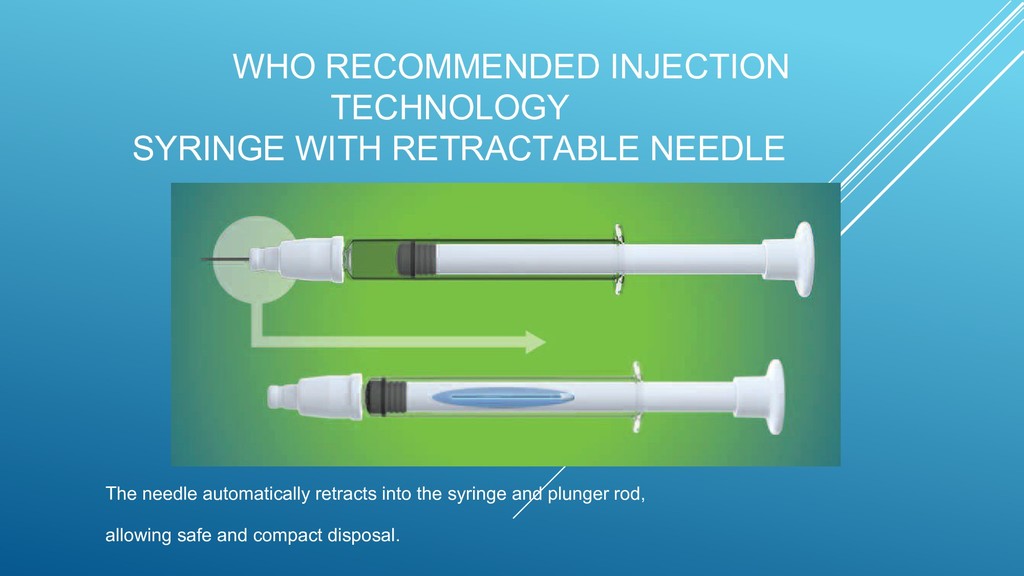
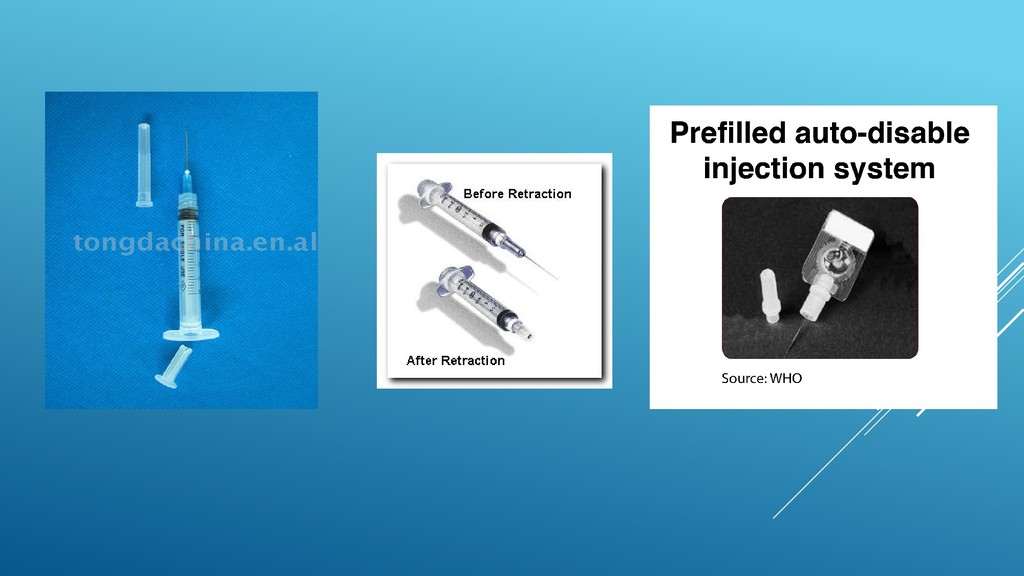
their endeavor towards safe injection practice. It prevents both downstream and intentional reuse. 1. Auto Disable AD syringe 2. Re use prevention RUP syringe 3. Prefilled injection devices. 4. Safety syringes with retractable needles 5. Vacuum based technology for blood collection
become disabled after one use. After the plunger is depressed past the point of safety, it cannot be pulled backwards for reuse. These are in use across the globe post a joint endorsement by WHO, UNICEF and UNFPA.
the plunger is fully pressed, the plunger mechanism locks into the needle unit. When the plunger is pulled back, the needle also gets pulled back into the syringe barrel, enclosing the used needle. The needle shield protects others from accidental needle sticks and prevents reuse of the syringe.


 lauravandoore
 jacobtomlinson
 marcelosomers
 427marketing
 marcoroth
 mojombo
 techseoconnect
 mlcsv
 tmiket
 mayunak
 soysaucechin
 bcantrill