up sex and devote your life to transposition of great arteries n 7 things lady gaga has in common with transposition of great arteries n 11 ways investing in transposition of great arteries can make you a millionaire n guns don't kill people -- transposition of great arteries kills people n what the government doesn't want you to know about transposition of great arteries
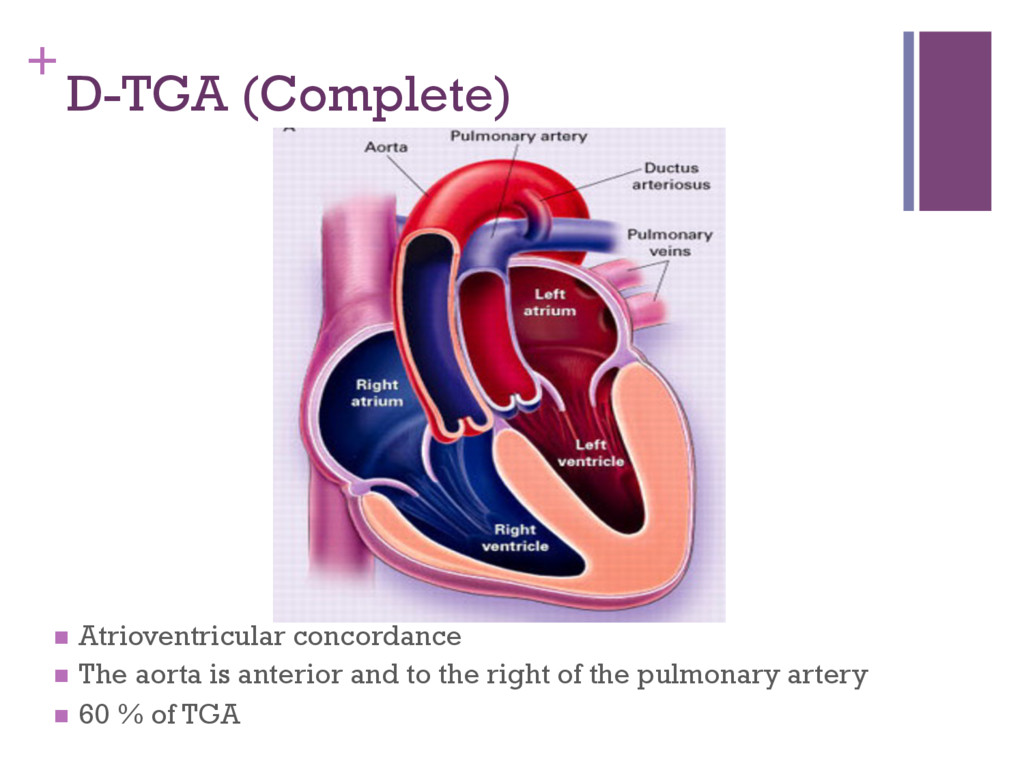
intact ventricular septum n (2) transposition of the great arteries with ventricular septal defect n (3) transposition of the great arteries with ventricular septal defect and left ventricular outflow tract obstruction n (4) transposition of the great arteries with ventricular septal defect and pulmonary vascular obstructive disease.
from the right coronary artery (22%) n A single right coronary artery (9.5%) n A single left coronary artery (3%) n Inverted origin of the coronary arteries (3%)
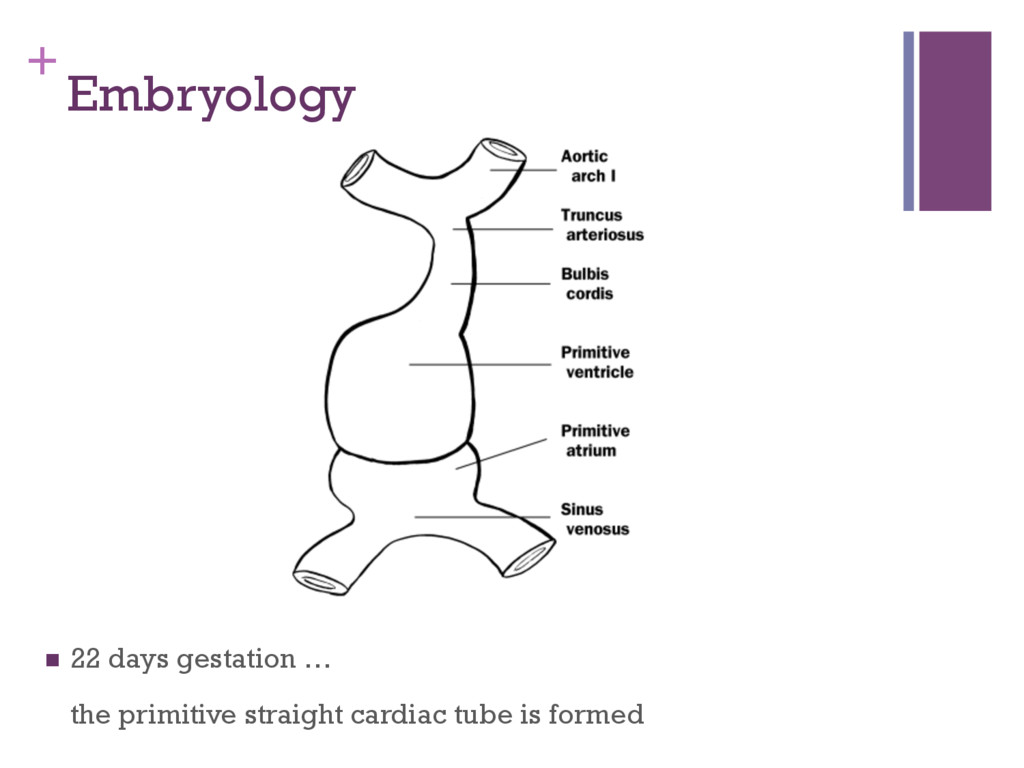
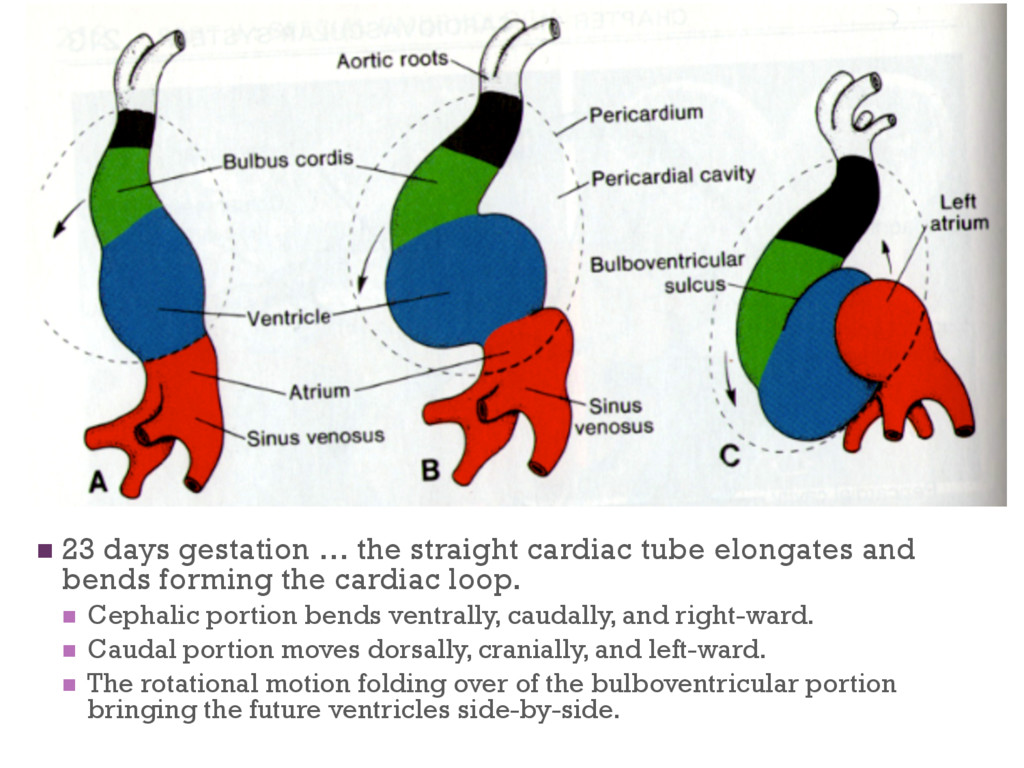
elongates and bends forming the cardiac loop. n Cephalic portion bends ventrally, caudally, and right-ward. n Caudal portion moves dorsally, cranially, and left-ward. n The rotational motion folding over of the bulboventricular portion bringing the future ventricles side-by-side.
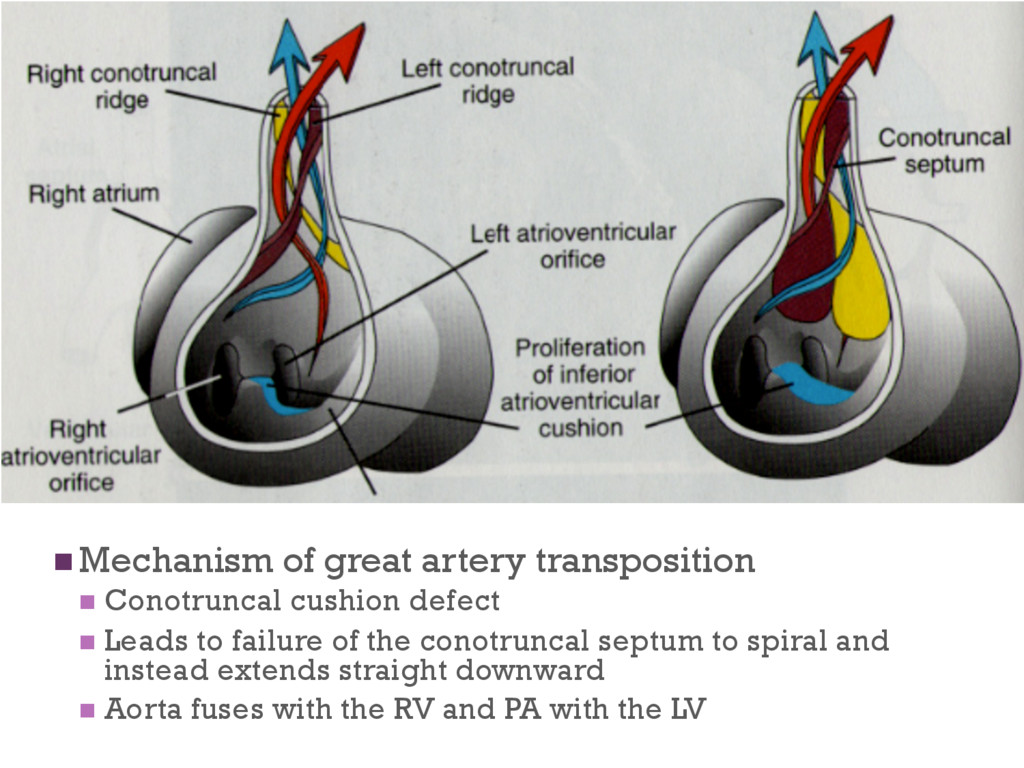
4 chambers via formation of swellings (cushions) of tissue that exhibit differential growth. n Endocardial cushions divide the AV canal forming the mitral and tricuspid valves. n Conotruncal cushions form the outflow tracts, aortic and pulmonary roots.
Right superior truncal cushion grows distally and left- ward. n Left inferior truncal cushion grows distally and right- ward. n The net effect is a twisting motion. n The truncal cushions fuse to form the truncal septum. n Additional cushions develop in the conus which grow down and towards each other until they fuse with the truncal septum to form the RVOT and LVOT.
by a cardiovascular malformation*. n > 750,000 adult patients with congenital heart disease. n Transposition of the great arteries occurs in approximately 1 per 5,000 live births. n More common in males n Diagnosis possible in utero with fetal echocardiography n Transvaginal ultrasound at 13-14 weeks (limited views) n Transabdominal ultrasound at 16 weeks *not including bicuspid aortic valve and mitral valve prolapse
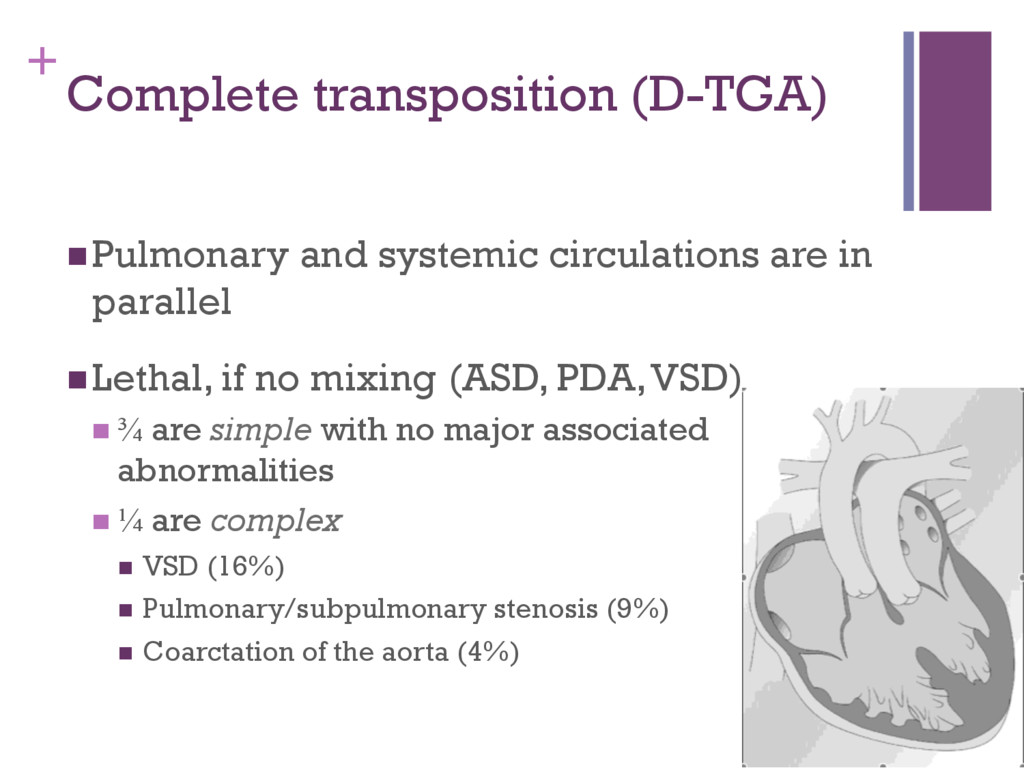
parallel n Lethal, if no mixing (ASD, PDA, VSD) n ¾ are simple with no major associated abnormalities n ¼ are complex n VSD (16%) n Pulmonary/subpulmonary stenosis (9%) n Coarctation of the aorta (4%)
and weight at birth n Dyspnea and cyanosis n Progressive hypoxemia n Congestive heart failure n Without treatment, the outlook is dismal n 30% mortality within the 1st week n 90% mortality within the 1st year
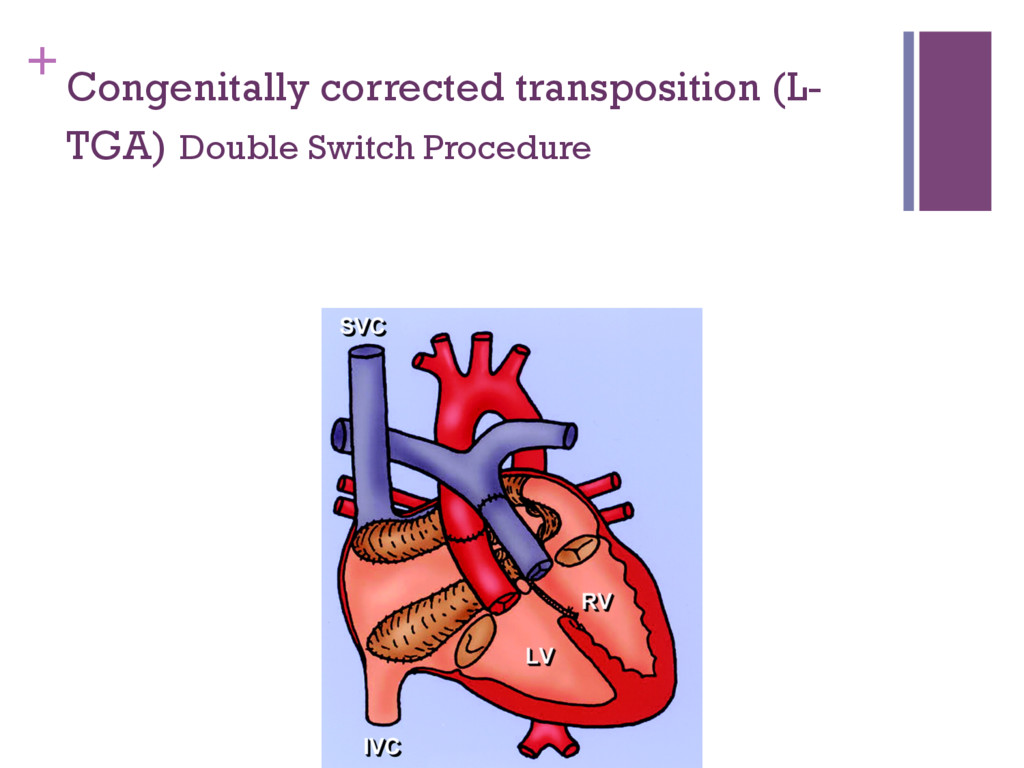
PDA n Atrial septostomy (balloon or surgical) n Palliative prior to corrective surgery n Repair within the first days to weeks of life n 2-4% mortality with 90% 1 year survival n Atrial switch n Mustard or Senning n Arterial switch n Rastelli procedure
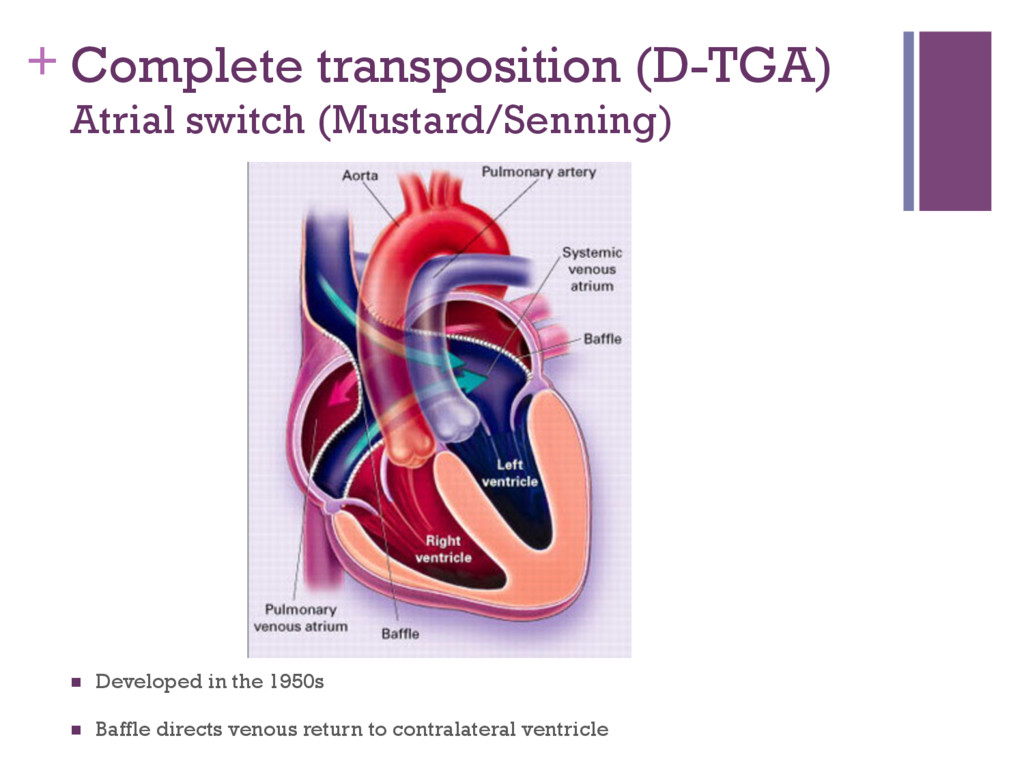
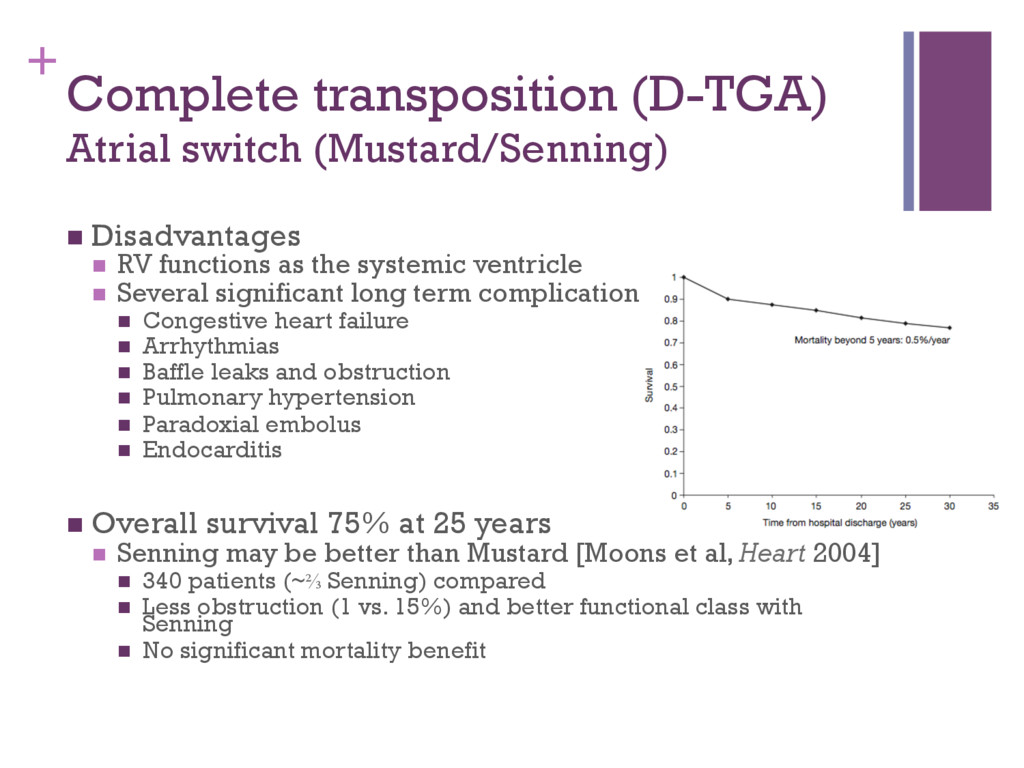
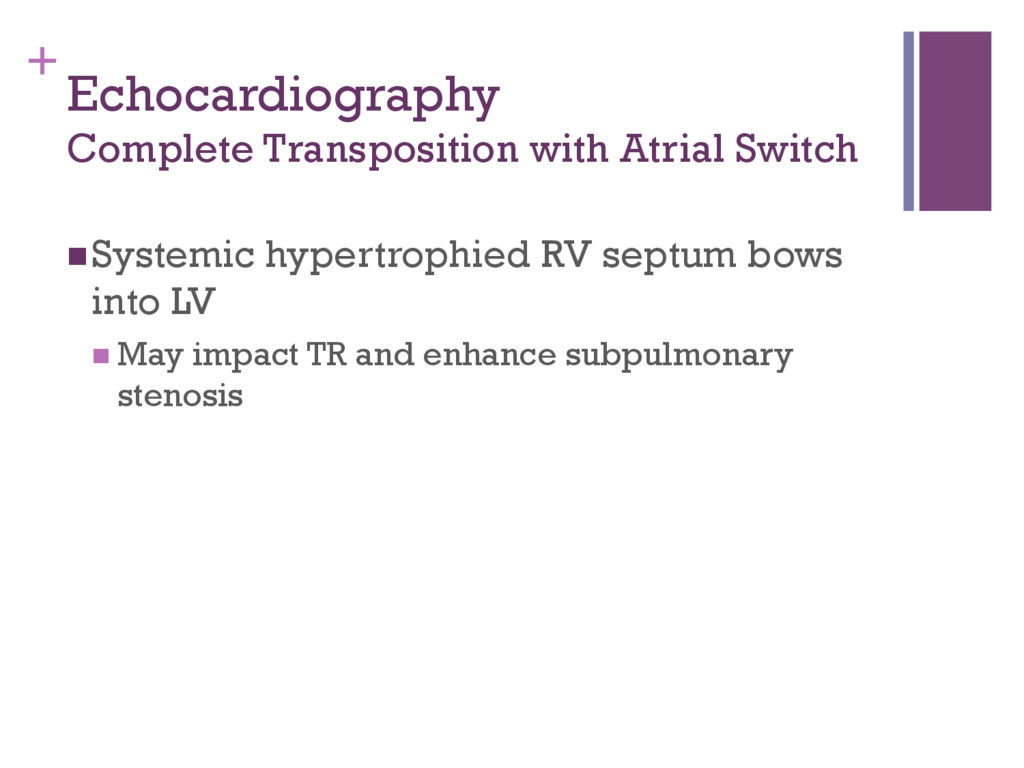
RV functions as the systemic ventricle n Several significant long term complications n Congestive heart failure n Arrhythmias n Baffle leaks and obstruction n Pulmonary hypertension n Paradoxial embolus n Endocarditis n Overall survival 75% at 25 years n Senning may be better than Mustard [Moons et al, Heart 2004] n 340 patients (~⅔ Senning) compared n Less obstruction (1 vs. 15%) and better functional class with Senning n No significant mortality benefit
presyncope, and syncope are common n Both brady and tachyarrythmias frequently seen n 50% develop sinus node dysfunction n Physical damage during surgery and baffle construction n Disruption of blood supply leading to ischemia n 20% develop atrial flutter n Sensitive to nodal agents due to conduction system disease n 11% required pacemakers at 20 years [Gelatt et al, J Am Coll Cardiol 1997] n Pacemakers are difficult to place due to distorted anatomy n Should be avoided if residual intracardiac communications due to risk of paradoxical embolus and stroke
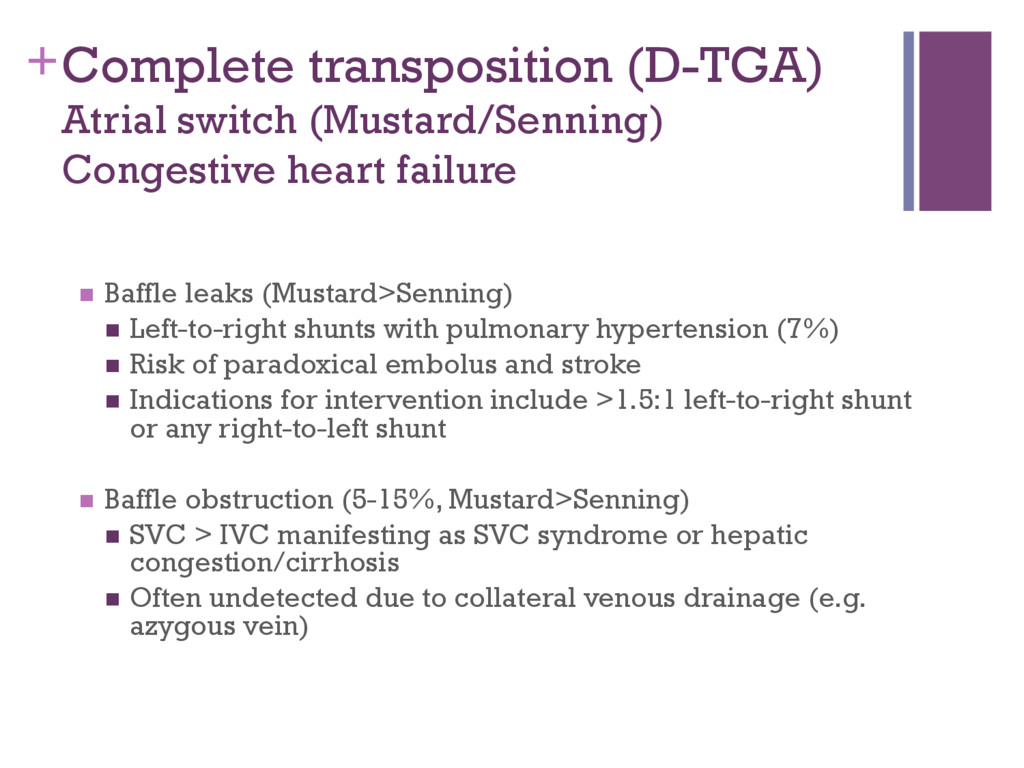
Baffle leaks (Mustard>Senning) n Left-to-right shunts with pulmonary hypertension (7%) n Risk of paradoxical embolus and stroke n Indications for intervention include >1.5:1 left-to-right shunt or any right-to-left shunt n Baffle obstruction (5-15%, Mustard>Senning) n SVC > IVC manifesting as SVC syndrome or hepatic congestion/cirrhosis n Often undetected due to collateral venous drainage (e.g. azygous vein)
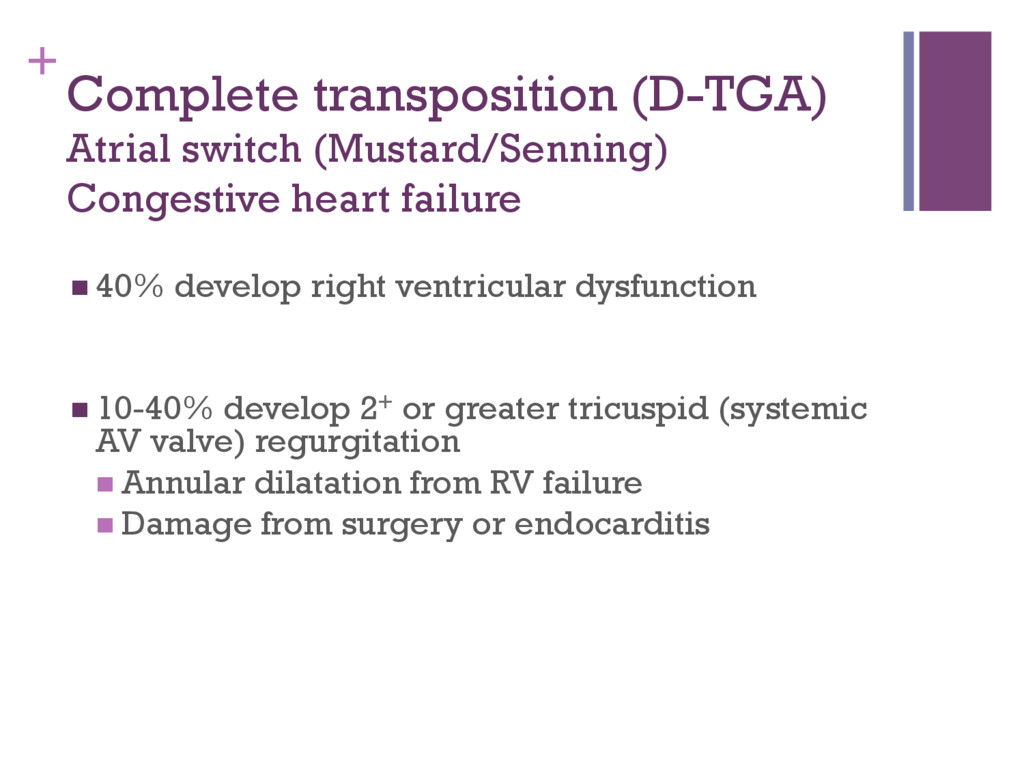
greater tricuspid (systemic AV valve) regurgitation n Annular dilatation from RV failure n Damage from surgery or endocarditis Complete transposition (D-TGA) Atrial switch (Mustard/Senning) Congestive heart failure
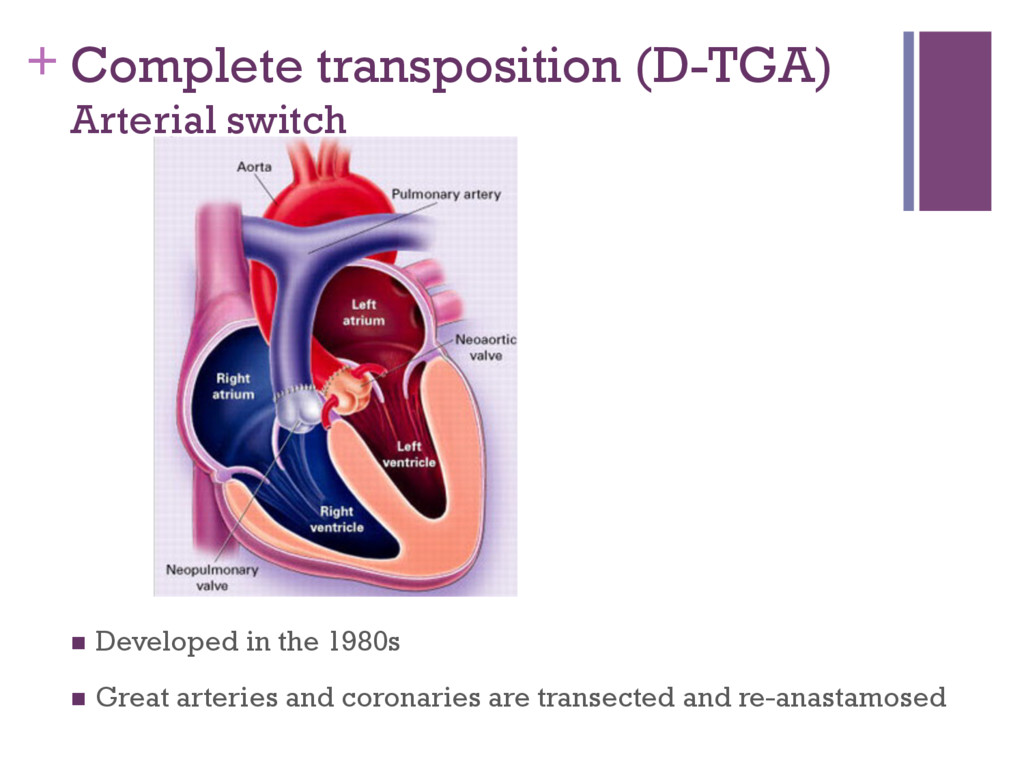
is the systemic pump n No disruption of atrial conduction (sinus rhythm) n Fewer long term complications compared to atrial switch n Coronary ostial stenosis n Supravalvular pulmonary/aortic stenosis n Intervention indicated for RVOT gradient >50 mmHg n Neoaortic regurgitation n Arrhythmias n Follow up with normal LV function and good exercise capacity
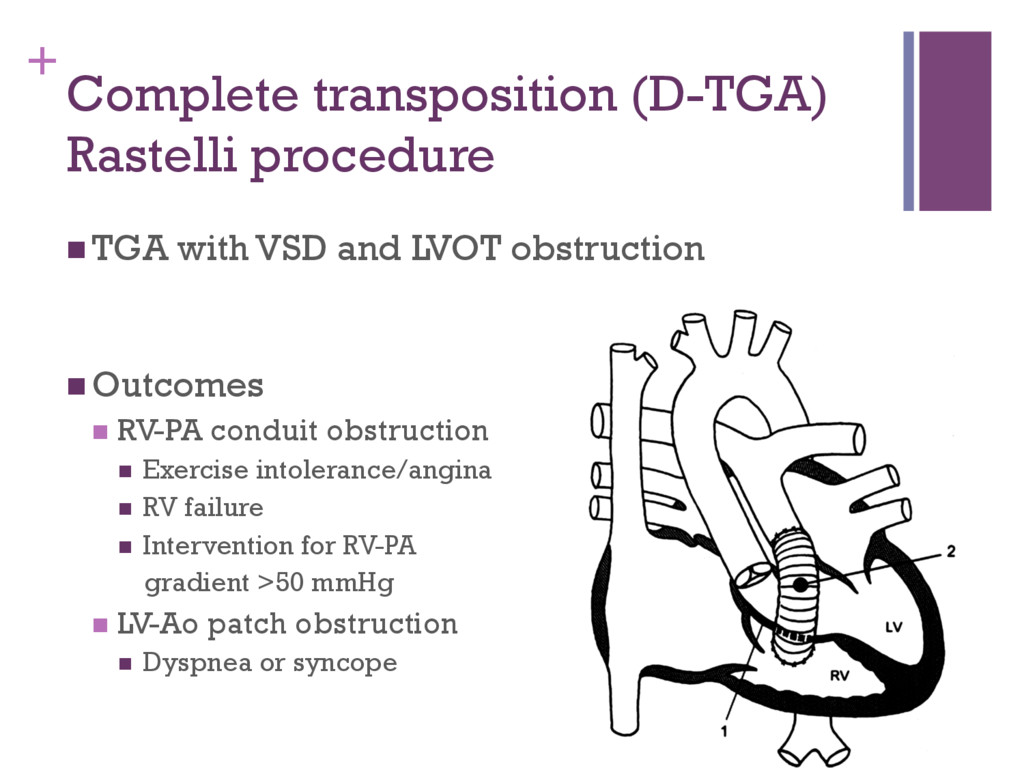
LVOT obstruction n Outcomes n RV-PA conduit obstruction n Exercise intolerance/angina n RV failure n Intervention for RV-PA gradient >50 mmHg n LV-Ao patch obstruction n Dyspnea or syncope
heart failure therapies are unproven n The two-stage arterial switch n Stage 1 – the PA is banded to ‘re-train’ the LV to handle systemic pressures n Stage 2 – the atrial baffles and pulmonary band are taken down and an arterial switch is performed n 50% survival at 8 years in early results n Appears to be more successful in patients under 12
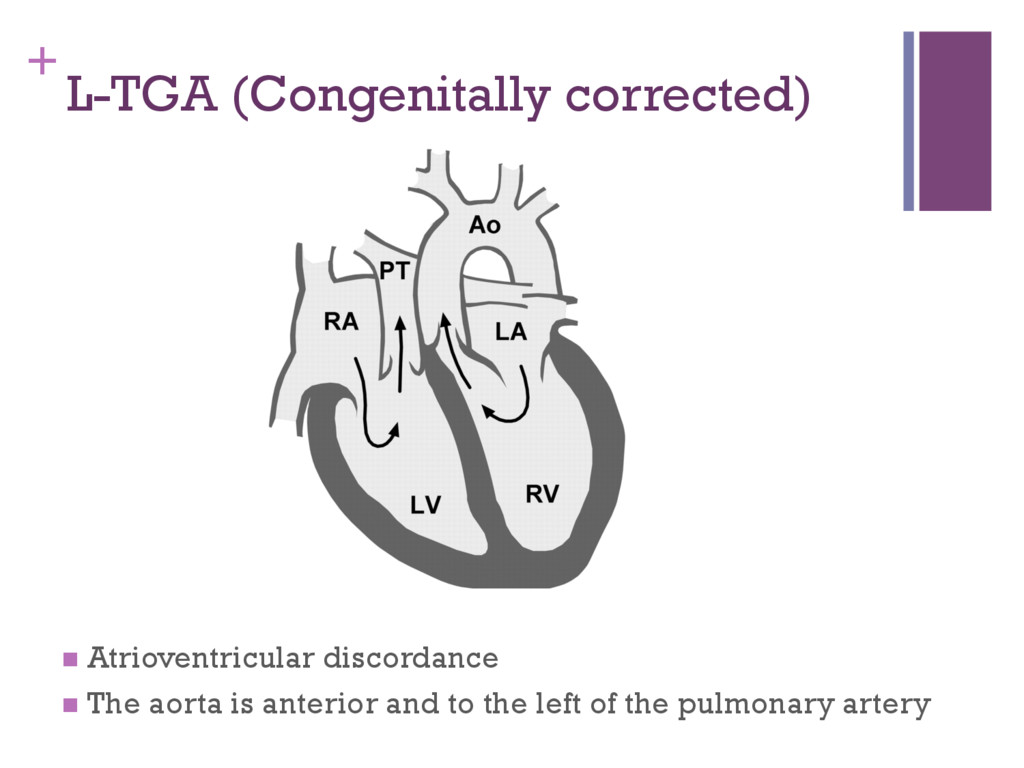
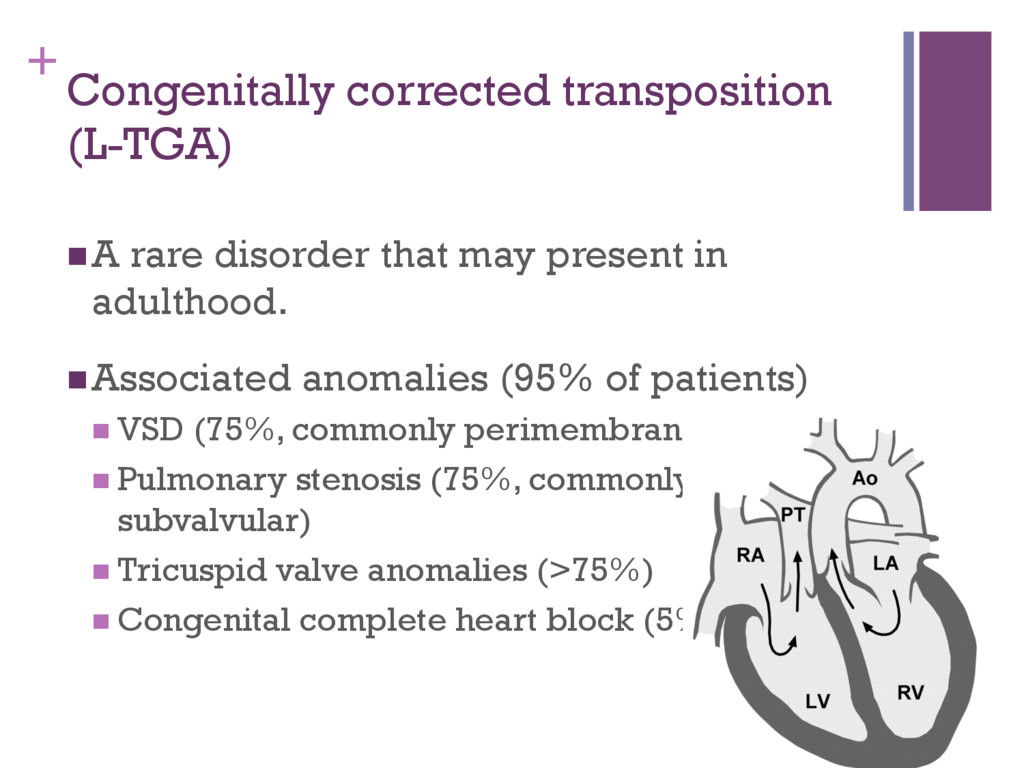
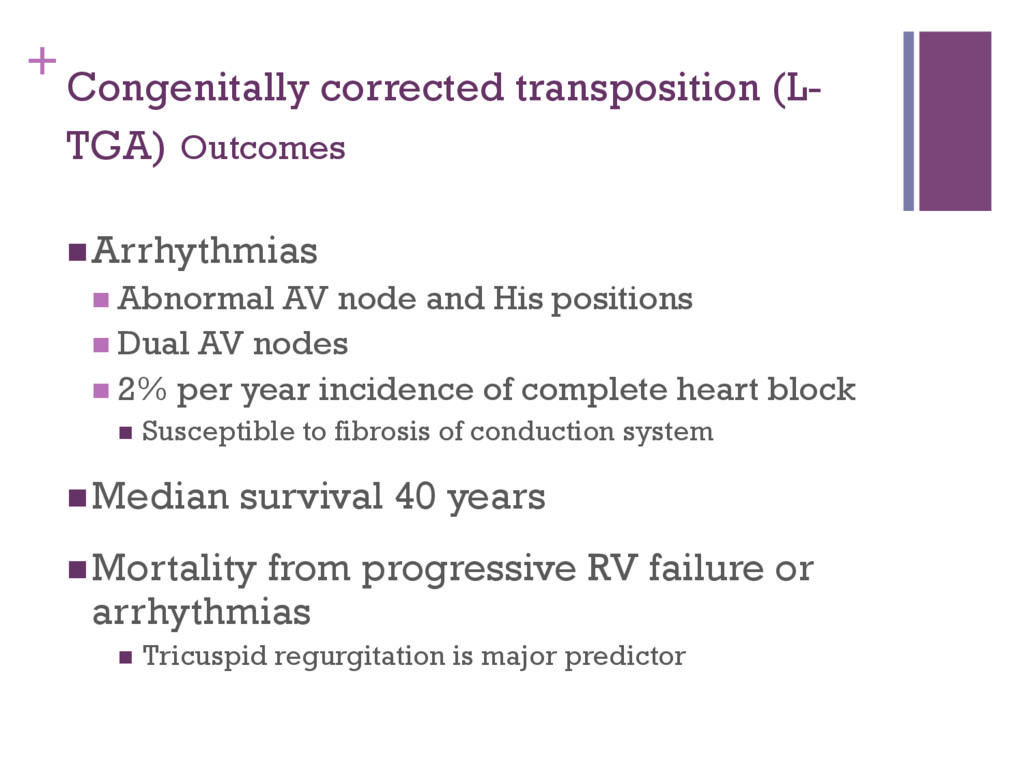
present in adulthood. n Associated anomalies (95% of patients) n VSD (75%, commonly perimembranous) n Pulmonary stenosis (75%, commonly subvalvular) n Tricuspid valve anomalies (>75%) n Congenital complete heart block (5%)
node and His positions n Dual AV nodes n 2% per year incidence of complete heart block n Susceptible to fibrosis of conduction system n Median survival 40 years n Mortality from progressive RV failure or arrhythmias n Tricuspid regurgitation is major predictor
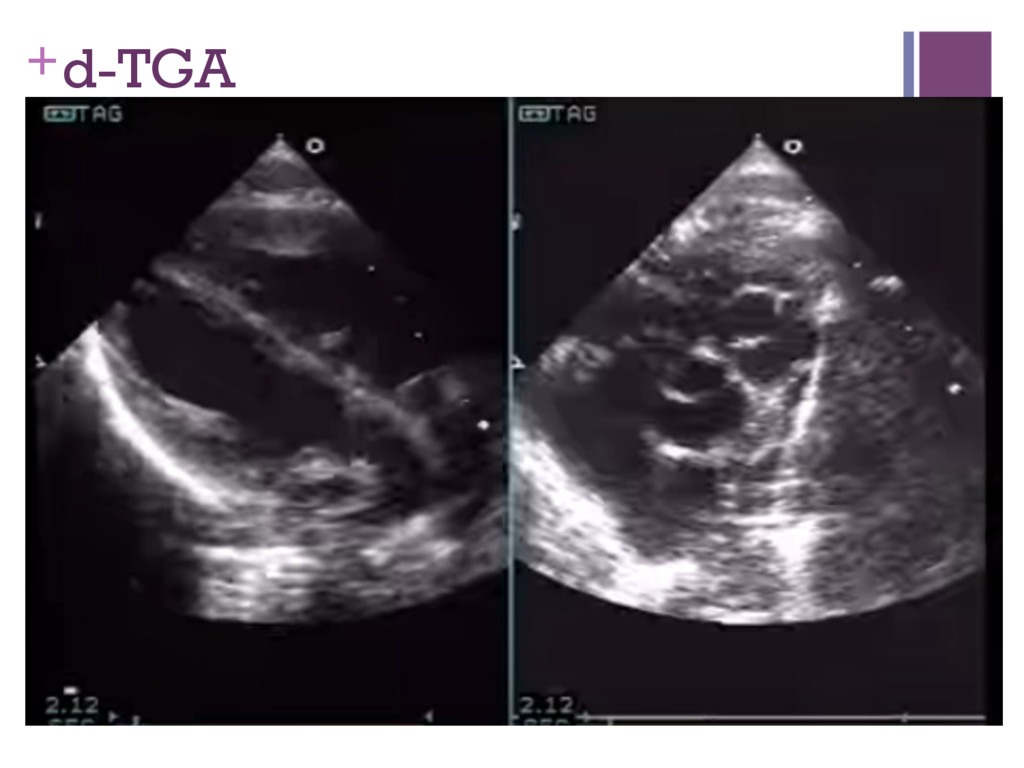
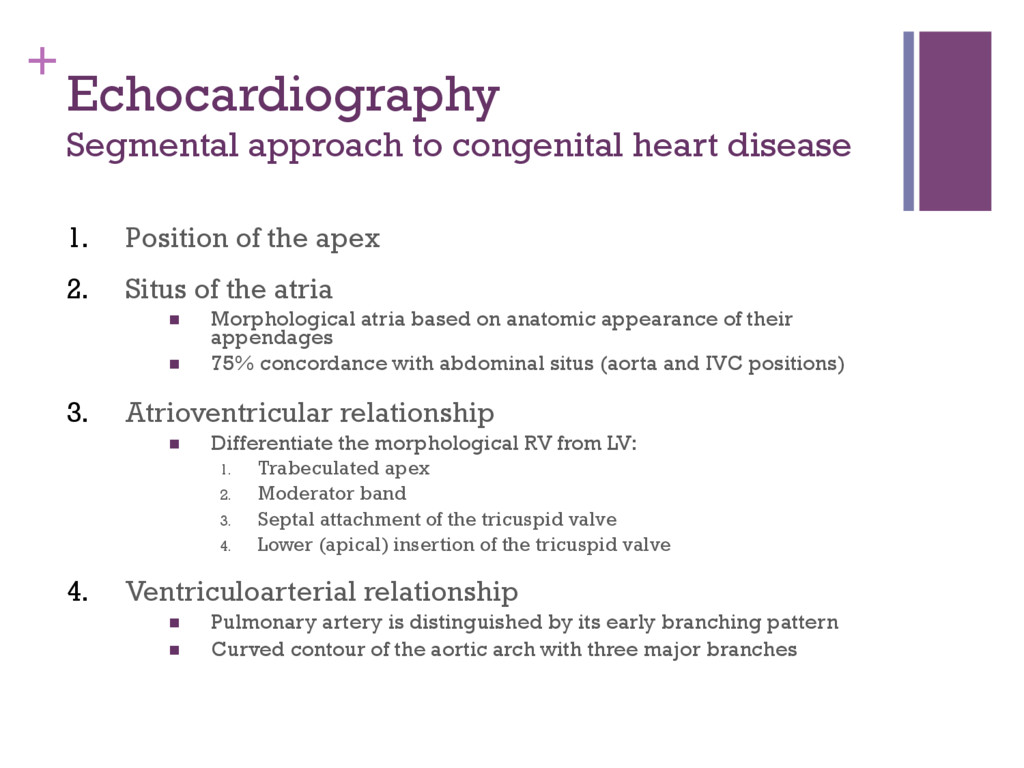
of the apex 2. Situs of the atria n Morphological atria based on anatomic appearance of their appendages n 75% concordance with abdominal situs (aorta and IVC positions) 3. Atrioventricular relationship n Differentiate the morphological RV from LV: 1. Trabeculated apex 2. Moderator band 3. Septal attachment of the tricuspid valve 4. Lower (apical) insertion of the tricuspid valve 4. Ventriculoarterial relationship n Pulmonary artery is distinguished by its early branching pattern n Curved contour of the aortic arch with three major branches
n Tricuspid regurgitation n Subpulmonary obstruction n Baffle leak or obstruction (color Doppler) n Normal baffle flow is phasic with peak velocity <1 m/sec n Arterial switch n Neoaortic valve regurgitation n Supraneopulmonary valve stenosis n Wall motion abnormalities due to coronary artery ostial stenosis n Rastelli procedure n LV-Ao tunnel patch obstruction n RV-PA conduit degeneration (stenosis/regurgitation)
tricuspid regurgitant velocity n Isovolumic myocardial acceleration n Tissue Doppler measurement of myocardial acceleration during isovolumic contraction n ?sensitive assessment of RV contractility that is less load dependent
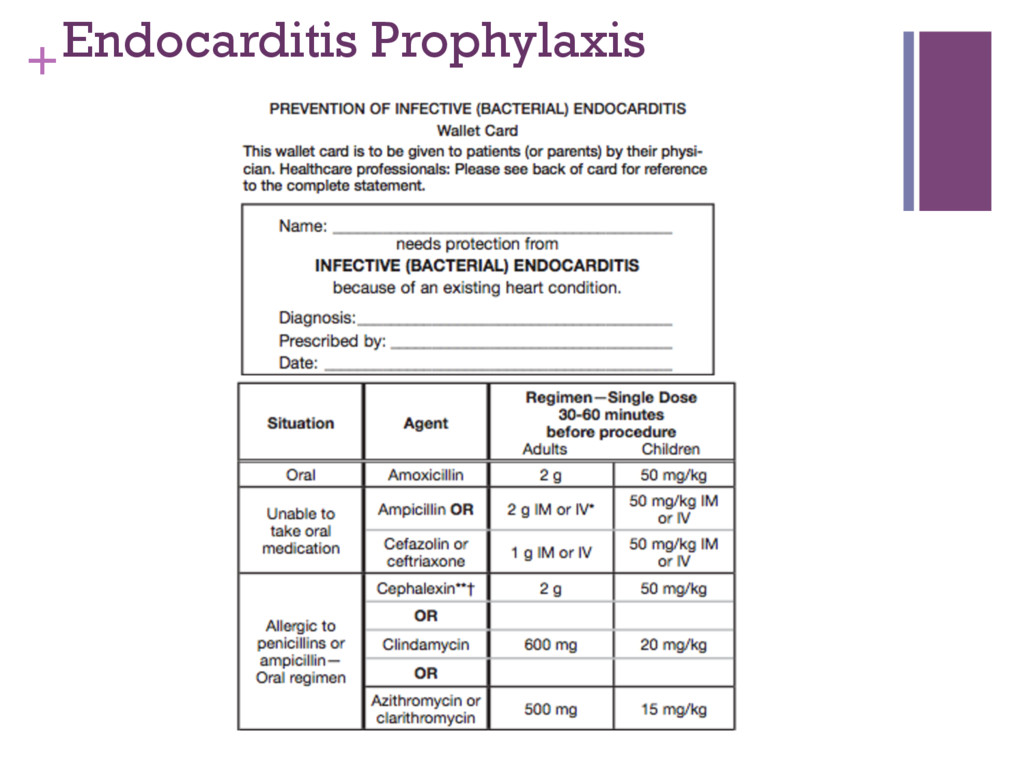
is reasonable to consider for patients at the highest risk of adverse outcomes (Class IIa) n Prosthetic valves n Prior endocarditis n Congenital heart disease n Unrepaired cyanotic, including palliative shunts and conduits n Completely repaired with prosthetic material or device (6 months) n Repaired with defects at or near a prosthetic device n Post-cardiac transplant with valvular disease
Braunwald’s Heart Disease, 8th ed., Chapter 61, 1561-1624. n Sadler, Cardiovascular System in Langman’s Medical Embryology, 8th ed., Chapter 11, 208-259. n Otto, The Adult with Congenital Heart Disease in Clinical Echocardiography, 4th ed., Chapter 17, 418-447. n Warnes, Transposition of the Great Arteries, Circulation 2006 114:2699-2709. n Love et al., Evaluation and Management of the Adult Patient with Transposition of the Great Arteries Follow Atrial-level (Senning or Mustard) Repair, Nature Clinical Practice Cardiovasc Med 2008 5:454-67. n Verhuegt et al., Long-term Prognosis of Congenital Heart Defects: A Systematic Review, Int J Cardiol 2008 131:25-32. n Skinner et al., Transposition of the Great Arteries: from Fetus to Adult, Heart 2008 94:1227-35 n ACC/AHA Guidelines for the Management of Adults with Congenital Heart Disease, J Am Coll Cardiol 2008 52:e1-121. n Images courtesy: Langman’s and Braunwald’s


 bkeepers
 maltzj
 tmiket
 orderedlist
 frankvandijk
 codingconduct
 elsirapls
 moore
 holman
 asonas
 rkendrick25