Hospital, Calgary @brent_thoma Brent Thoma, EM Resident! Simulation/Research Fellow at Massachusetts General @ermentor Nadim Lalani, Adult and Pediatric EM Physician @olszynskip Paul Olszynski, Adult EM Physician
PE has a high mortality! ! 2. That CTPA has an exceedingly low risk of harm! ! 3. That CTPA is accurate at diagnosing PE! ! 4. That if we diagnose PE we can significantly reduce a patient’s risk of death by treating them with anticoagulation
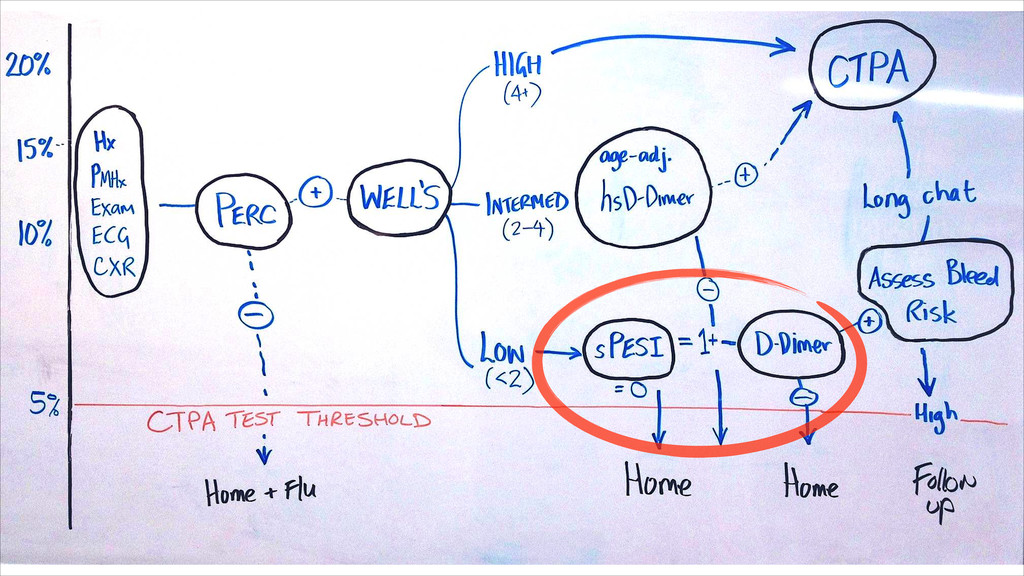
threshold for CTPA (>4.8%)! ! 2. Using the sPESI score to prognosticate in the tricky mildly-symptomatic patient category! ! 3. Anticoagulation may not really be making a big difference to outcomes in simple, haemodynamically stable, small PEs
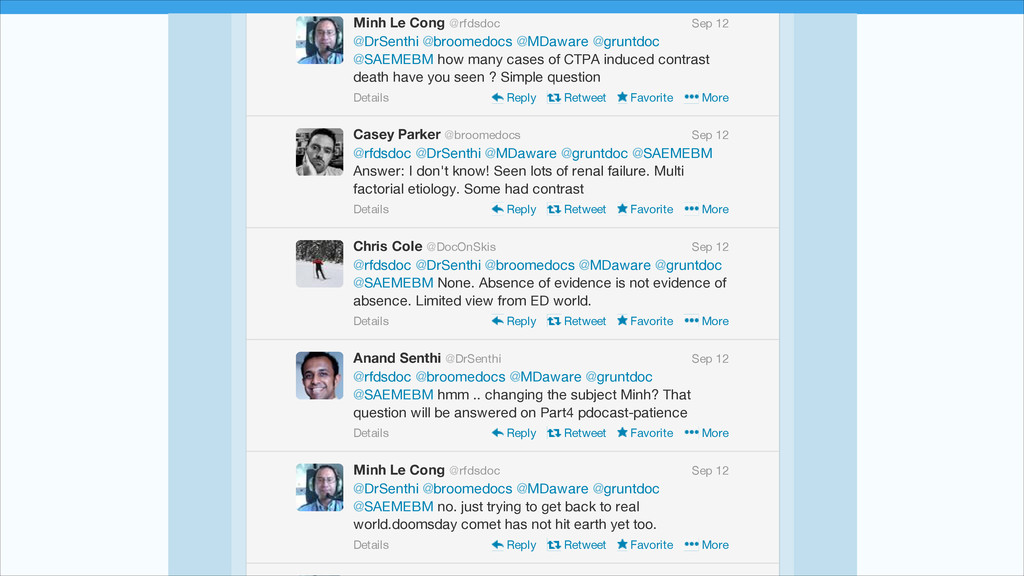
many cases of CTPA induced contrast death have you seen ? Simple question Sep 12 Details Reply Retweet Favorite More Casey Parker @broomedocs @rfdsdoc @DrSenthi @MDaware @gruntdoc @SAEMEBM Answer: I don't know! Seen lots of renal failure. Multi factorial etiology. Some had contrast Sep 12 Details Reply Retweet Favorite More Chris Cole @DocOnSkis @rfdsdoc @DrSenthi @broomedocs @MDaware @gruntdoc @SAEMEBM None. Absence of evidence is not evidence of absence. Limited view from ED world. Sep 12 Details Reply Retweet Favorite More Anand Senthi @DrSenthi @rfdsdoc @broomedocs @MDaware @gruntdoc @SAEMEBM hmm .. changing the subject Minh? That question will be answered on Part4 pdocast-patience Sep 12 Details Reply Retweet Favorite More Minh Le Cong @rfdsdoc @DrSenthi @broomedocs @MDaware @gruntdoc @SAEMEBM no. just trying to get back to real world.doomsday comet has not hit earth yet too. Sep 12 Details Reply Retweet Favorite More
Excluding Pulmonary Embolism at the Bedside without Diagnostic Imaging: Management of Patients with Suspected Pulmonary Embolism Presenting to the Emergency Department by Using a Simple Clinical Model and D-dimer Philip S. Wells, MD, MSc; David R. Anderson, MD; Marc Rodger, MD, MSc; Ian Stiell, MD, MSc; Jonathan F. Dreyer, MD; David Barnes, MD; Melissa Forgie, MD; George Kovacs, MD; John Ward, MD; and Michael J. Kovacs, MD After 3 months, patients were followed up for development of thromboembolic events at a return appointment or by telephone contact.!


 medrez
 palkan
 schroneko
 jeffersonlam
 minecr
 62gerente
 cassininazir
 baasie
 chriscoyier
 soysaucechin
 jdejongh
 lara
 honzajavorek