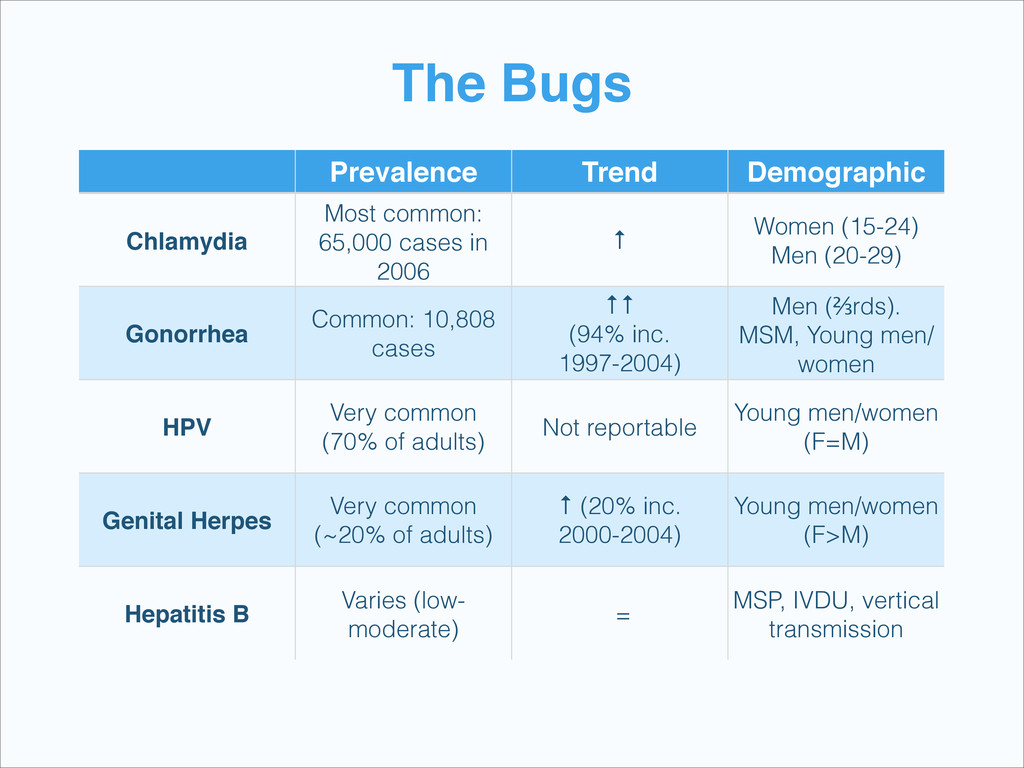
in 2006 ↑ Women (15-24) Men (20-29) Gonorrhea Common: 10,808 cases ↑↑ (94% inc. 1997-2004) Men (⅔rds). MSM, Young men/ women HPV Very common (70% of adults) Not reportable Young men/women (F=M) Genital Herpes Very common (~20% of adults) ↑ (20% inc. 2000-2004) Young men/women (F>M) Hepatitis B Varies (low- moderate) = MSP, IVDU, vertical transmission
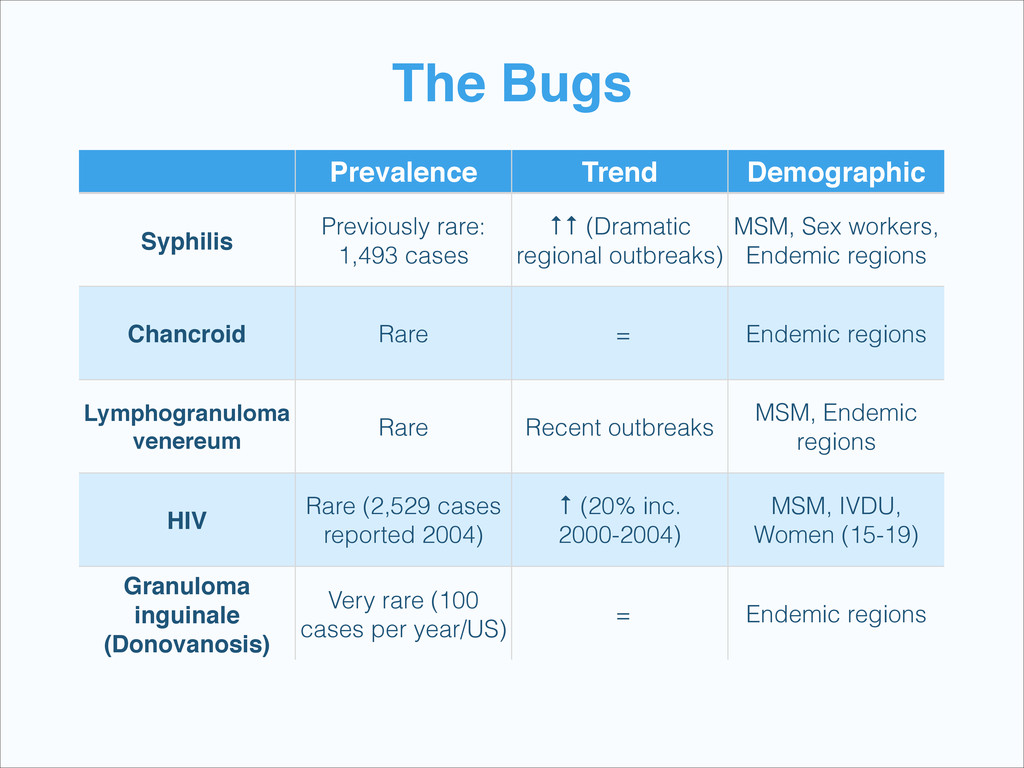
↑↑ (Dramatic regional outbreaks) MSM, Sex workers, Endemic regions Chancroid Rare = Endemic regions Lymphogranuloma venereum Rare Recent outbreaks MSM, Endemic regions HIV Rare (2,529 cases reported 2004) ↑ (20% inc. 2000-2004) MSM, IVDU, Women (15-19) Granuloma inguinale (Donovanosis) Very rare (100 cases per year/US) = Endemic regions
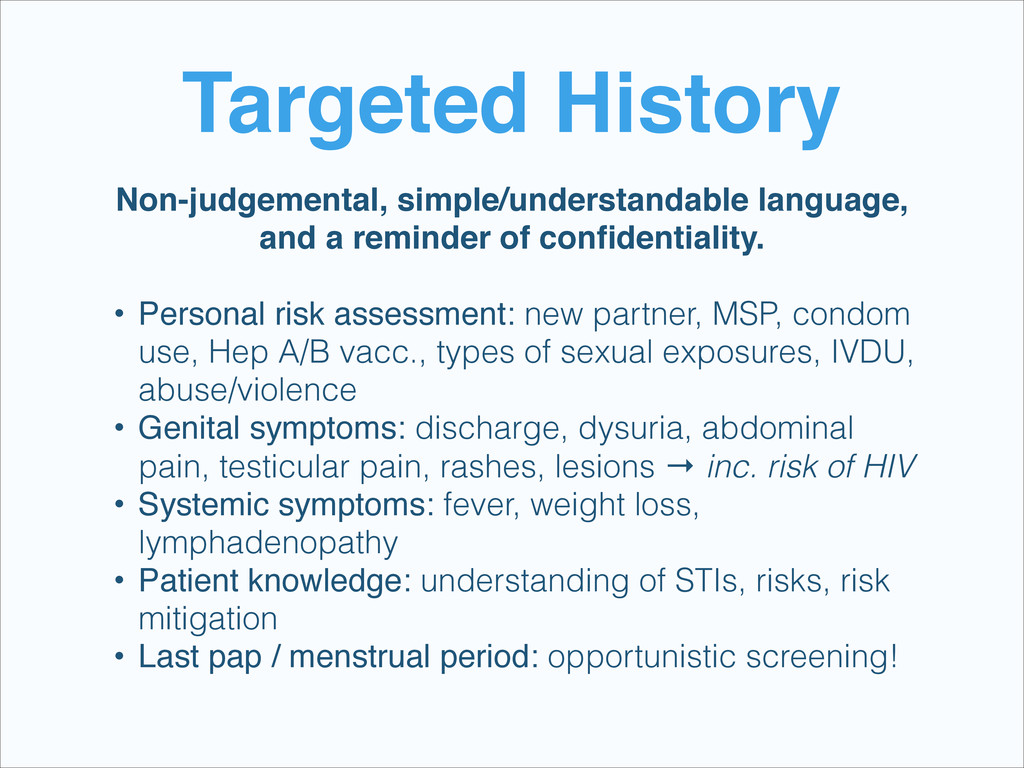
local prevalence • New partner(s) in last 60 days • Multiple partners (>2 in last year) • History of prior STI / partner with known STI • IVDU • Time in prison / youth detention • Contact with sex workers • Homelessness • Sexual assault victims
Are you sexually active? • Do you have symptoms that may make you think you have an STI? • What are you doing to avoid pregnancy? • What are you doing to avoid STIs? • Concerns of sexual or relationship violence? • Are you or your partner IVDU?
prevalence Specific patient request ! “The Usual”: Chlamydia, Gonorrhea, Syphilis & HIV! ! for all sexually active patients under 25! as well as! those at risk
Gonorrhea! • Test of cure not usually required (high treatment success rates) • CSF/vesicle fluid/ulcer swab NAAT preferred for HSV (~100% sens/spec), but not widely available • Serological Treponemal ELISA preferred for Syphilis, highly sensitive but not specific. If positive test result, lab will confirm with Treponemal-specific test (TP-PA, MHA-TP, FTA- ABS)
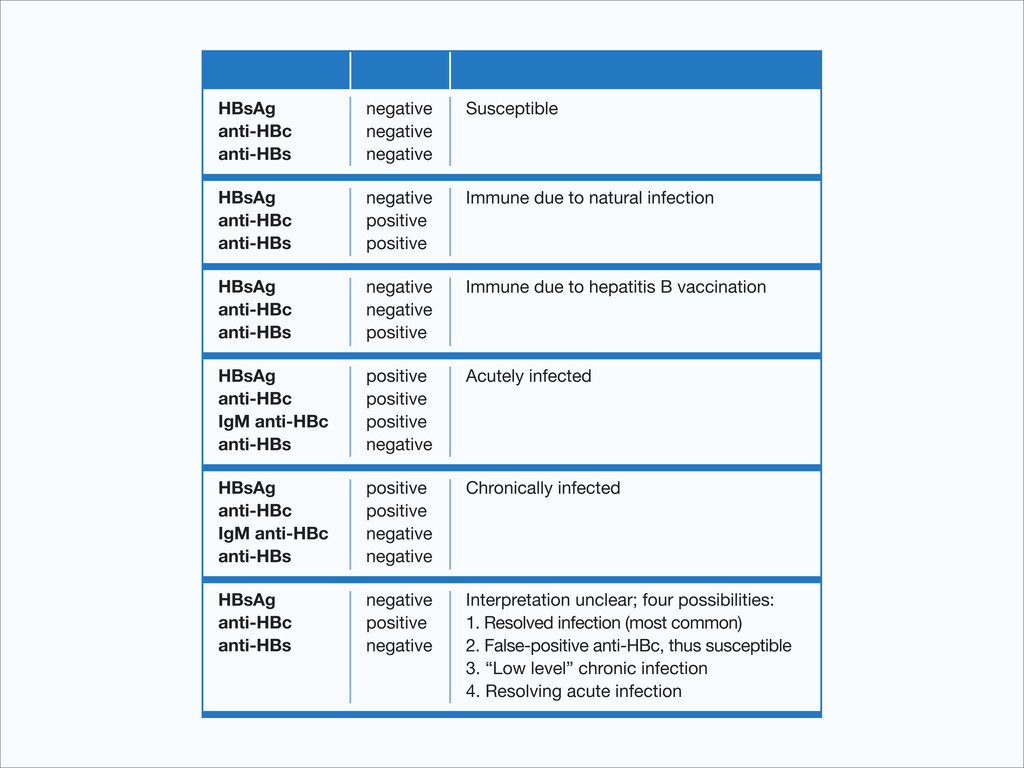
test positive 3 weeks after infection, but may take up to 6 months (repeat HIV testing in high-risk patients) NAAT/PCR is used in infants born to HIV- infected mothers. • HPV testing can be done on liquid cytology Pap smear samples (not yet in Sask.). HPV testing not widely available in Canada • Hep B testing is done by serological ELISA.
for 7 days, or Azithromycin 1g PO single dose, or in pregnancy, Amoxicillin 500 mg PO TID for 7 days! • Retest in 6 months (high rate of recurrence)! • Gonorrhea:! • Cefixime 800mg PO single dose, and Azithromycin 1g PO single dose (includes empiric therapy for Chlamydia)
PO BID for 10 days Recurrent lesions: Valacyclovir 500mg PO BID for 3 days Suppressive (episodes 6 times / year): Valacyclovir 500mg PO daily (example only, other antivirals work too.)
local Public Health Officer • Can be by the lab (done automatically for positive test results), or yourself as the physician! • Partner notification is also strongly encouraged: typically either by the infected patient or (with permission) by the physician (without naming the index case!)! • If the infected patient is not amenable to partner notification, explore reasons and/or report to public health.
all sexual health visits, with a stronger emphasis in particular populations: • Adolescents initiating sexual activities for the first time (preferably beforehand) • At-risk populations (sex workers, etc.)
Saskatchewan Communicable Disease Control Manual: http:// www.health.gov.sk.ca/cdc-section5 ! Saskatchewan Sexual Health - STI Information: http://www.health.gov.sk.ca/ sti-information ! At a Glance - HIV and AIDS in Canada: Surveillance Report to December 31st, 2012: http://www.phac-aspc.gc.ca/aids-sida/publication/survreport/ 2012/dec/index-eng.php ! HIV InSite UCSF: http://hivinsite.ucsf.edu/insite?page=basics-01-01 ! WHO Guidelines for the management of sexually transmitted infections: http://www.who.int/hiv/pub/sti/pub6/en/
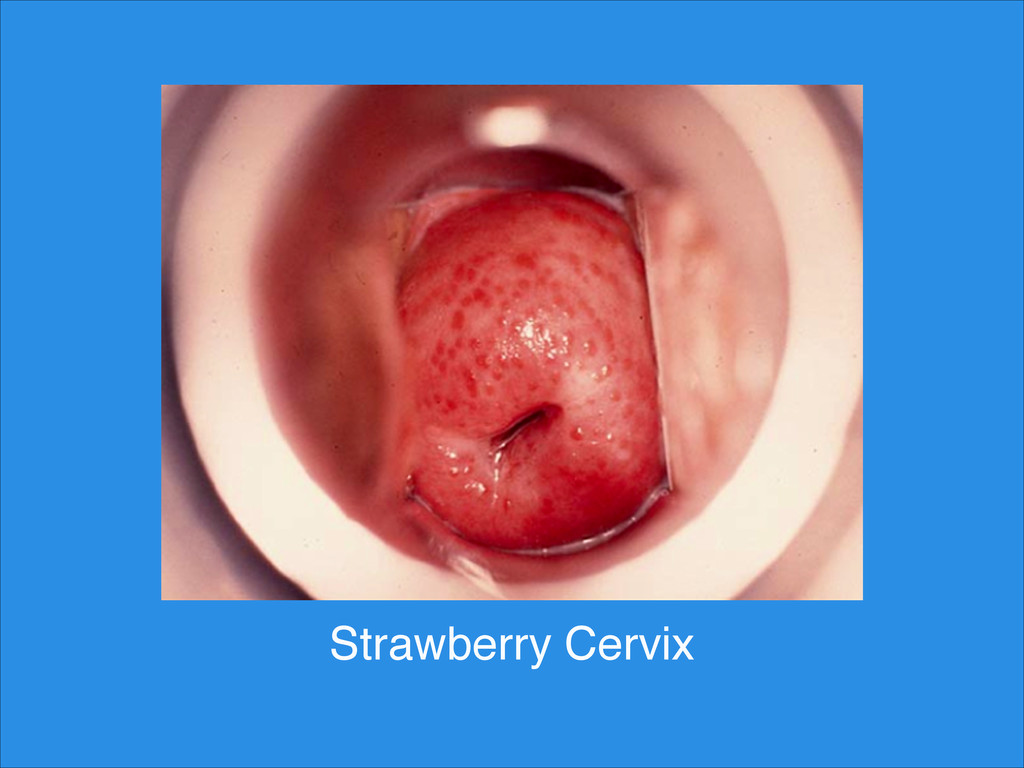
In Trich, vaginal pH is usually >4.5, and whiff test / KOH test is negative. Causative agents of urethritis:! • N. gonorrhoaeae, C. trachomatis, Trichomonas vaginalis, HSV, Mycoplasma genitalium, Ureaplasma urealyticum


 medrez
 kristinabergwall1
 irinanazarova
 bluesmoon
 lindahogenes
 gurzu
 shlominoach
 jacobtomlinson
 marktimemedia
 elsirapls
 jonoalderson
 mongodb
 yeseniaperezcruz