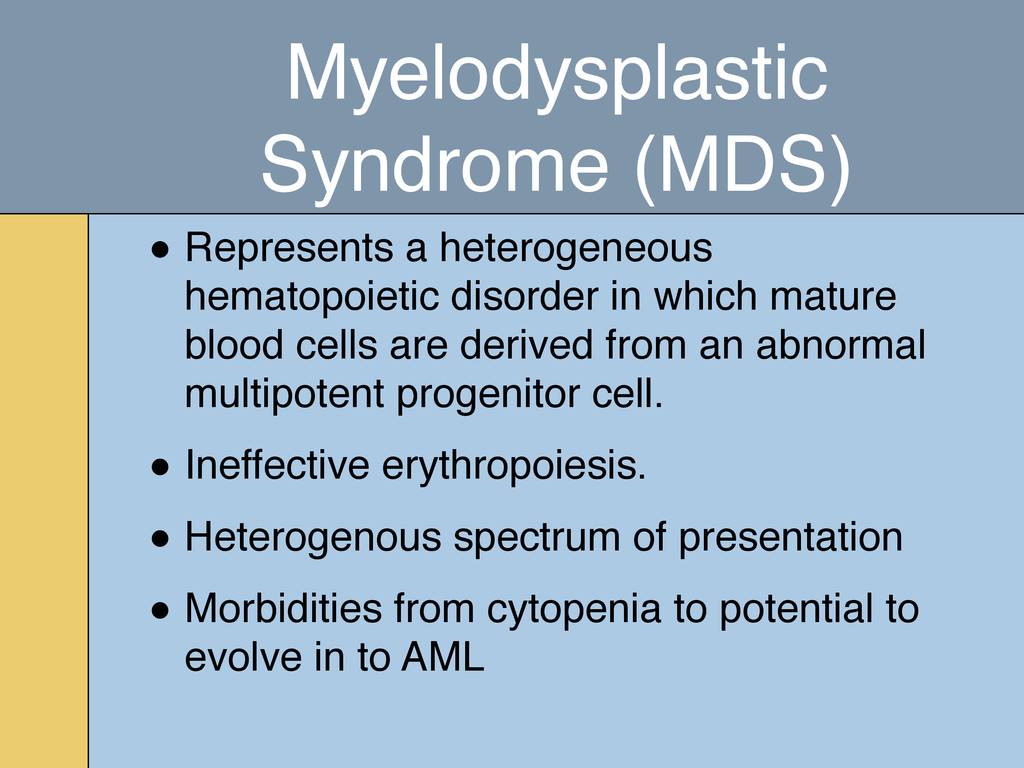
which mature blood cells are derived from an abnormal multipotent progenitor cell. • Ineffective erythropoiesis. • Heterogenous spectrum of presentation • Morbidities from cytopenia to potential to evolve in to AML
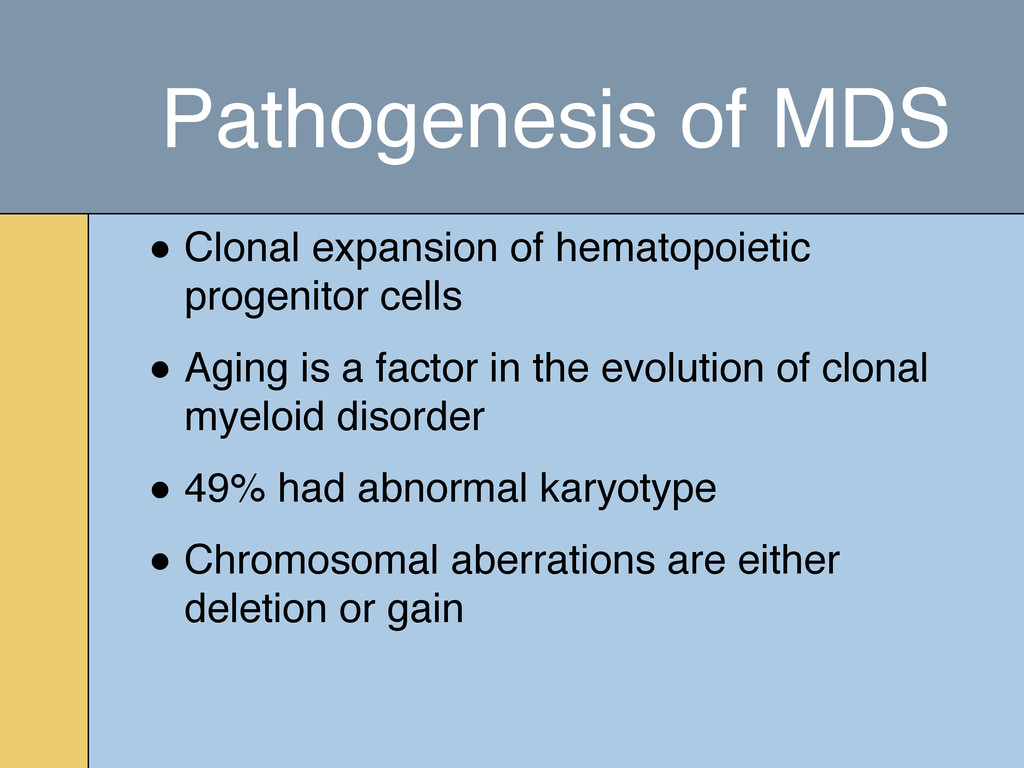
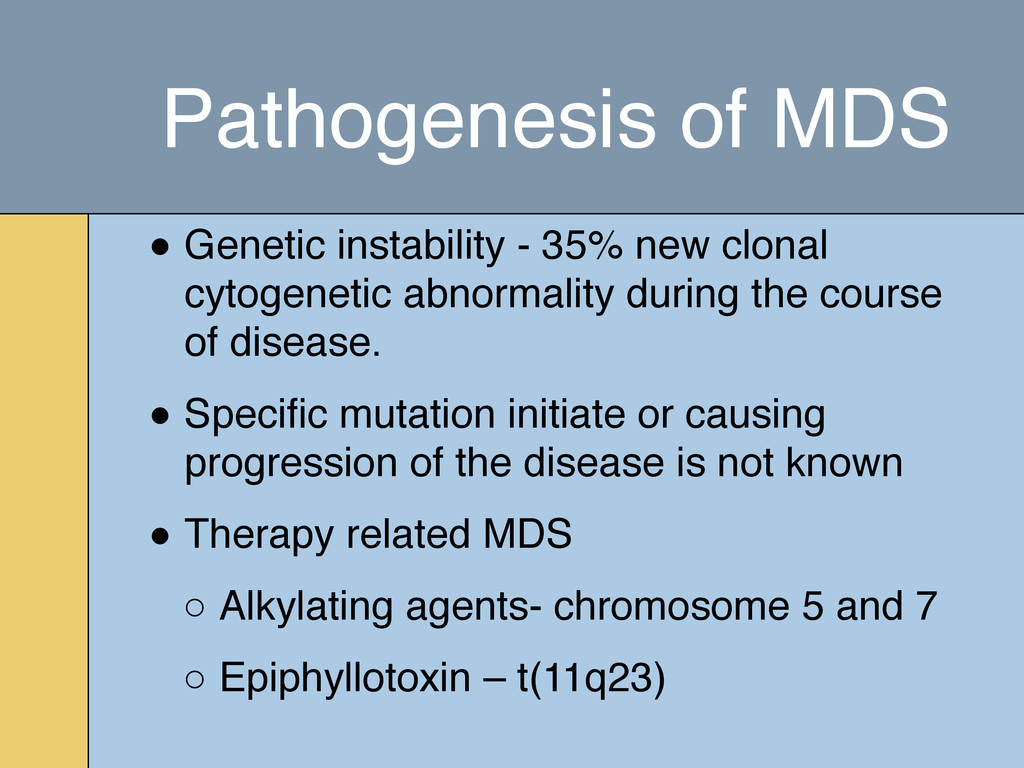
a factor in the evolution of clonal myeloid disorder • 49% had abnormal karyotype • Chromosomal aberrations are either deletion or gain Pathogenesis of MDS
cytogenetic abnormality during the course of disease. • Specific mutation initiate or causing progression of the disease is not known • Therapy related MDS ◦ Alkylating agents- chromosome 5 and 7 ◦ Epiphyllotoxin – t(11q23)
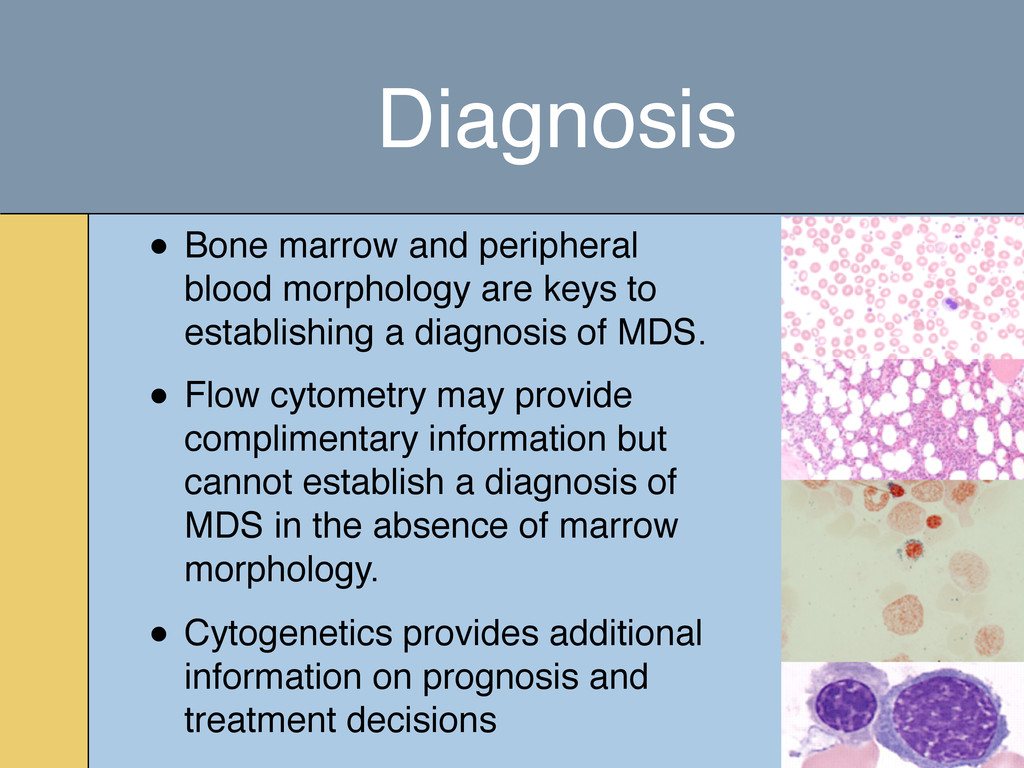
to establishing a diagnosis of MDS. • Flow cytometry may provide complimentary information but cannot establish a diagnosis of MDS in the absence of marrow morphology. • Cytogenetics provides additional information on prognosis and treatment decisions
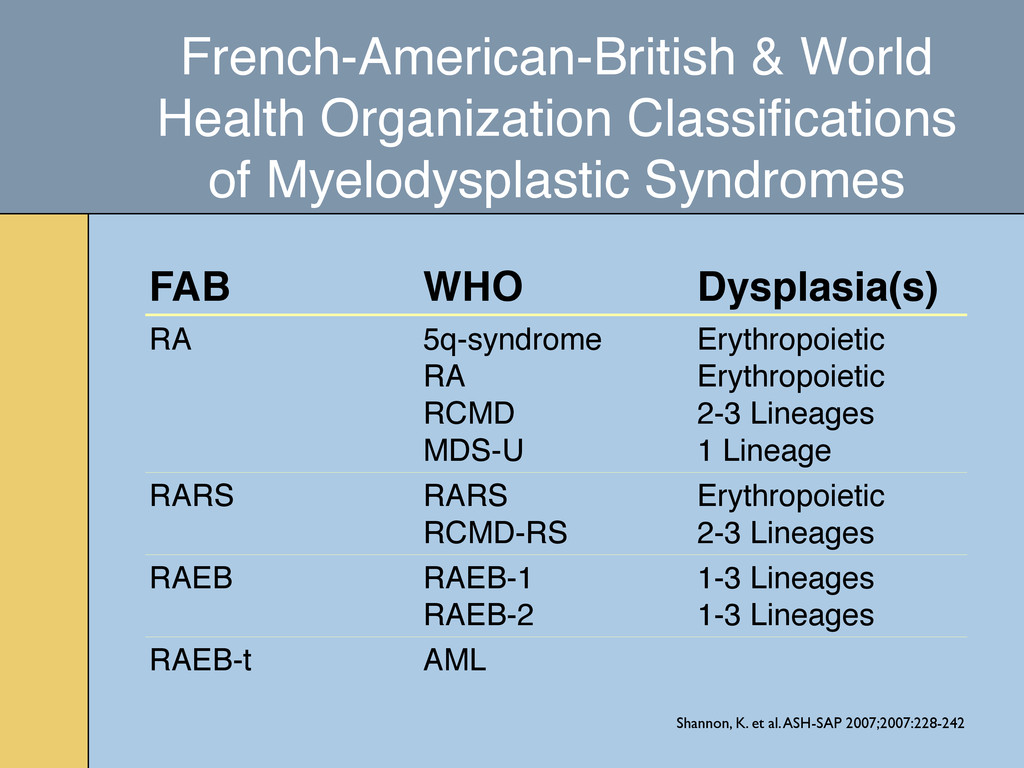
K. et al. ASH-SAP 2007;2007:228-242 FAB WHO Dysplasia(s) RA 5q-syndrome RA RCMD MDS-U Erythropoietic Erythropoietic 2-3 Lineages 1 Lineage RARS RARS RCMD-RS Erythropoietic 2-3 Lineages RAEB RAEB-1 RAEB-2 1-3 Lineages 1-3 Lineages RAEB-t AML
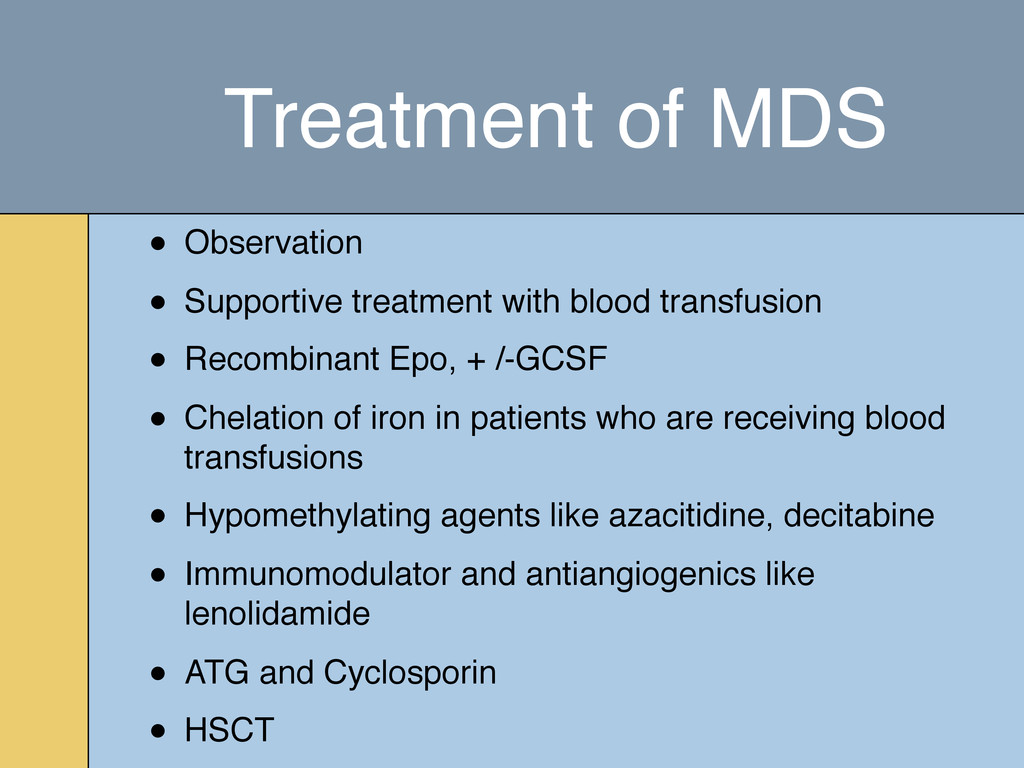
transfusion • Recombinant Epo, + /-GCSF • Chelation of iron in patients who are receiving blood transfusions • Hypomethylating agents like azacitidine, decitabine • Immunomodulator and antiangiogenics like lenolidamide • ATG and Cyclosporin • HSCT
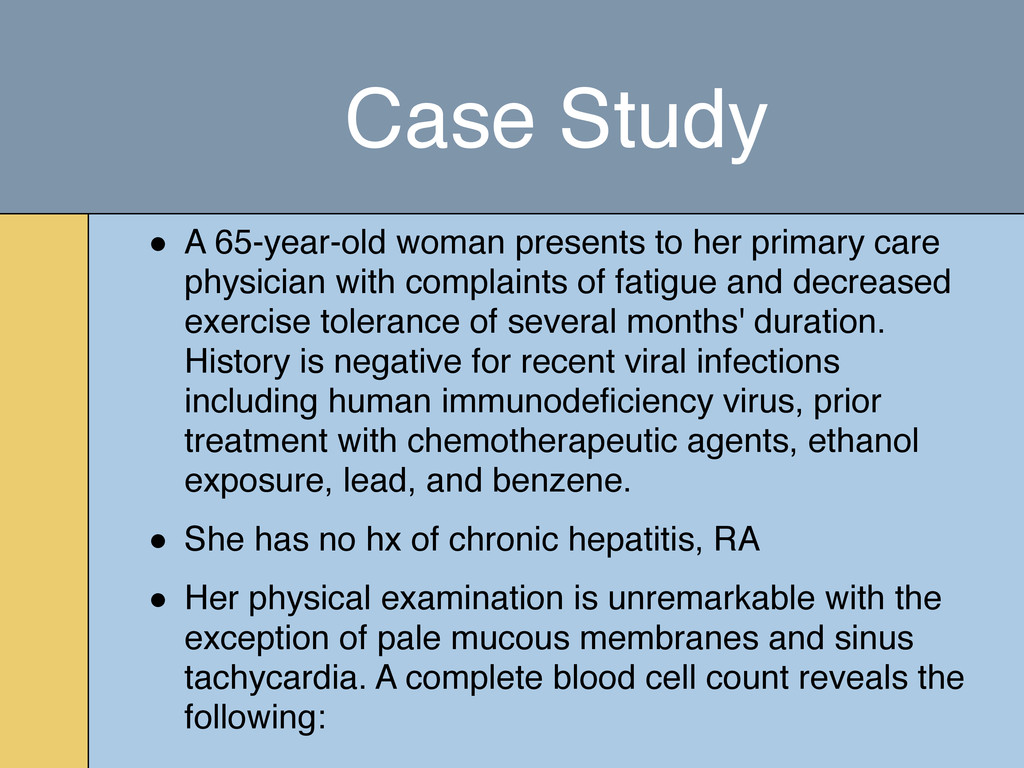
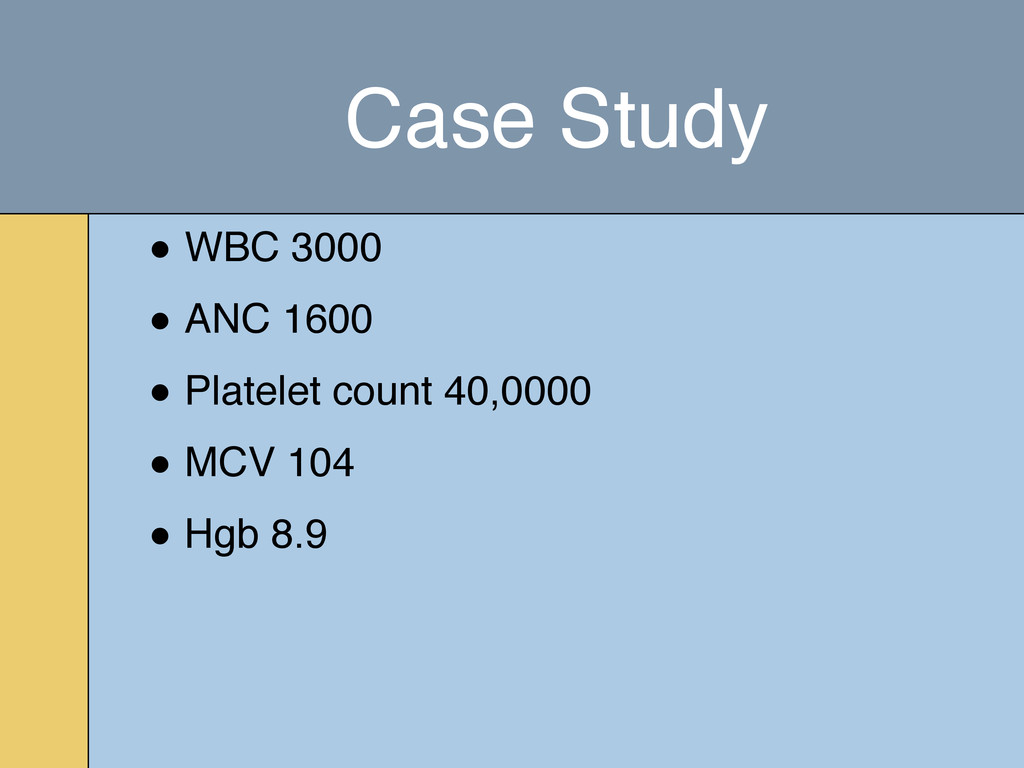
care physician with complaints of fatigue and decreased exercise tolerance of several months' duration. History is negative for recent viral infections including human immunodeficiency virus, prior treatment with chemotherapeutic agents, ethanol exposure, lead, and benzene. • She has no hx of chronic hepatitis, RA • Her physical examination is unremarkable with the exception of pale mucous membranes and sinus tachycardia. A complete blood cell count reveals the following:
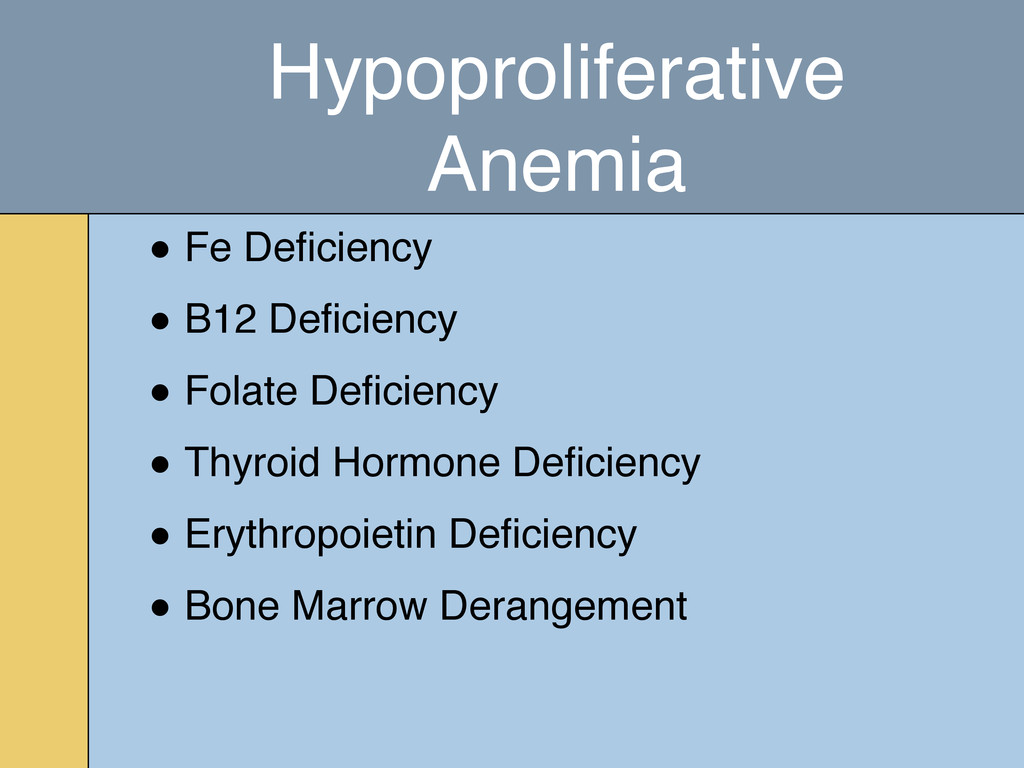
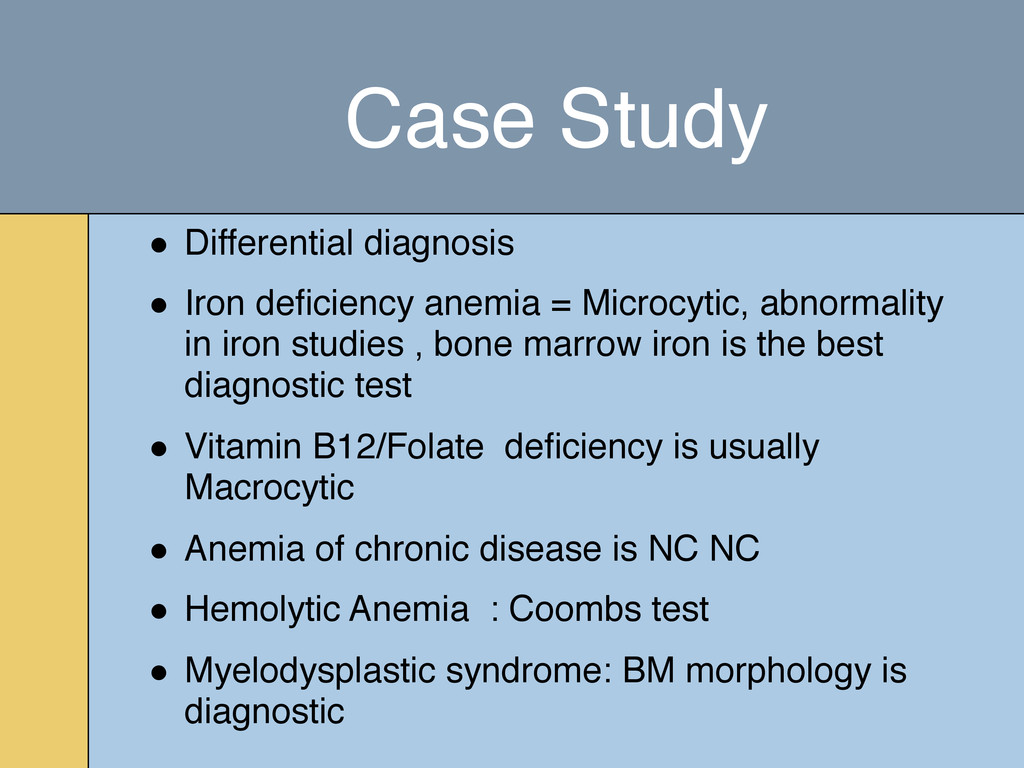
Microcytic, abnormality in iron studies , bone marrow iron is the best diagnostic test • Vitamin B12/Folate deficiency is usually Macrocytic • Anemia of chronic disease is NC NC • Hemolytic Anemia : Coombs test • Myelodysplastic syndrome: BM morphology is diagnostic
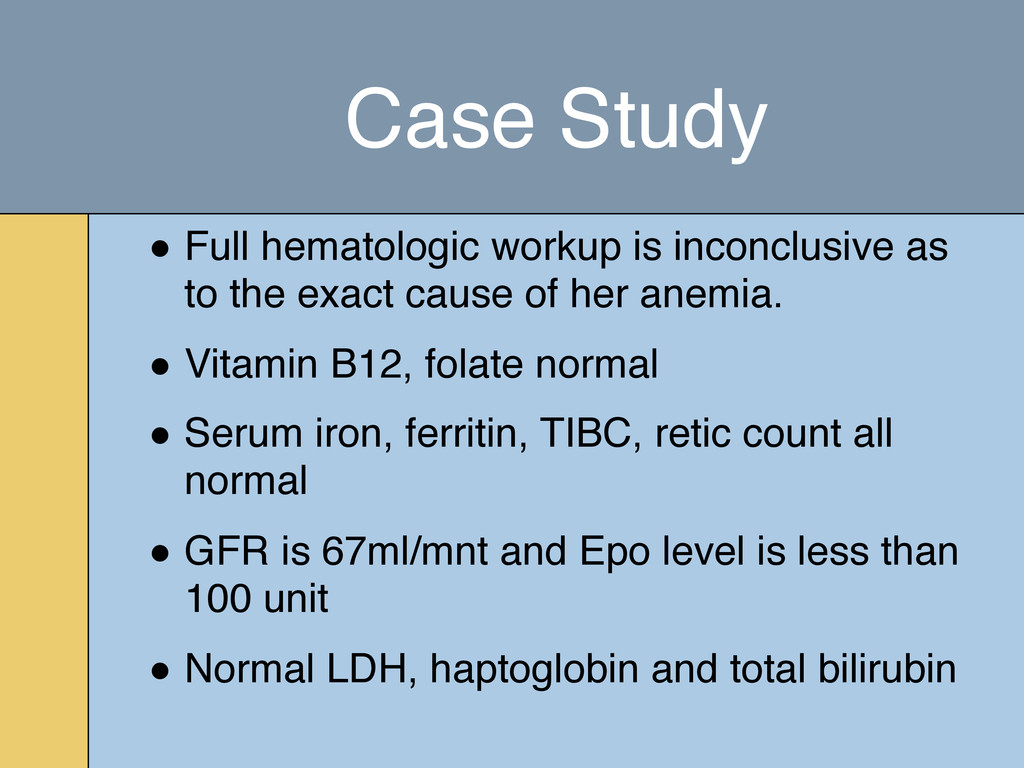
the exact cause of her anemia. • Vitamin B12, folate normal • Serum iron, ferritin, TIBC, retic count all normal • GFR is 67ml/mnt and Epo level is less than 100 unit • Normal LDH, haptoglobin and total bilirubin
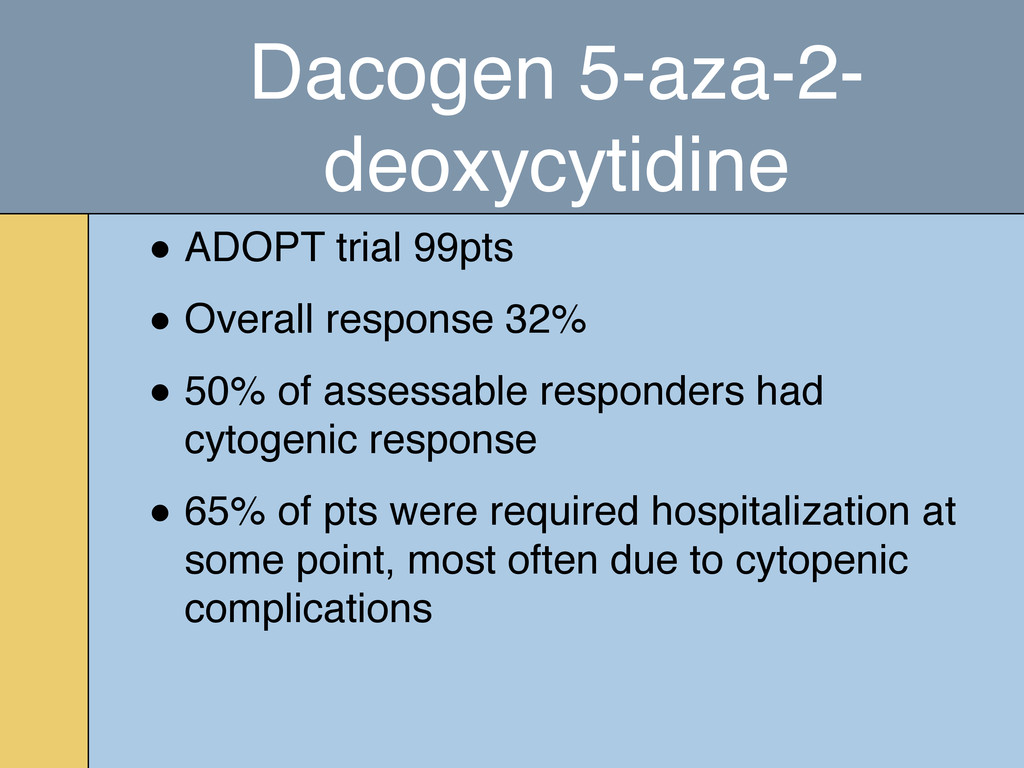
32% • 50% of assessable responders had cytogenic response • 65% of pts were required hospitalization at some point, most often due to cytopenic complications
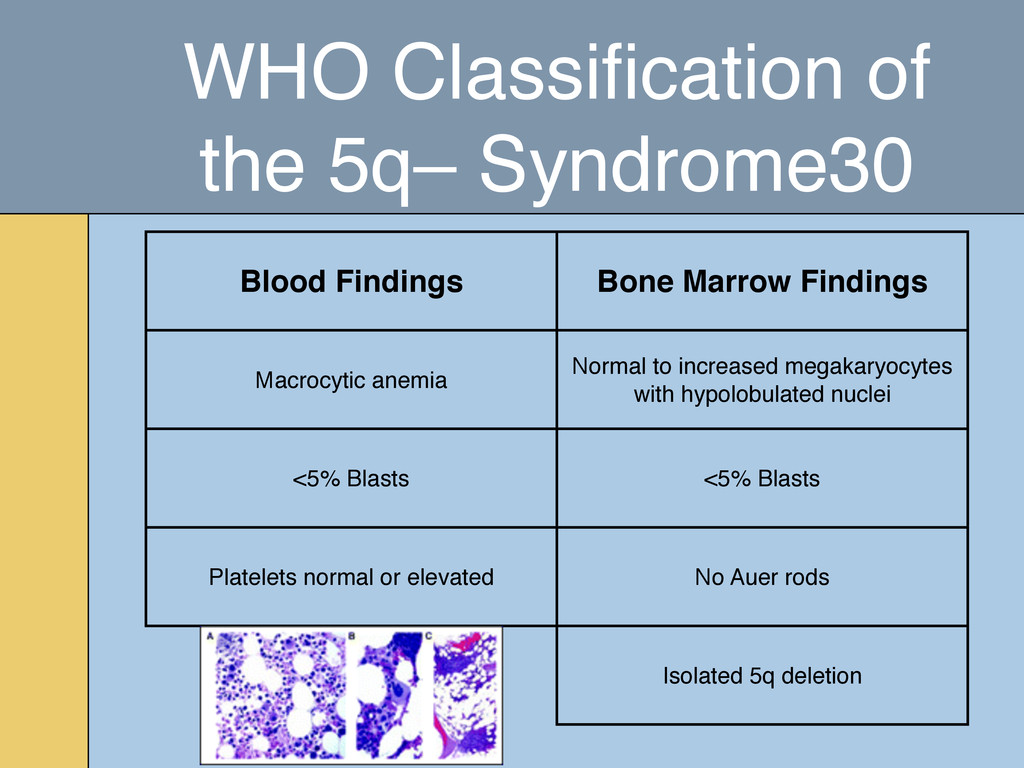
Findings Macrocytic anemia Normal to increased megakaryocytes with hypolobulated nuclei <5% Blasts <5% Blasts Platelets normal or elevated No Auer rods Isolated 5q deletion
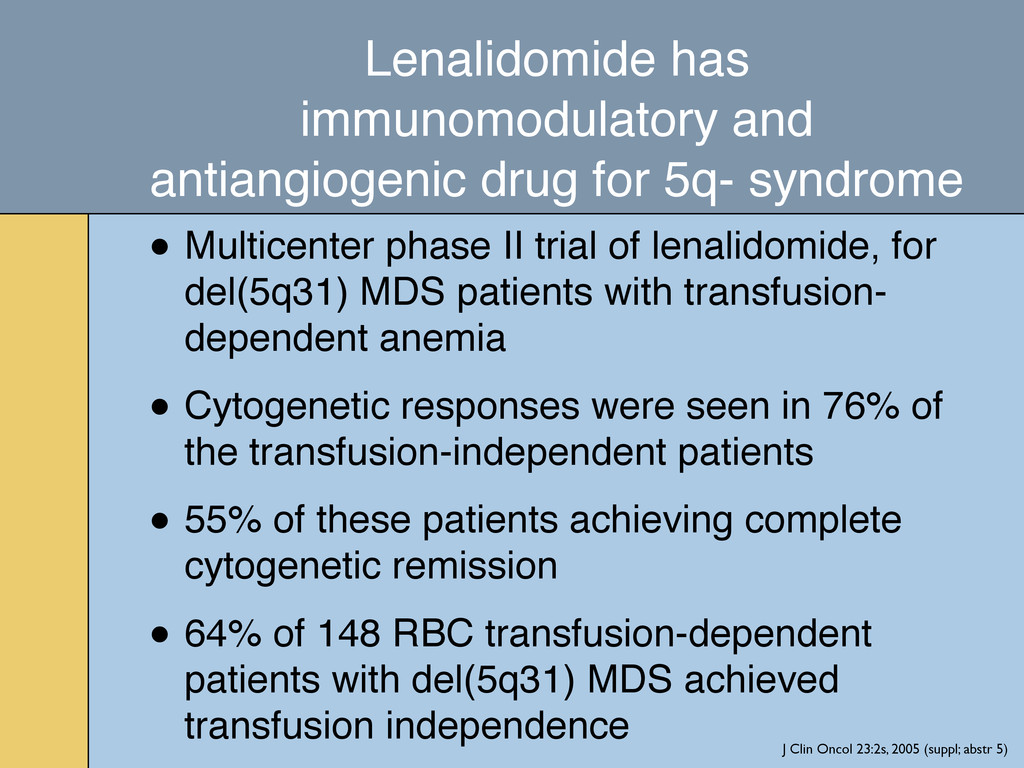
Multicenter phase II trial of lenalidomide, for del(5q31) MDS patients with transfusion- dependent anemia • Cytogenetic responses were seen in 76% of the transfusion-independent patients • 55% of these patients achieving complete cytogenetic remission • 64% of 148 RBC transfusion-dependent patients with del(5q31) MDS achieved transfusion independence J Clin Oncol 23:2s, 2005 (suppl; abstr 5)
Rate of transfusion independence was higher in patients with an isolated del(5q) than in del(5q) patients with additional chromosomal abnormalities 69% v/s 49% (P = .003). • The median response duration has not yet been reached, with a median follow-up of 9.3 months • Neutropenia and thrombocytopenia were the most common adverse events in this study, necessitating treatment interruption or dose reduction J Clin Oncol 23:2s, 2005 (suppl; abstr 5)
These results indicate that lenalidomide is highly effective in achieving durable transfusion independence and cytogenetic remission in MDS patients with del(5q31) J Clin Oncol 23:2s, 2005 (suppl; abstr 5)


 rwwmd
 codingconduct
 bcantrill
 tammielis
 aleyda
 ipullrank
 szymonslowik
 orderedlist
 speakerdeck
 reverentgeek
 jnunemaker
 mkilby
 katiecoart