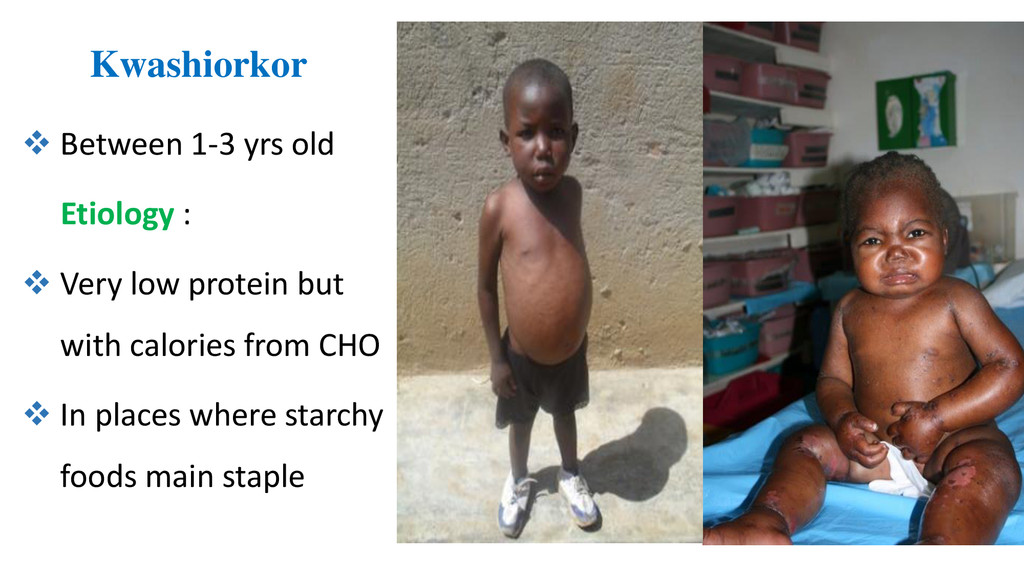
digests and assimilates to derive nutritive requirement for maintaining growth and physical well being. NUTRITION • Dynamic process concerned with ingestion, digestion, absorption and assimilation of food for nourishing the body.
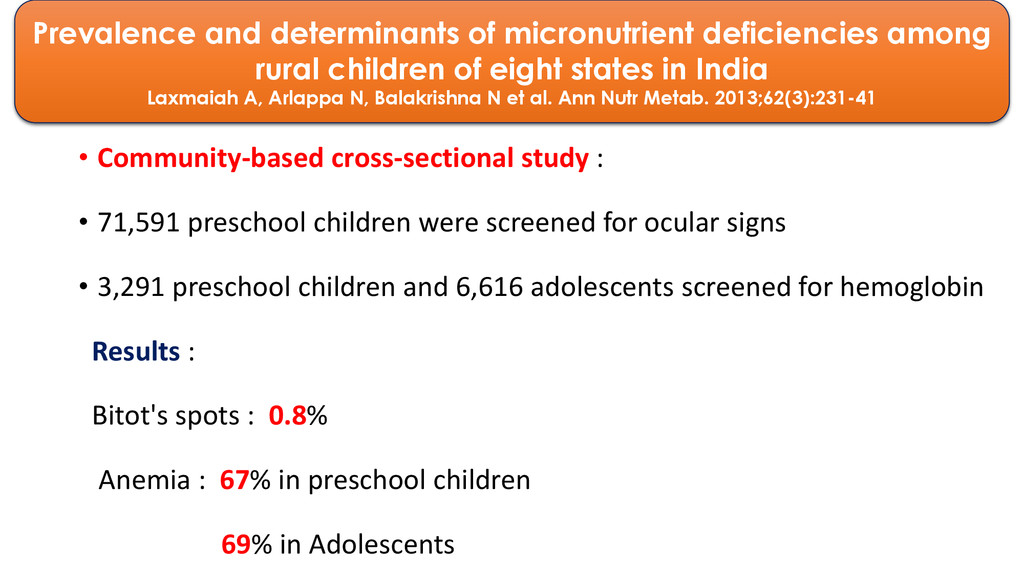
screened for ocular signs • 3,291 preschool children and 6,616 adolescents screened for hemoglobin Results : Bitot's spots : 0.8% Anemia : 67% in preschool children 69% in Adolescents Prevalence and determinants of micronutrient deficiencies among rural children of eight states in India Laxmaiah A, Arlappa N, Balakrishna N et al. Ann Nutr Metab. 2013;62(3):231-41
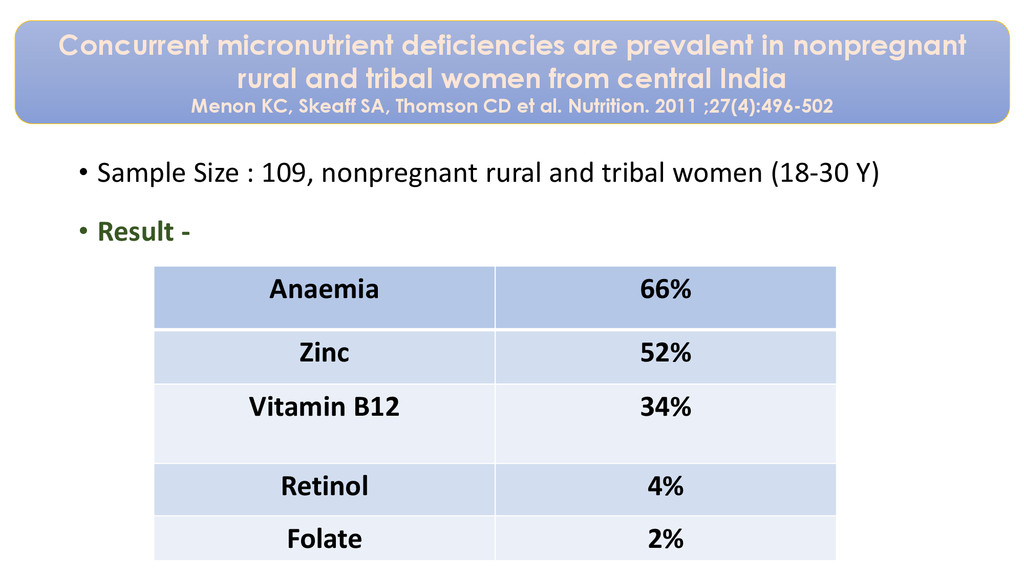
(18-30 Y) • Result - Concurrent micronutrient deficiencies are prevalent in nonpregnant rural and tribal women from central India Menon KC, Skeaff SA, Thomson CD et al. Nutrition. 2011 ;27(4):496-502 Anaemia 66% Zinc 52% Vitamin B12 34% Retinol 4% Folate 2%
organism in very small amounts for maintenance of vital processes essential for life. 1. Principal elements/macrominerals K, Ca, Mg, Na, P, S and Cl. 2. Trace elements/ microminerals Iron , Zinc, Copper, Selenium, Fluoride, Iodine, Cobalt, Molybdenum, Silicon,Nickel, Tin, Cromium
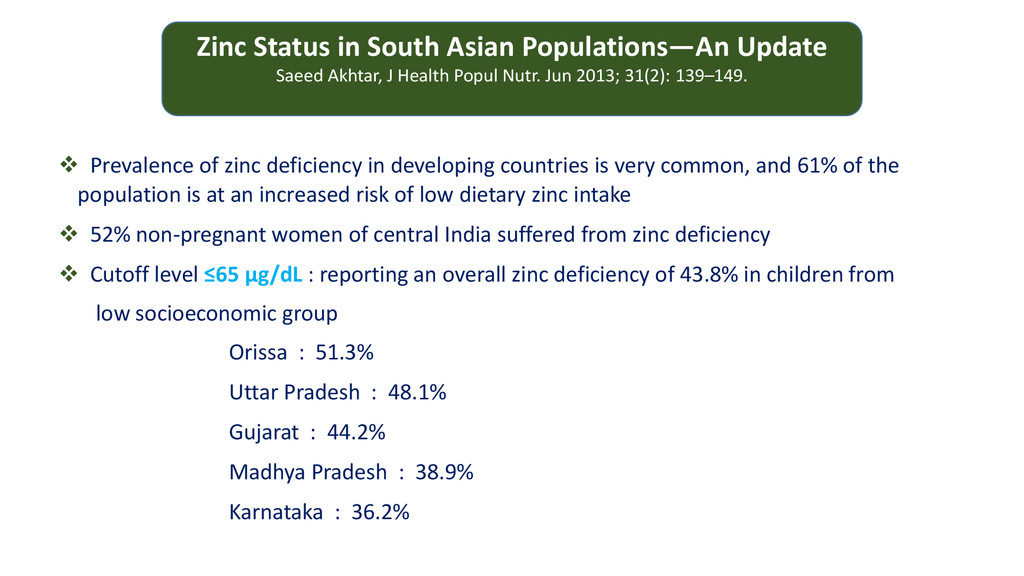
Health Popul Nutr. Jun 2013; 31(2): 139–149. Prevalence of zinc deficiency in developing countries is very common, and 61% of the population is at an increased risk of low dietary zinc intake 52% non-pregnant women of central India suffered from zinc deficiency Cutoff level ≤65 μg/dL : reporting an overall zinc deficiency of 43.8% in children from low socioeconomic group Orissa : 51.3% Uttar Pradesh : 48.1% Gujarat : 44.2% Madhya Pradesh : 38.9% Karnataka : 36.2%
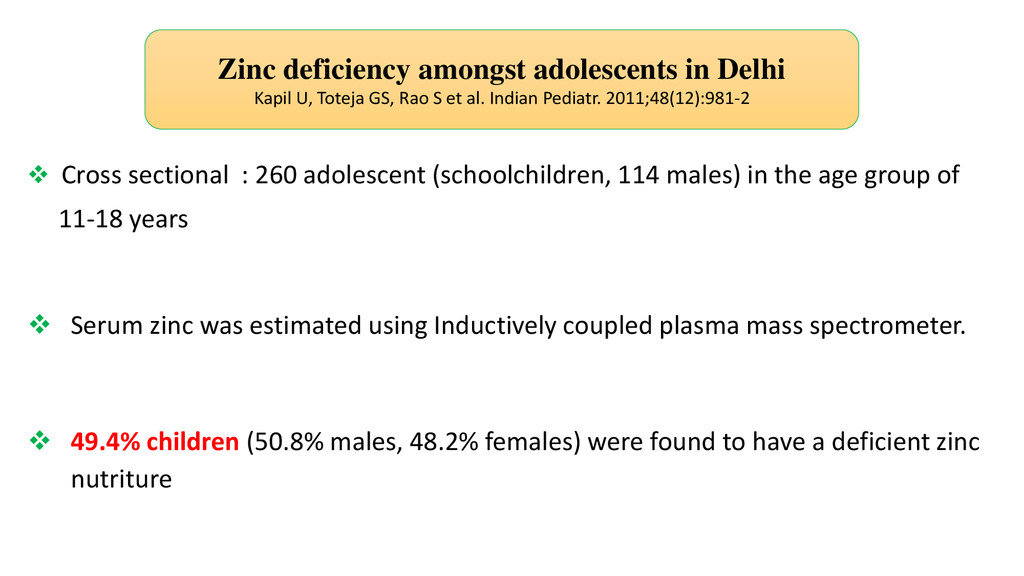
the age group of 11-18 years Serum zinc was estimated using Inductively coupled plasma mass spectrometer. 49.4% children (50.8% males, 48.2% females) were found to have a deficient zinc nutriture Zinc deficiency amongst adolescents in Delhi Kapil U, Toteja GS, Rao S et al. Indian Pediatr. 2011;48(12):981-2
variety of metabolic pathways and cellular functions Adequate zinc levels are also important for wound healing and for T-cell, neutrophil, and natural killer cell function Meat & fish are best dietery sources Human breast milk contains very high levels of zinc during the first 1 to 2 months of lactation Also contains a zinc-binding ligand that increases the bioavailability
skin, muscles and prostate, there is no free exchange of stored zinc Deficiency : 1. Hereditary type 2. Non-hereditary type Low grade, marginal, nonhereditary zinc deficiency is far more common I. Early weaning II. Excessive calcium intake III. Phytate in diet IV. Cutaneous burn, Exfoliative dermatitis V. Nephrotic syndrome
breast milk to formula or cereal, which have lower zinc bioavailability than breast milk Defect in intestinal zinc transporter, the human ZIP4 protein Genetic locus for acrodermatitis entropathica on chromosome 8q24.3
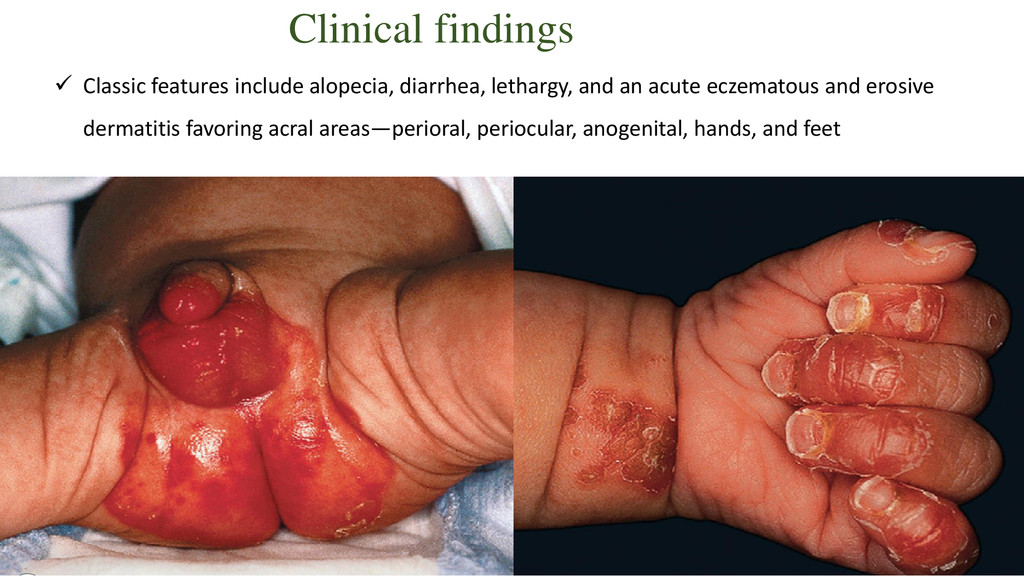
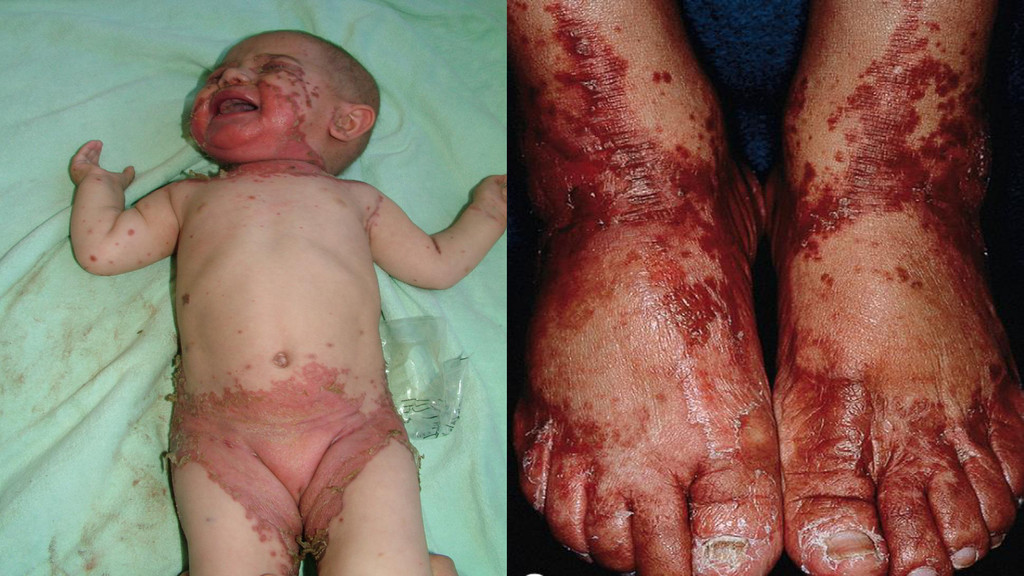
crusted border Delayed wound healing, acute paronychia, conjunctivitis, blepharitis, and photophobia may also be observed Predisposition to infection with Candida and bacterial infections Chronic deficiency : psoriasiform dermatitis involving the hands and feet and, occasionally, the knees Growth retardation, hypogonadism, dysguesia, impaired dark adaptation
for diagnosis If plasma zinc level is equivocal and the diagnosis is uncertain, skin biopsy may be helpful Biopsy : Psoriasiform hyperplasia with confluent parakeratosis, spongiosis and pallor of the upper epidermis, focal dyskeratosis, and variable epidermal atrophy Treatment : 0.5 to 1.0 mg/kg of elemental zinc given as one to two daily doses Patients with AE require lifelong treatment
oxidation- reduction reactions, collagen synthesis, and as a co-factor for various enzymes Animal sources, dried fruits, green leafy vegetables, jaggery are best sources Iron deficiency remains an international problem that crosses socioeconomic and ethnic divide Groups at high risk include infants, menstruating females, and individuals with chronic GI bleeds
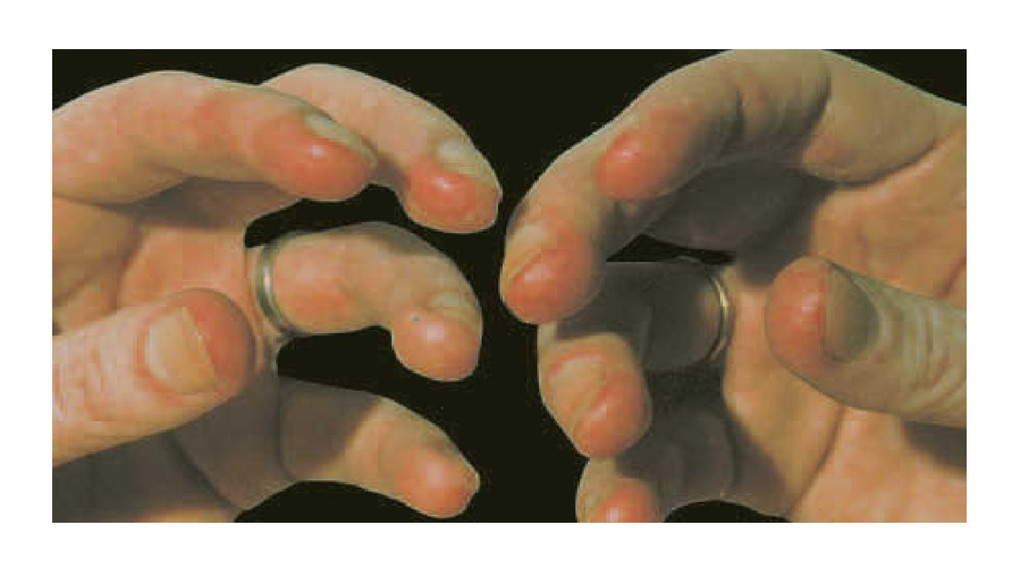
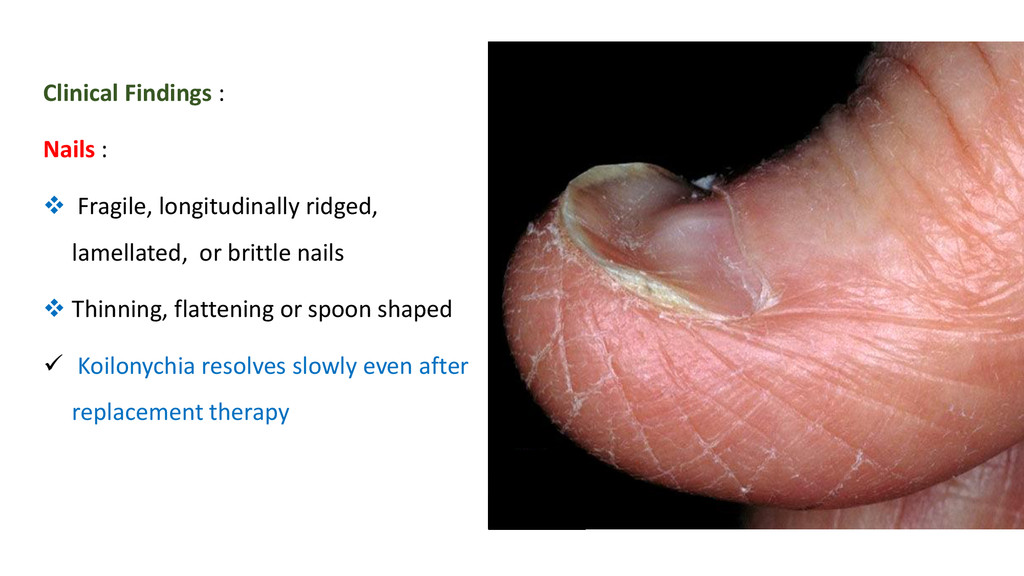
split hair shafts, likely caused by impaired keratin production Heterochromia of black scalp hair with alternating segments of dark brown, white, and silver bands Role of iron deficiency in hair loss : A controversy J Am Acad Dermatol 2006 ;54(5):824-44
and absent or atrophied tongue papillae. Generalized pruritus of variable severity has been reported in some individuals with iron deficiency Treatment involves appropriate iron supplementation.
changes of the skin are seen. Cutaneous hyperpigmentation is seen in more than 90% of patients with idiopathic hemochromatosis Hyperpigmentation is one of the earliest signs of the disease, tends to be most pronounced on sun-exposed skin. 1/3 shows external genital hyperpigmentation and 1/5 shows flexural folds, scars, and nipple areolae hyperpigmentation
indispensable for the normal functions of the body. No direct function as an energy source or as structural tissue components. Act as coenzymes in various enzyme systems. Fat Soluble Vitamins Vitamin A, D, E, K Water Soluble Vitamins Vitamin B & C
Retinal, the aldehyde form, functions in vision Retinoic acid, the physiologically most important vitamin A metabolite, regulates many genes involved in biologic activities of cells Functions : 1. Retinal is in photosensitive pigment in both rods (rhodopsin) & cones (iodopsin) 2. Needed for lysosomal membrane stability 3. Involved in keratinization, cornification, bone development & cell growth & reproduction
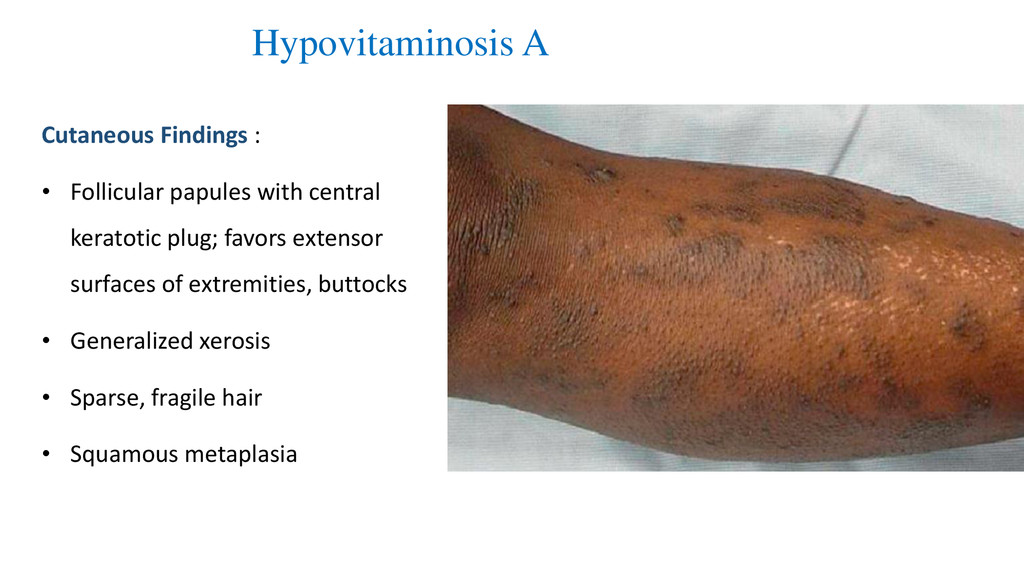
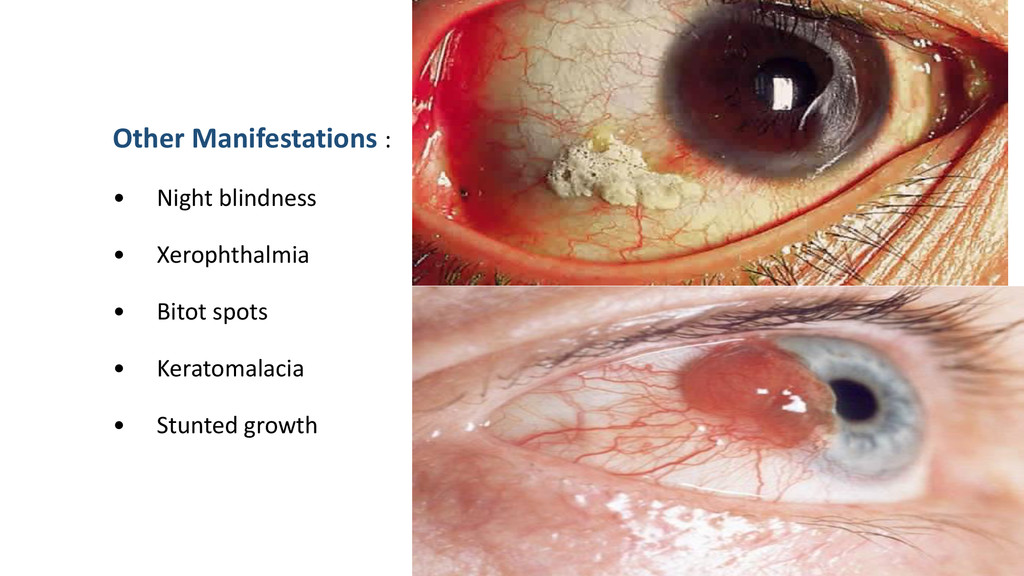
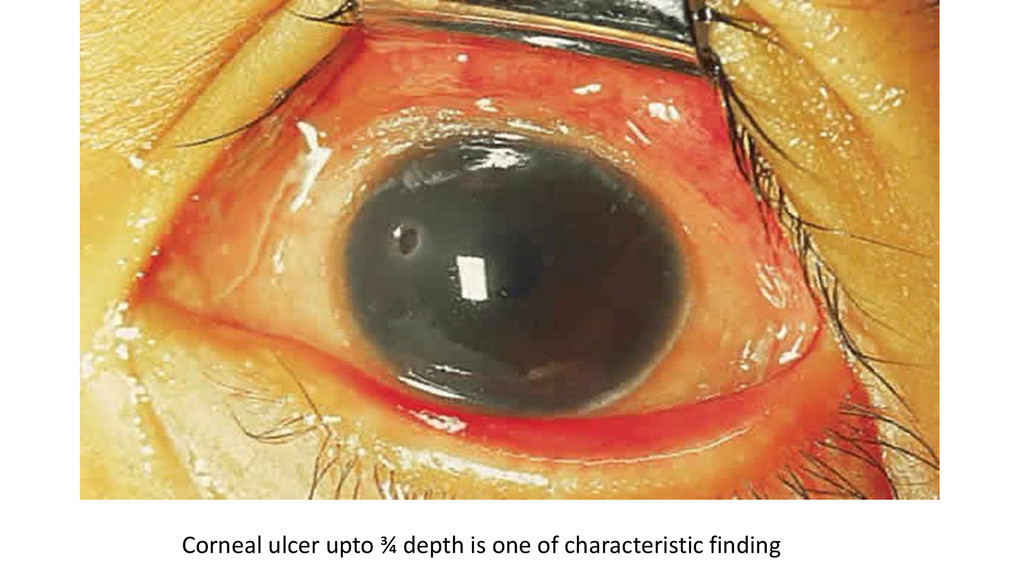
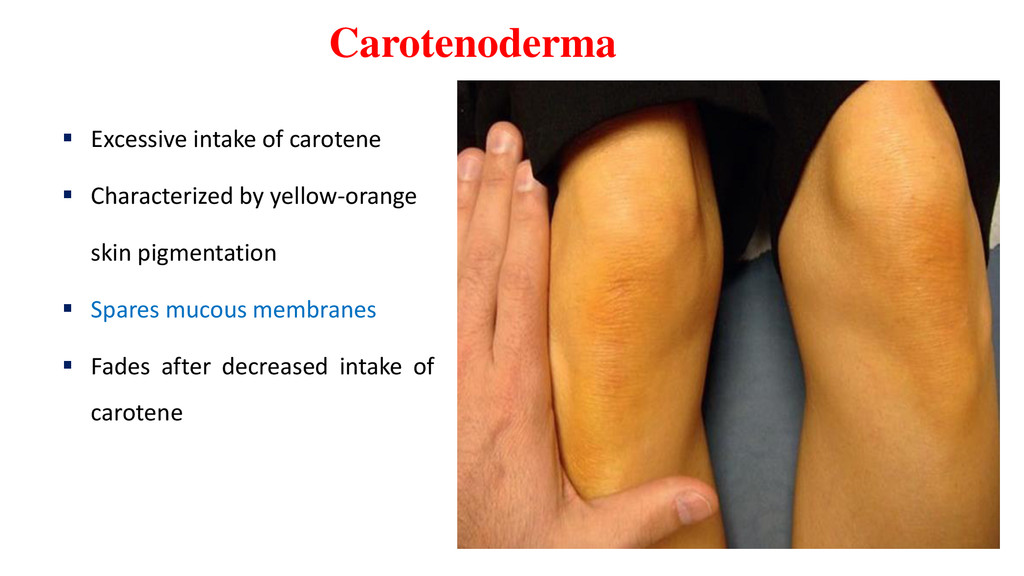
(liver, fish, eggs, milk, butter) Carotenoids (e.g., beta-carotene) : yellow and leafy green vegetables (carrots, squash and spinach) Deficiency : Poor absorption as in low-fat diet, malabsorption syndromes, etc. Low protein intake resulting in deficient carriers Increased excretion as in cancer & UTI
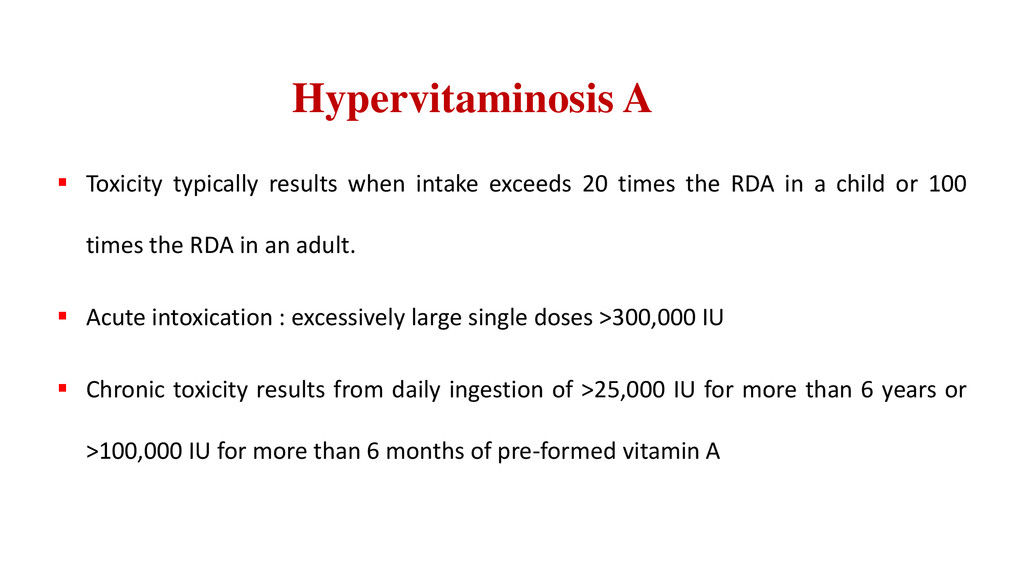
times the RDA in a child or 100 times the RDA in an adult. Acute intoxication : excessively large single doses >300,000 IU Chronic toxicity results from daily ingestion of >25,000 IU for more than 6 years or >100,000 IU for more than 6 months of pre-formed vitamin A
desquamation and fissuring of the lips and angles of the mouth. Infants: nausea & vomiting, drowsiness or irritability with signs of increased ICP Adults: drowsiness, irritability, headache & vomiting Chronic intoxication Early cutaneous sign is dryness of the lips Diffuse, dry, pruritic, scaly skin with peeling of palms and soles, Alopecia, follicular hyperkeratosis, and hyperpigmentation of the face and neck.
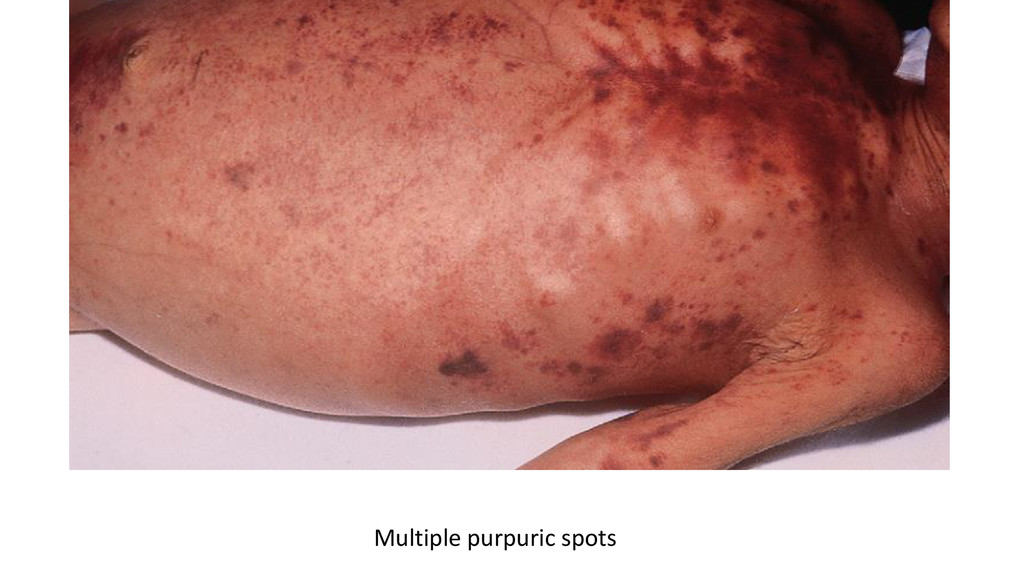
ecchymoses and purpura Bleeding in the newborn from the cord or circumcision site GIT bleeding, hematuria & intracranial hemorrhage Anemia & shock may ensue from severe blood loss Treatment Acute treatment of vitamin K deficiency with hemorrhage is with fresh frozen plasma to replace deficient coagulation factors. Parenteral or intramuscular 5 to 10 mg vitamin K per day
from whole grains, enriched bread products, dried peas and beans, potatoes, and fish Polished rice eliminates the thiamine containing husk Deficiency show up in quickly growing tissues such as epithelium and cells using lots of energy like nerve cells and cardiac muscles
and prompt response to thiamine administration Dry beriberi : peripheral neuritis with neurological disorders Glossitis and glossodynia Treated with 50-100mg IV or IM thiamine for 7-14 days
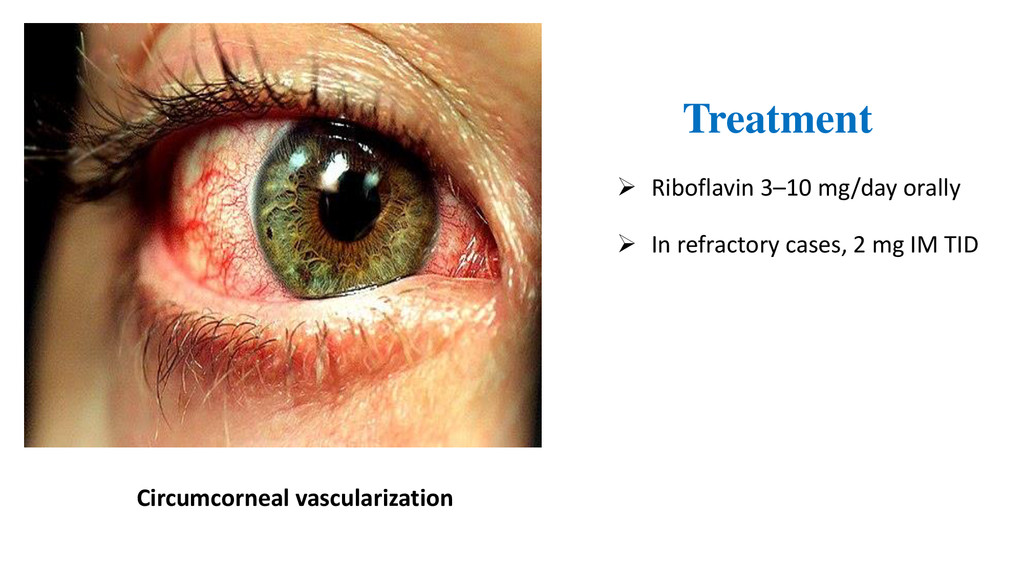
cellular respiration and oxidative phosphorylation Source : Dairy products, meat, nuts, eggs, whole grain and enriched bread products, fatty fish, and green leafy vegetables Visible light phototherapy causes photodecomposition of riboflavin Chlorpromazine and other tricyclic drugs inhibit transport of riboflavin in the gastrointestinal tract
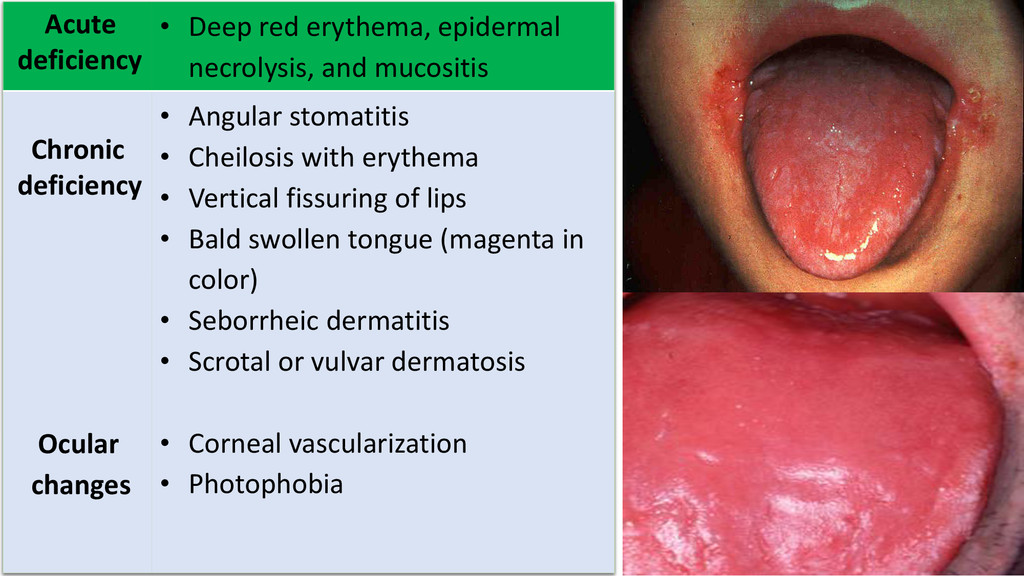
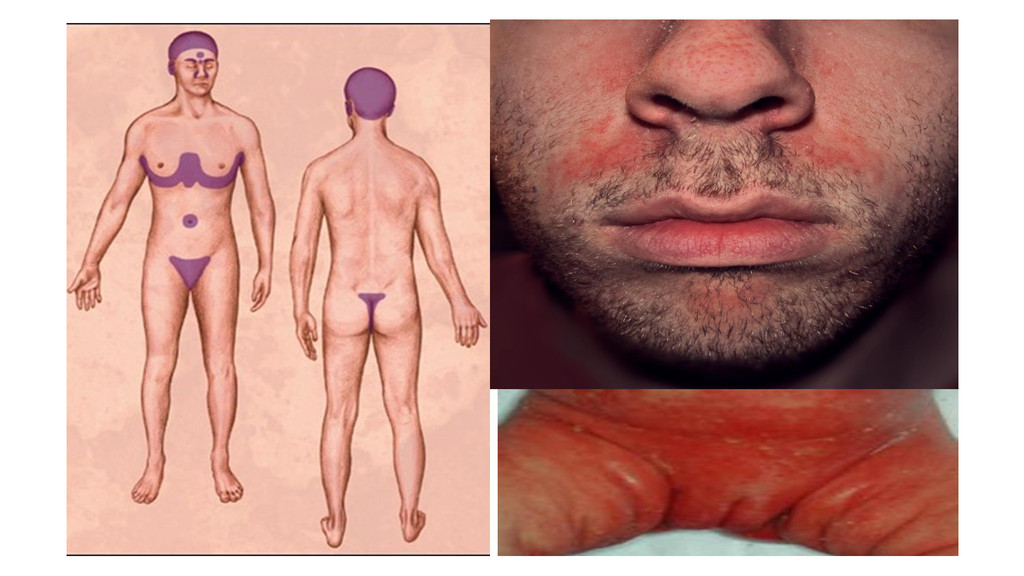
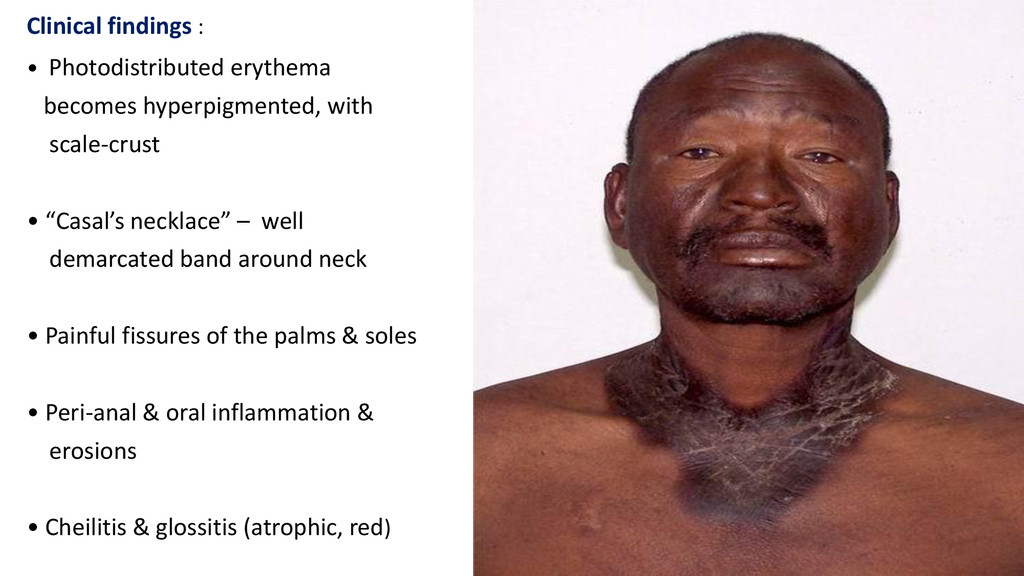
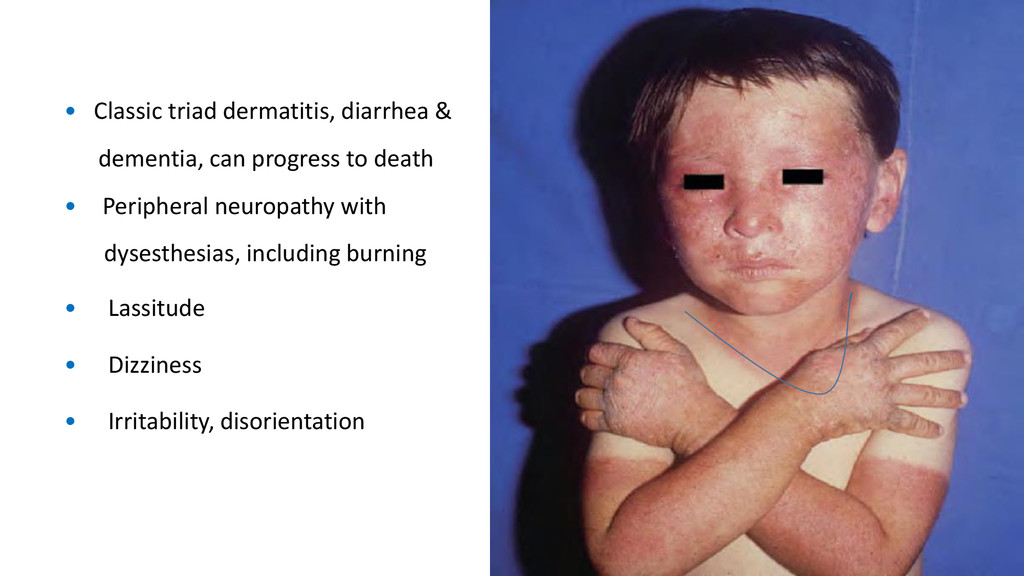
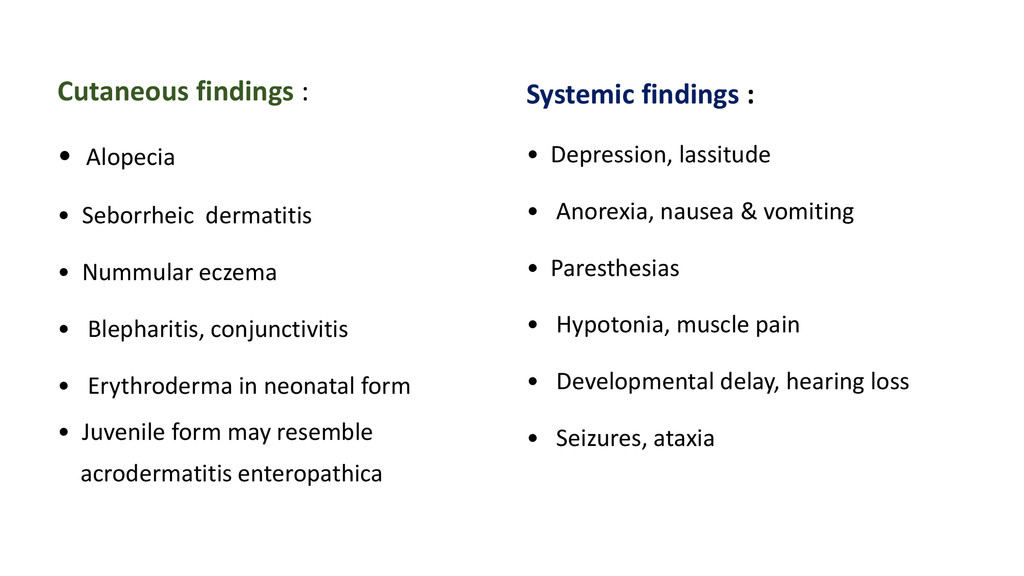
• “Casal’s necklace” – well demarcated band around neck • Painful fissures of the palms & soles • Peri-anal & oral inflammation & erosions • Cheilitis & glossitis (atrophic, red)
Glossitis – atrophic with ulceration • Conjunctivitis • Intertrigo • Neurologic symptoms including peripheral neuropathy, somnolence, confusion & seizures Treatment : • Pyridoxine 50–100 mg/day PO to prevent neuropathy • 100 mg/day IV in those with seizures
metabolism • Plays role in gluconeogenesis • Animal sources like liver, meat and eggs are best sources • Synthesized in gut by bacterial flora Deficiency : Excessive raw egg white consumption Chronic anticonvulsant therapy Inborn error of metabolism
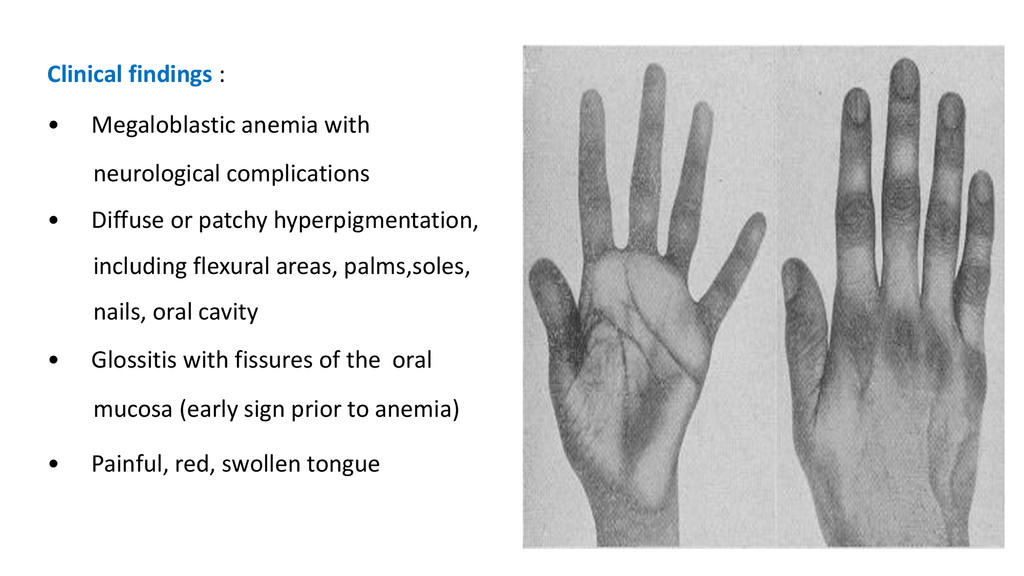
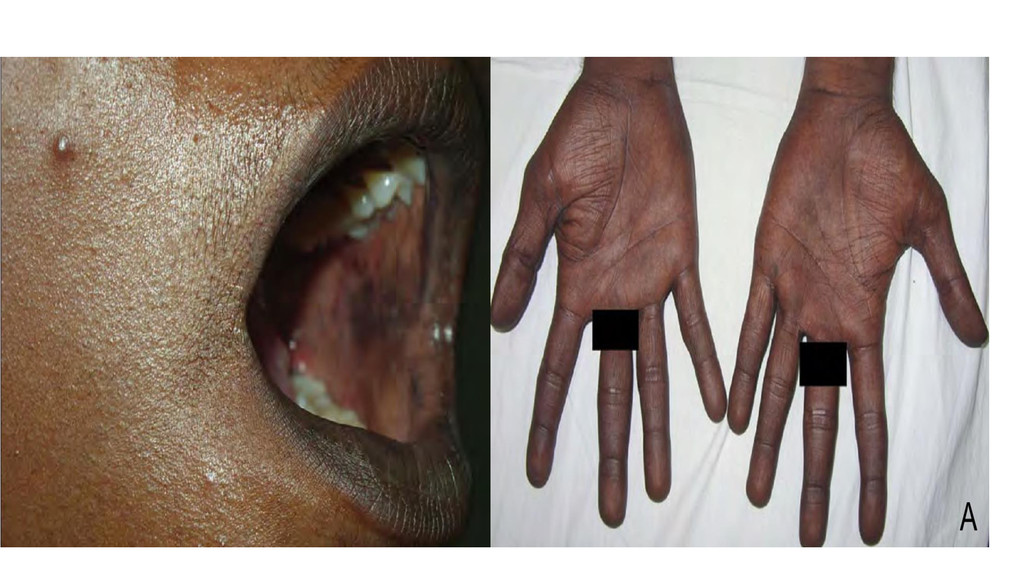
Diffuse or patchy hyperpigmentation, including flexural areas, palms,soles, nails, oral cavity • Glossitis with fissures of the oral mucosa (early sign prior to anemia) • Painful, red, swollen tongue
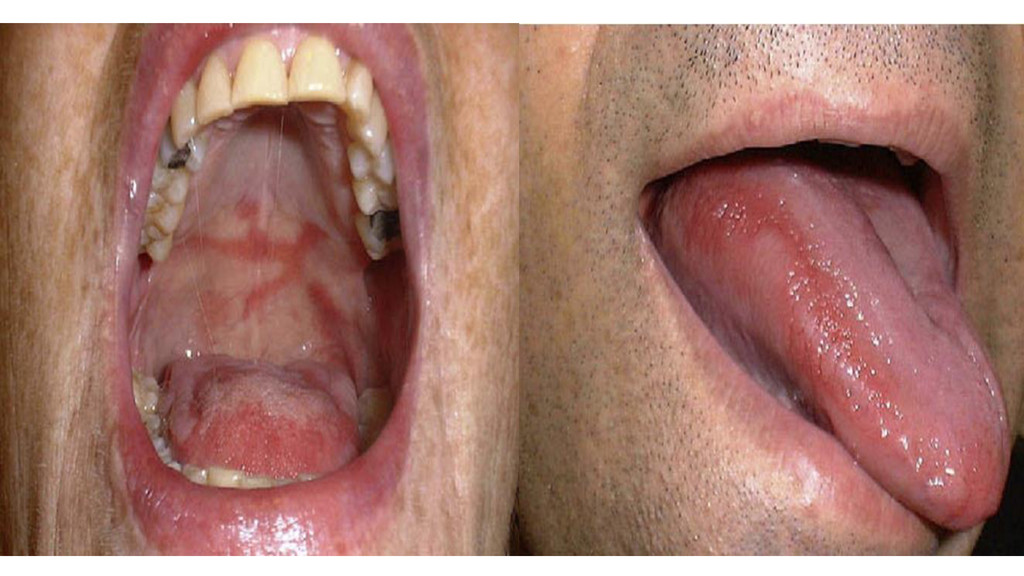
with vitiligo, alopecia areata Treatment Oral supplementation is not recommended due to poor absorption 30 μg administered via the IM or SC route for 5 to 10 days, followed by 100 to 200 μg per month is recommended
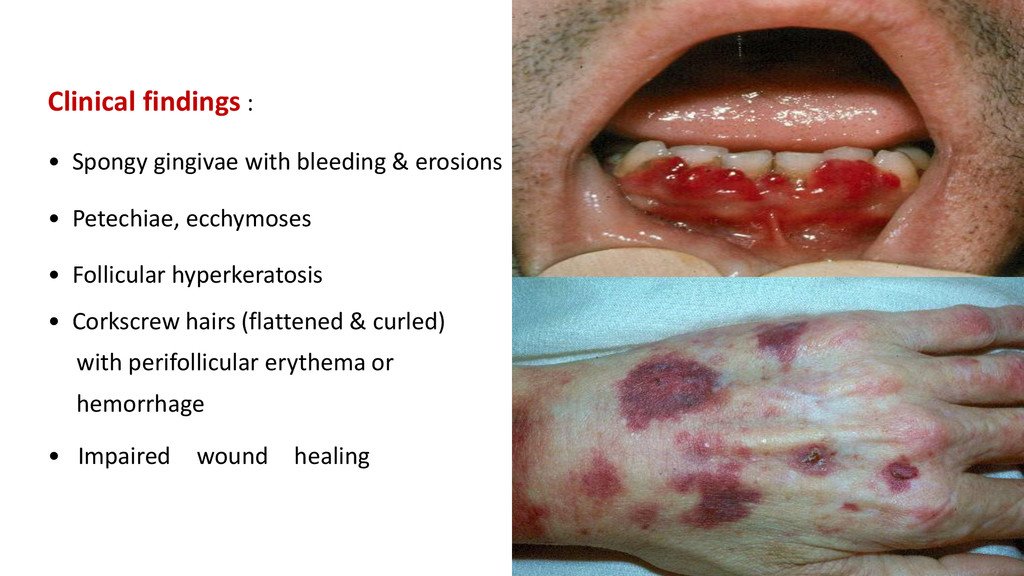
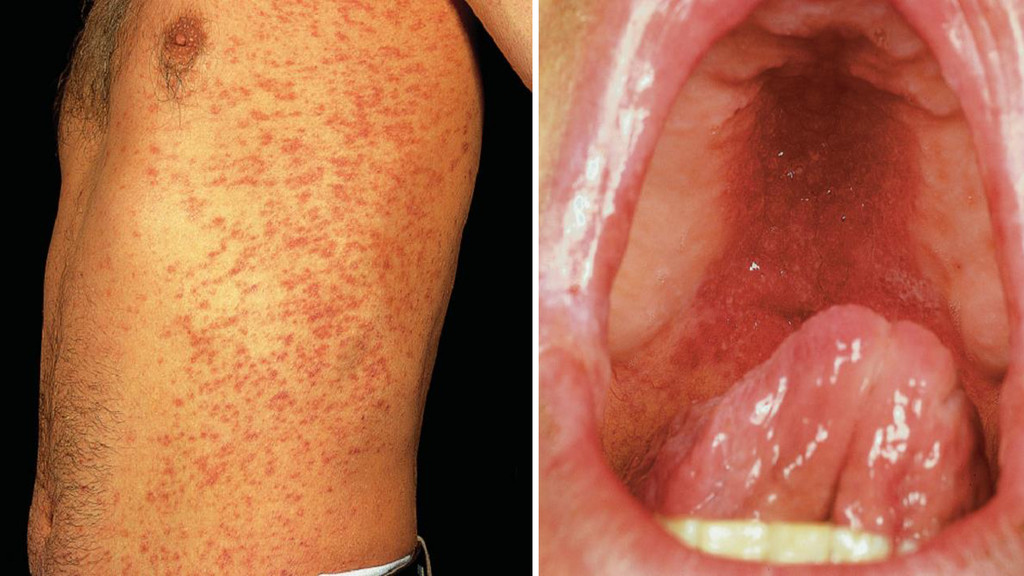
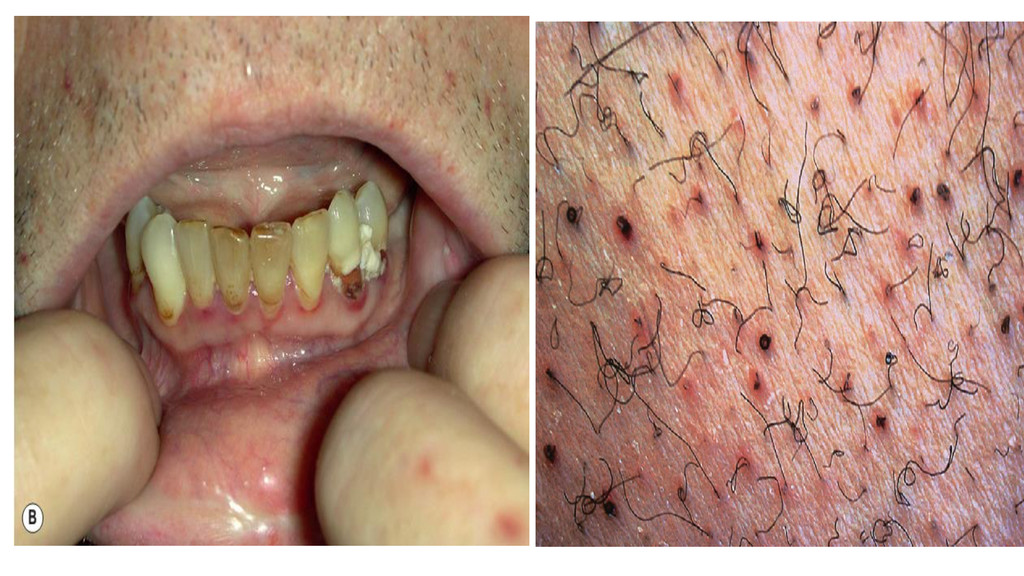
e.g. lysyl hydroxylase • Antioxidant • Iron absorption • Folate metabolism (folic acid to active form folinic acid) Dietery Source : Fresh fruits & vegetables Deficient intake for as few as 3 months can lead to scurvy
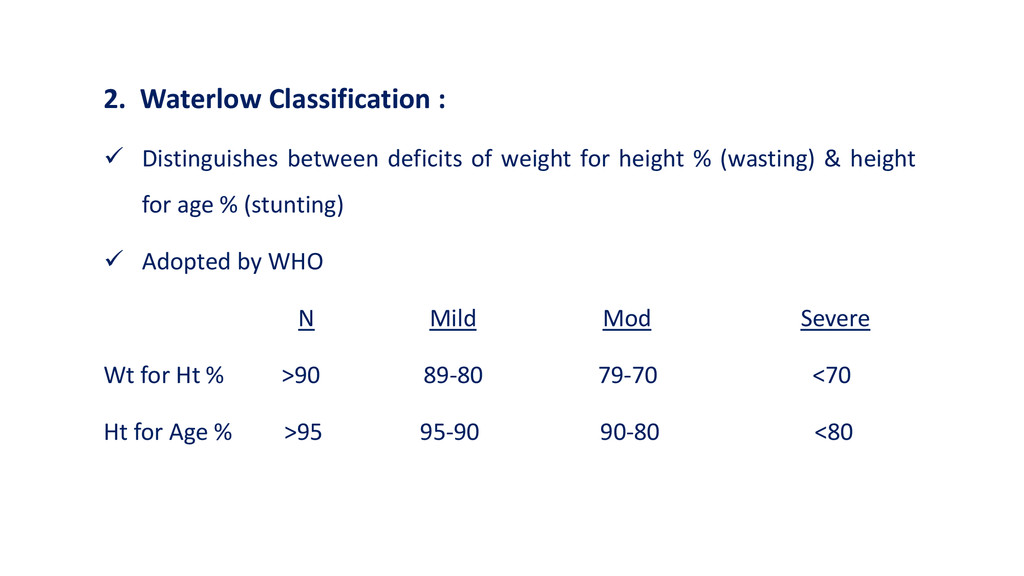
for height % (wasting) & height for age % (stunting) Adopted by WHO N Mild Mod Severe Wt for Ht % >90 89-80 79-70 <70 Ht for Age % >95 95-90 90-80 <80
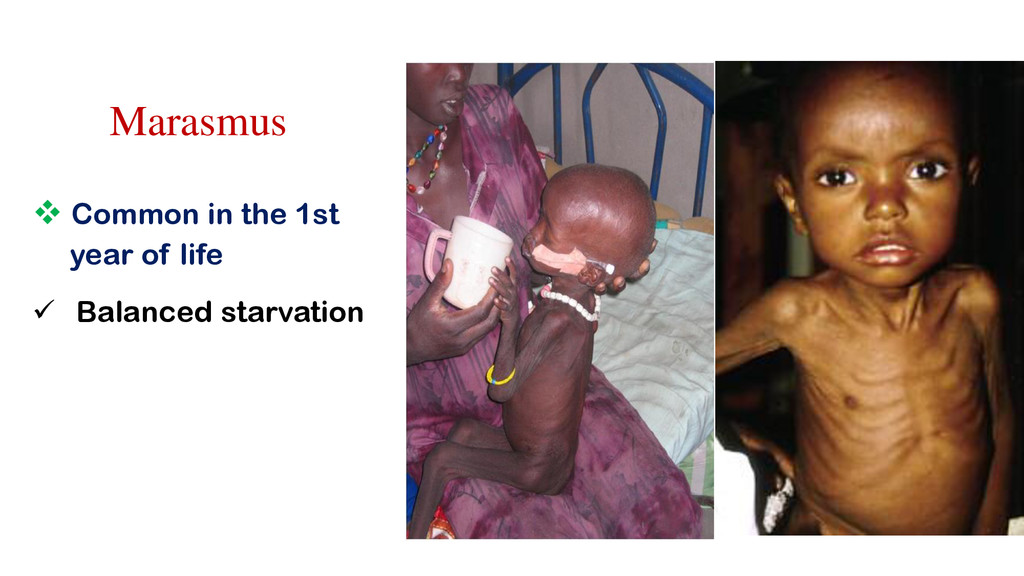
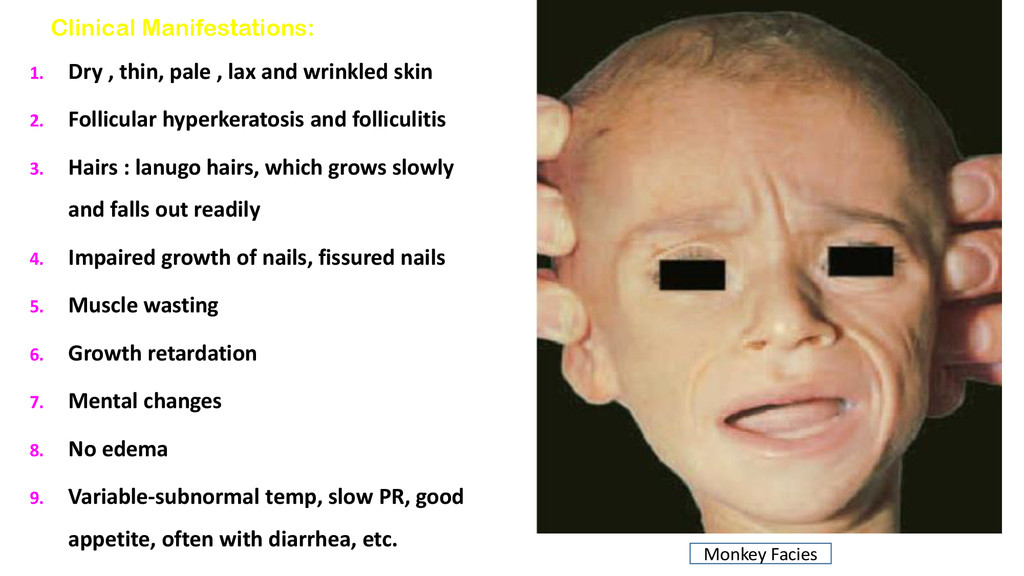
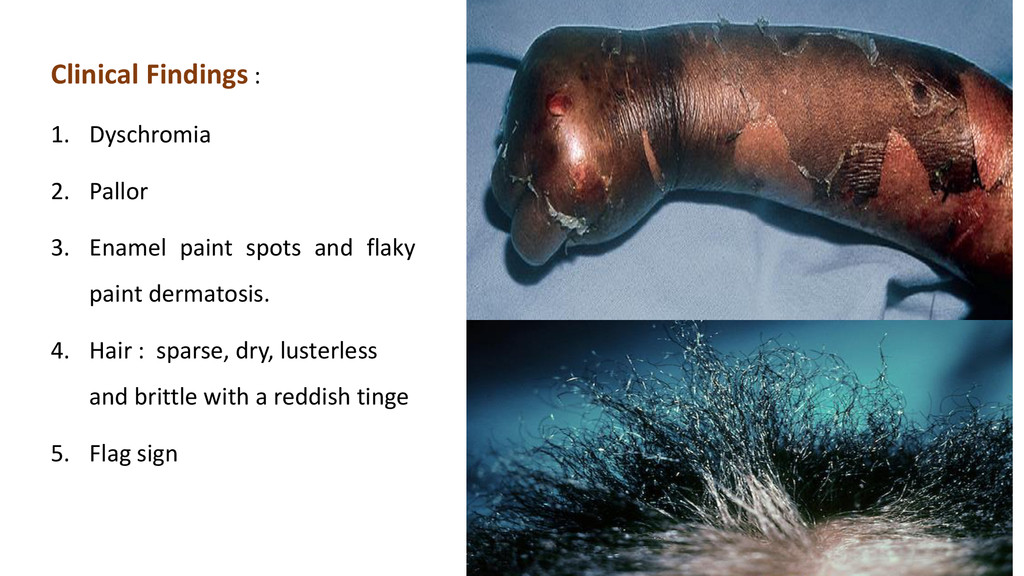
wrinkled skin 2. Follicular hyperkeratosis and folliculitis 3. Hairs : lanugo hairs, which grows slowly and falls out readily 4. Impaired growth of nails, fissured nails 5. Muscle wasting 6. Growth retardation 7. Mental changes 8. No edema 9. Variable-subnormal temp, slow PR, good appetite, often with diarrhea, etc. Monkey Facies
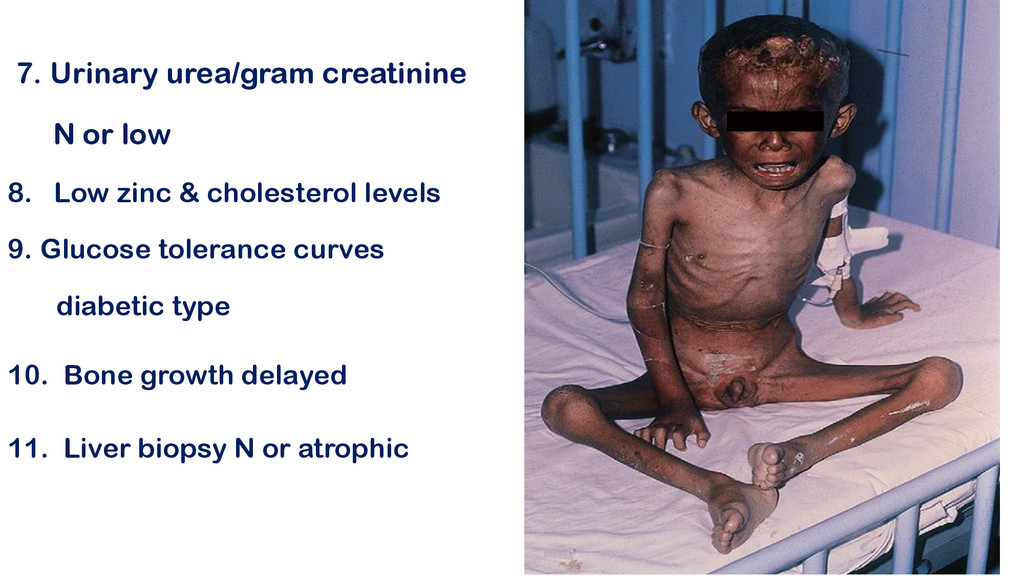
muscle circumference <15cm 3. Most hair bulbs are in the telogen phase 4. Abundant broken hairs 5. Creatinine height index <60% of standard 6. Serum albumin Normal
readaptation of metabolic and intestinal functions Supplementation with linoleic acid and zinc Monitor for hypophosphatemia and cardiorespiratory failure (associated with overly aggressive nutritional replacement)
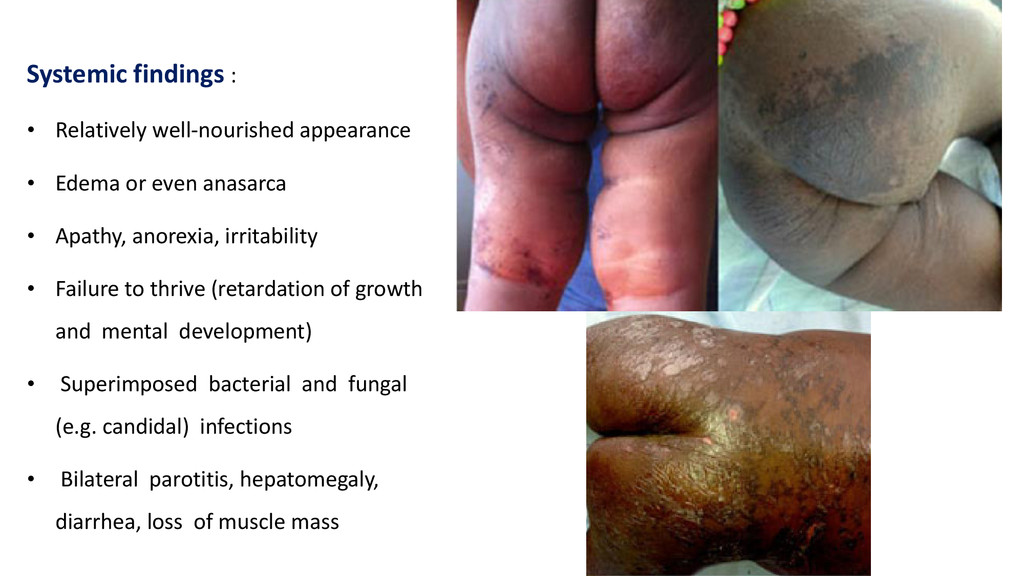
even anasarca • Apathy, anorexia, irritability • Failure to thrive (retardation of growth and mental development) • Superimposed bacterial and fungal (e.g. candidal) infections • Bilateral parotitis, hepatomegaly, diarrhea, loss of muscle mass
<200 ɱg/dl • Peripheral lymphocyte count <1500/ɱl • Decreased number of anagen hair follicles and increased number of telogen follicles • Structural abnormalities in anagen follicles – severe atrophy, shaft constriction, depletion of pigment
metabolic balance; correction of any electrolyte disturbances or hypoglycemia • Institute diet with adequate protein and caloric • Identify and attempt to treat underlying cause(s), including bacterial and parasitic disease


 sanjaysingh07
 mclloyd
 aleyda
 tapps
 codingconduct
 destraynor
 pedronauck
 axbom
 brettharned
 jonoalderson
 bethany
 garrettdimon
 kimpetersen