Share
Embed
FIT for Surgery? ERAS 2.0 - Attila Kett MD, MBA, FASA
Case Conference 8/11/2021 Chair of Anesthesiology at Saint Peter's Hospital, NB NJ 08901
us414
August 11, 2021
Transcript
58 slides
-
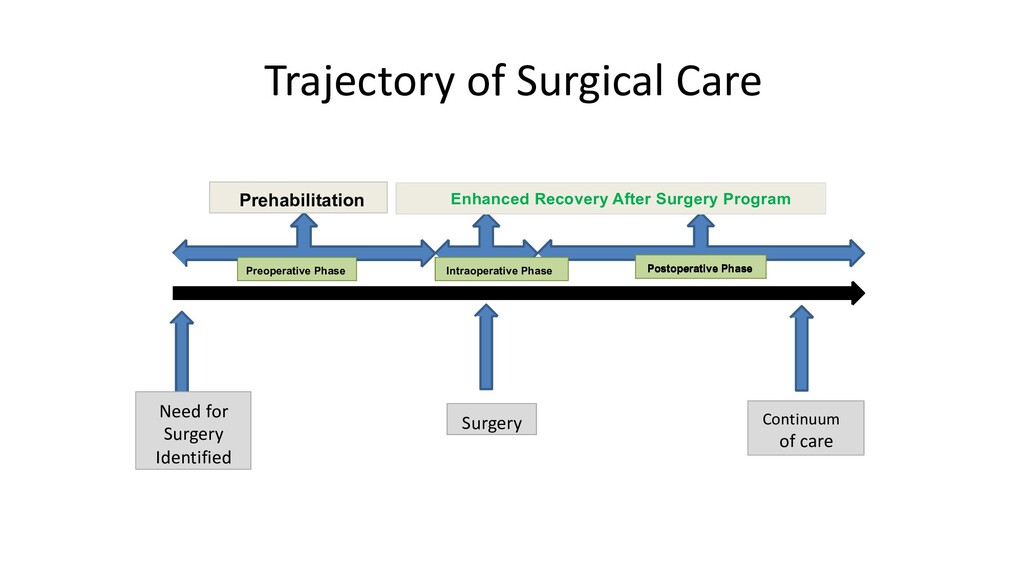
Need for Surgery Identified Surgery Preoperative Phase Prehabilitation Postoperative Phase
Enhanced Recovery After Surgery Program Intraoperative Phase Postoperative Phase Trajectory of Surgical Care Continuum of care -
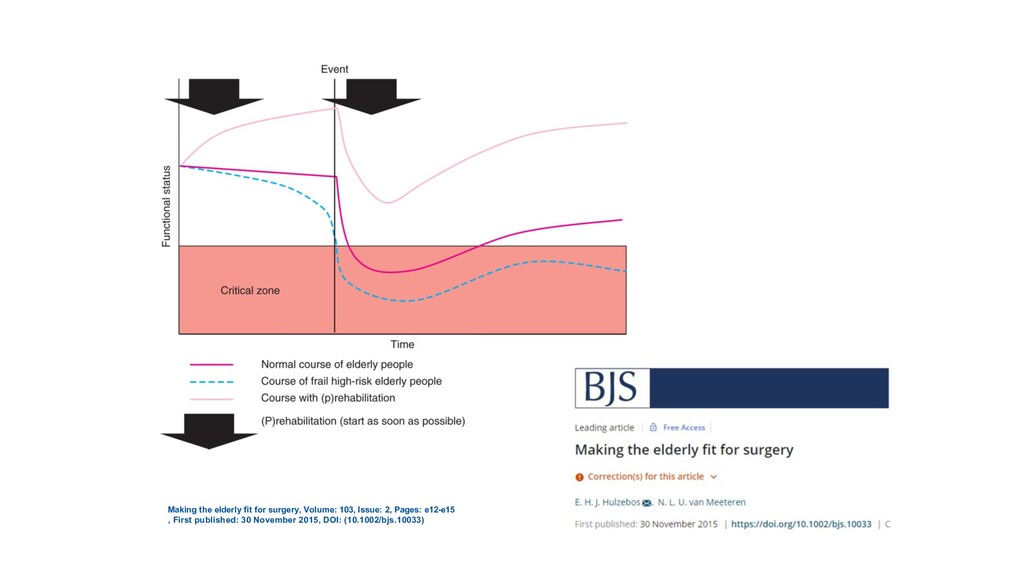
Current practice is to predict postoperative complications and to adjust
postoperative resources and wait until after surgery to intervene to help patients to recover Rehabilitation -
Making the elderly fit for surgery, Volume: 103, Issue: 2,
Pages: e12-e15 , First published: 30 November 2015, DOI: (10.1002/bjs.10033) -
Is the postoperative period the right time to intervene? Patients
are tired, depressed, weak Can we improve patient’s fitness before surgery, while waiting ? Prehabilitation -
Prehabilitation The multimodal process of improving a patient’s functional status
pre-operatively to enhance their body’s ability to cope with a stressful event and therefore improve their postoperative outcome. A group of interventions, integrated into the clinical pathway before a surgical procedure and aimed at both reducing imminent patient risk and promoting lasting beneficial effects on perioperative recovery and outcome. -
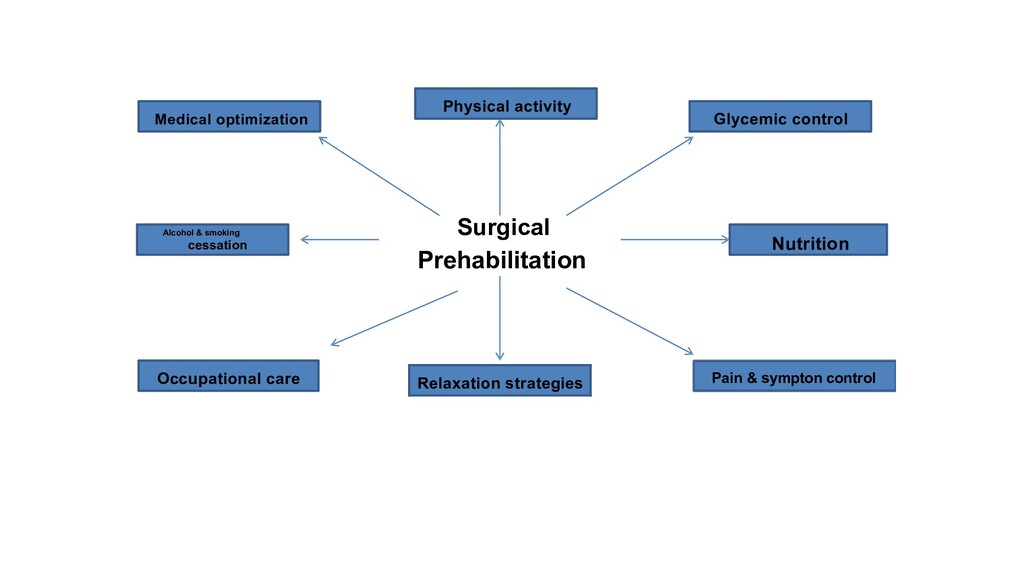
Surgical Prehabilitation Relaxation strategies Physical activity Nutrition Alcohol & smoking
cessation Glycemic control Medical optimization Pain & sympton control Occupational care -
Prevalence of Preoperative Anemia in Elective Orthopedic Surgery n In
a US national audit of patients undergoing elective orthopedic surgery, 35% of patients were found to have Hb levels <13 g/dL at preadmission testing 1 n In a large single-institution study in Spain, preoperative Hb was <13 g/dL in 19.4% of patients, and the prevalence of hematinic deficiencies was 33% for iron, 12.3% for vitamin B12 , and 3% for folate 2 n These results were also corroborated by a large series from Egypt and Scotland 3 1. Bierbaum BE et al. J Bone Joint Surg Am. 1999 2. Bisbe E et al. TATM. 2008 3. Saleh E et al. Br J Anaesth. 2007 -
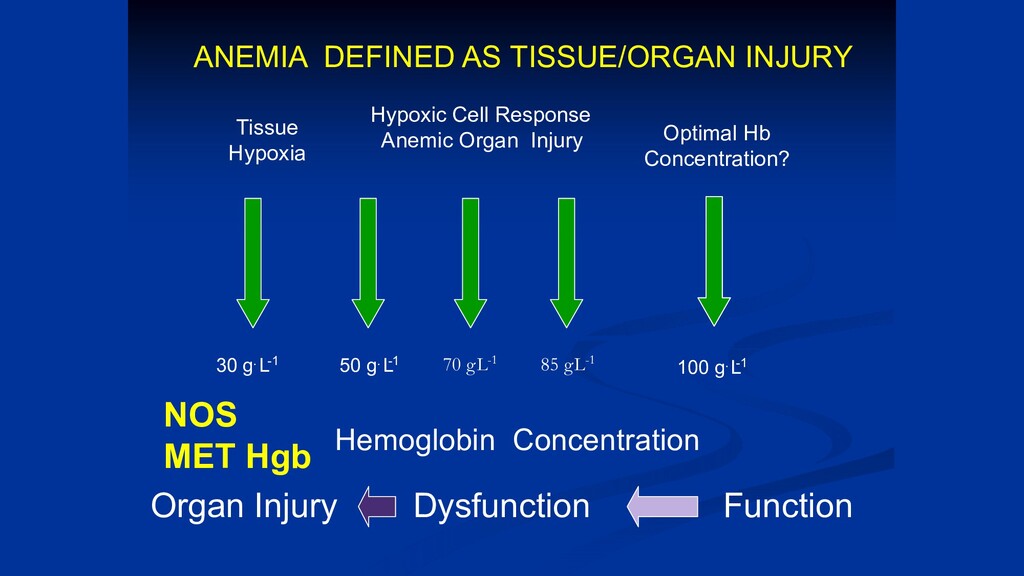
50 g L . -1 100 g L . -1
Hemoglobin Concentration 30 g L . -1 70 g.L-1 85 g.L-1 Tissue Hypoxia Hypoxic Cell Response Anemic Organ Injury Optimal Hb Concentration? Organ Injury Dysfunction Function ANEMIA DEFINED AS TISSUE/ORGAN INJURY NOS MET Hgb -
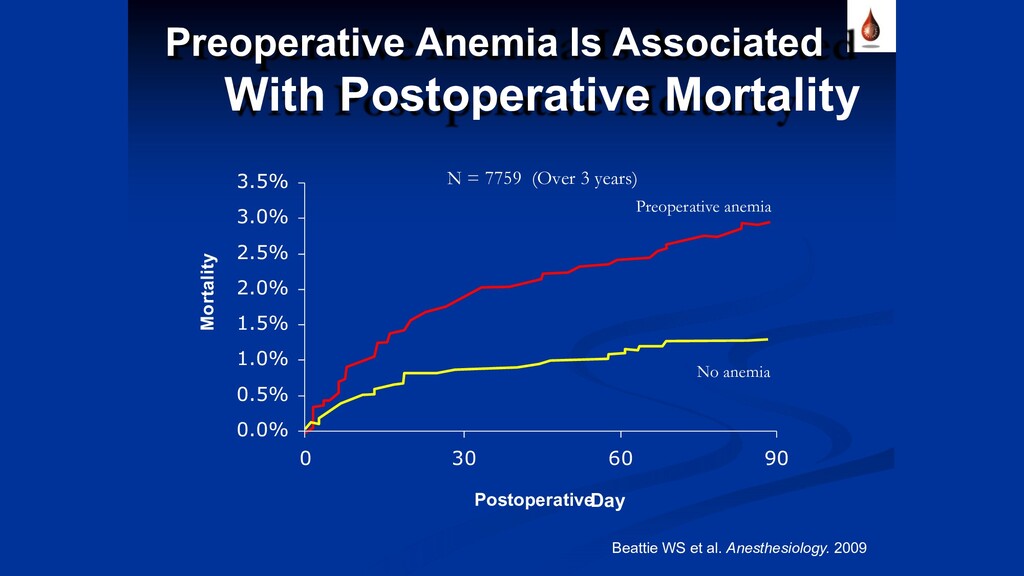
Preoperative Anemia Is Associated With Postoperative Mortality Beattie WS et
al. Anesthesiology. 2009 Preoperative anemia No anemia 0.0% 0.5% 1.0% 1.5% 2.0% 2.5% 3.0% 3.5% 0 30 60 90 Postoperative Day Mortality N = 7759 (Over 3 years) -
Clinical Strategies Treating Anemia n Early identification & treatment of
anemia before reaching a “Transfusion Threshold (TRIGGER)” n Use of other treatments before allogeneic blood n Avoid daily blood draws unless absolutely needed n Nutritional supplements • Iron • Folic Acid • B 12 -
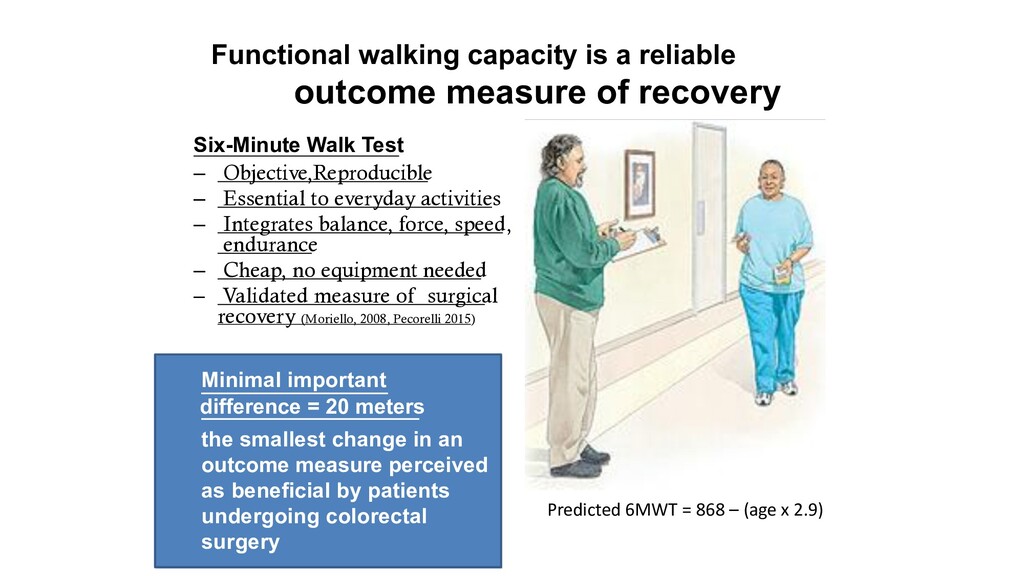
Functional walking capacity is a reliable outcome measure of recovery
Six-Minute Walk Test – Objective,Reproducible – Essential to everyday activities – Integrates balance, force, speed, endurance – Cheap, no equipment needed – Validated measure of surgical recovery (Moriello, 2008, Pecorelli 2015) . Predicted 6MWT = 868 – (age x 2.9) Minimal important difference = 20 meters the smallest change in an outcome measure perceived as beneficial by patients undergoing colorectal surgery -
Treatment • Physical activity with protein supplementation has demonstrated to
be effective in improving muscle mass and function and in preventing disability and frailty in older persons. • Aerobic training • Resistance training -
Take Home Message • • Prehabilitation: is feasible It is
part of the ERAS program • • Requires a multidisciplinary approach Customize the program to each patient/surgery • • Proof of concept: increases functional capacity Can improve postoperative outcome -
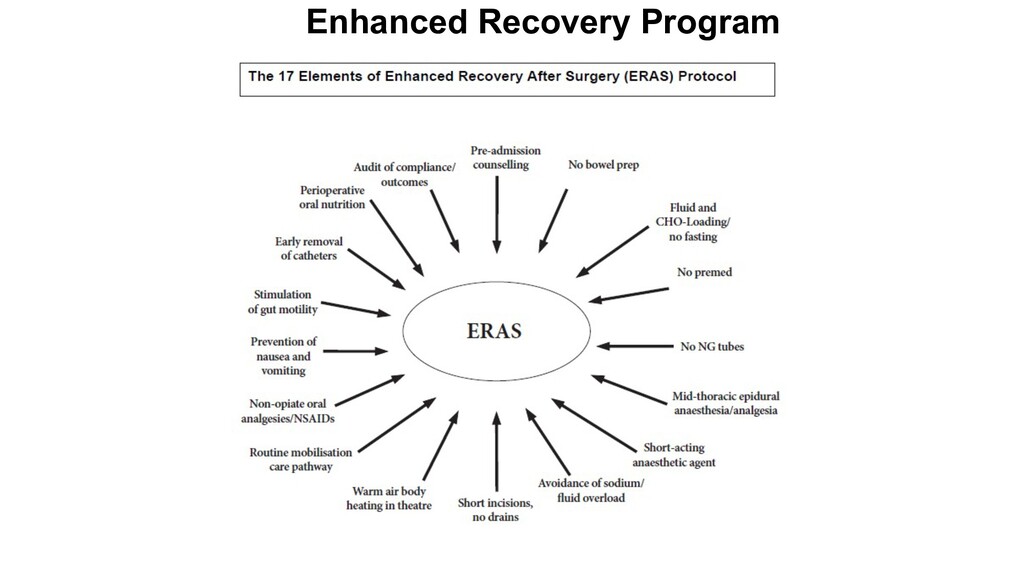
Evolution of surgical principles brought about the concept of E
R A S This concept was first described in 1990s by Henrik Kehlet, MD, PhD, Surgical Gastroenterologist. -
Mission statement Develop procedure specific- patient centered perioperative care pathways
to minimize symptom burden, enhance functional recovery, improve outcomes and enable delivery of safe, effective, and value-based care to an increasing number of patients. -
Dogma: Back to the Past…. Senior surgeons had strong principles

and they were assumed as a dogma. Preoperative prolonged fasting, Mechanical bowel preparation and nasogastric tubes were thought to be necessary to empty the bowel to prevent intraoperative contamination and to prevent early passage of bowel content through an anastomotic suture line while it is healing. Drain tube was believed essential in any GIT surgery. Prolonged bed rest were recommended to facilitate abdominal wall healing. -
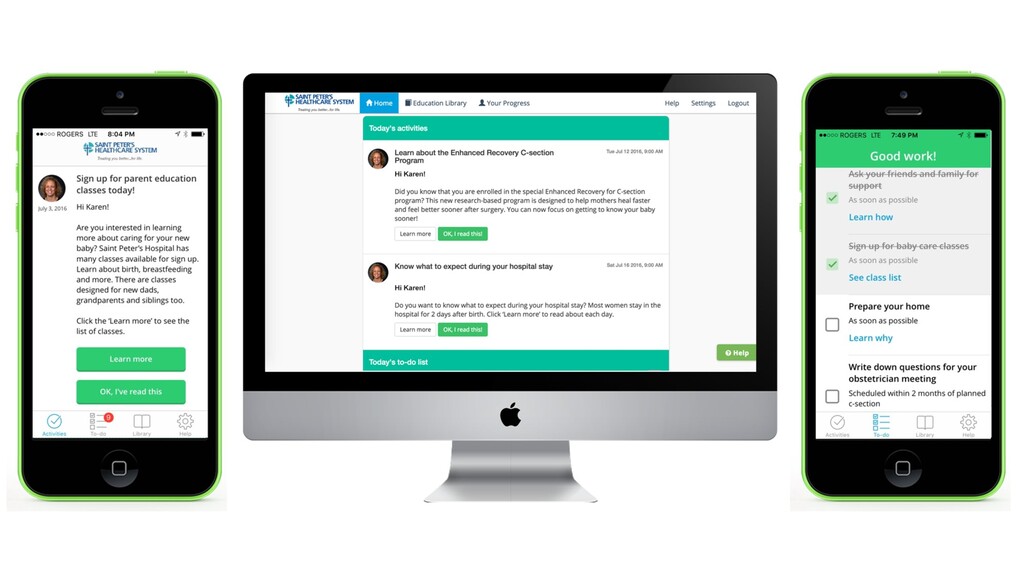
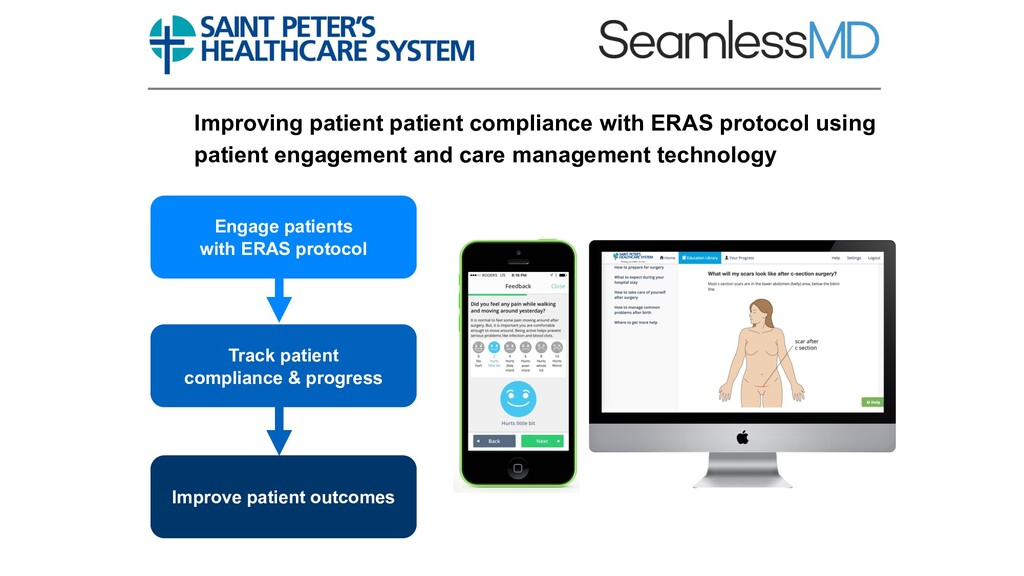
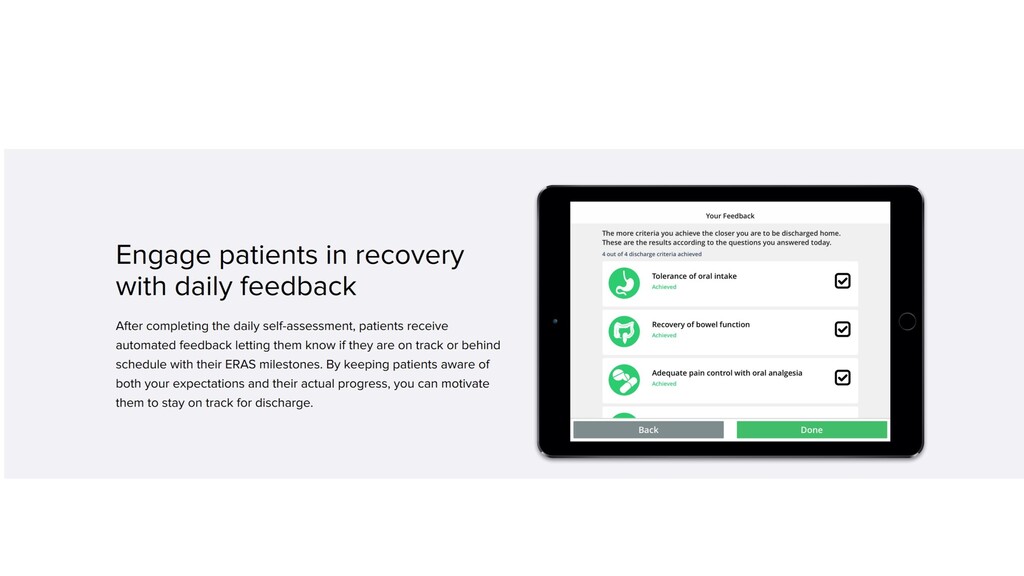
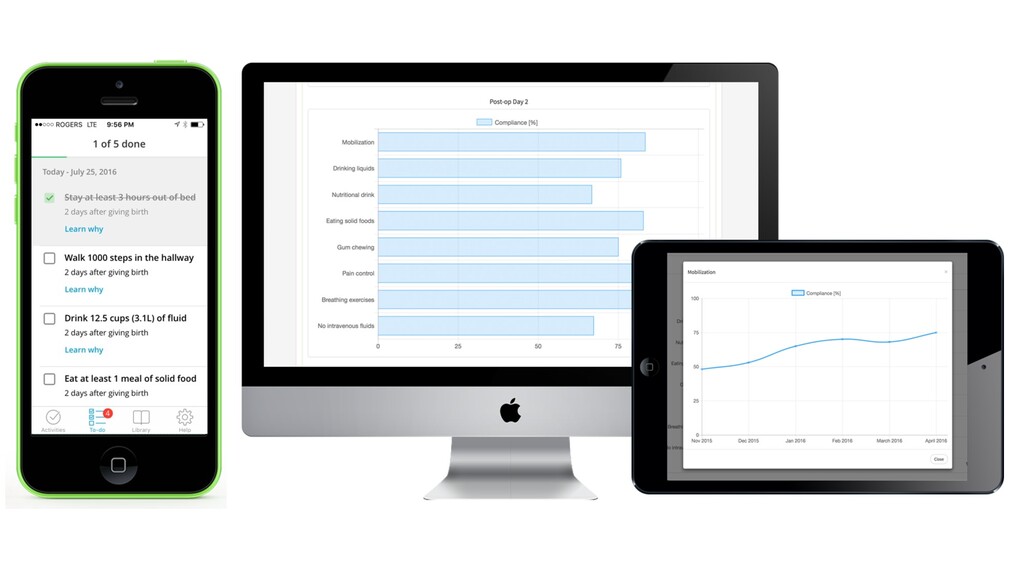
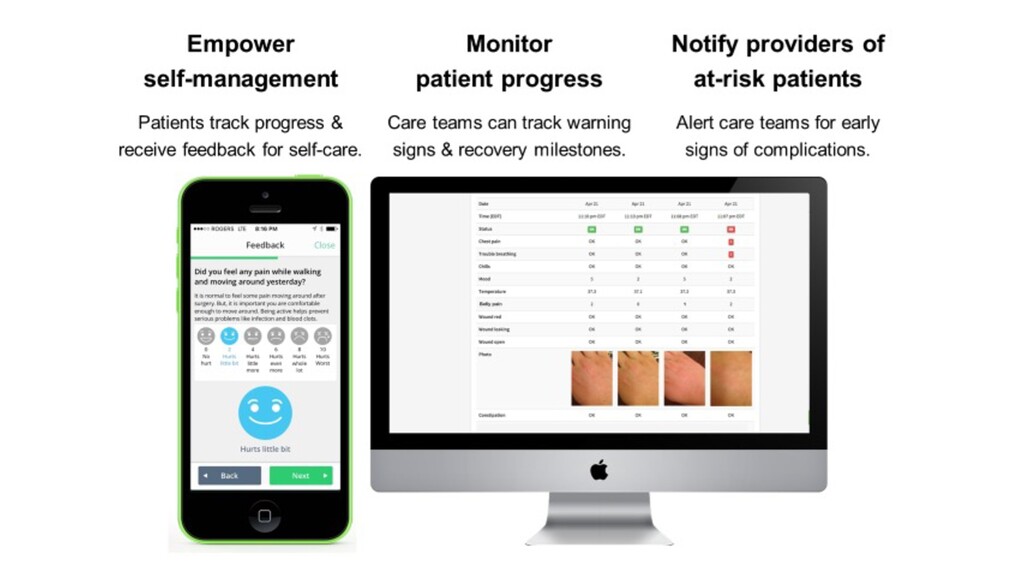
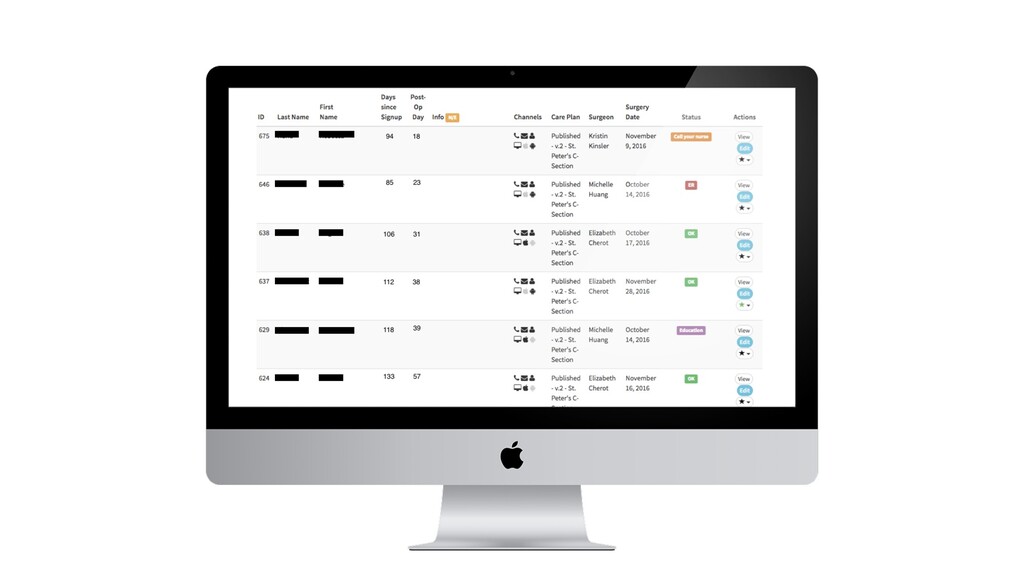
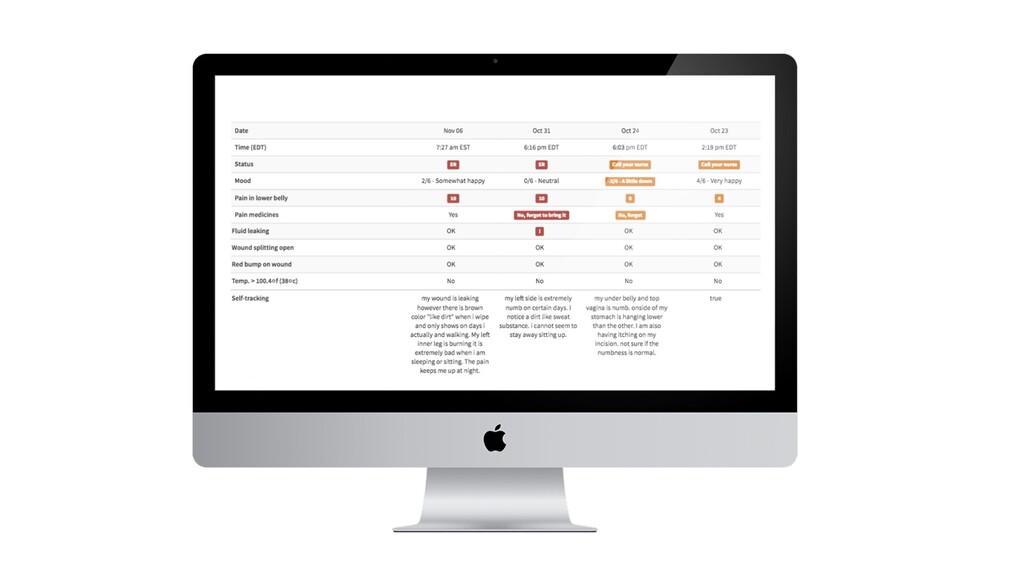
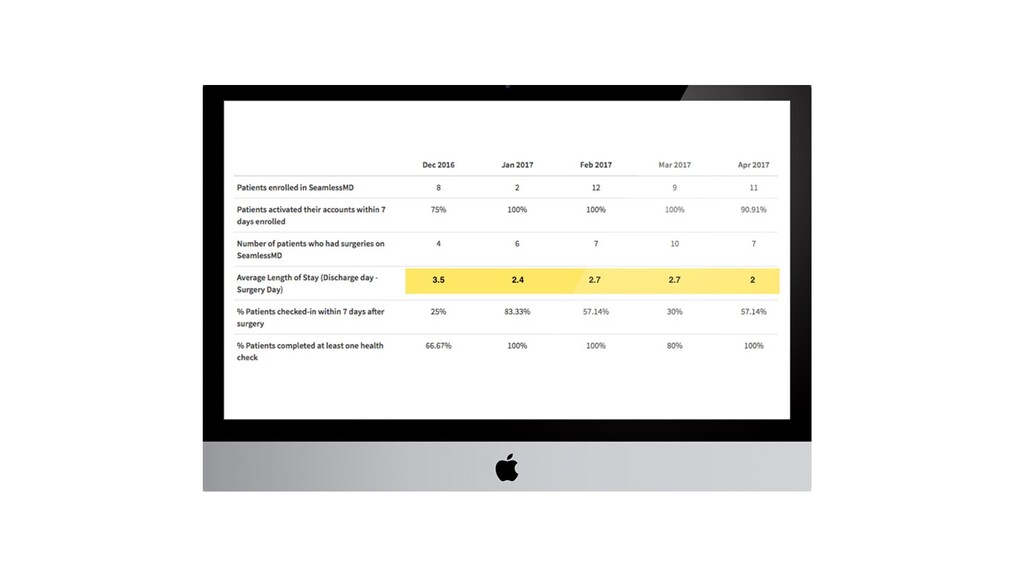
Engage patients with ERAS protocol Track patient compliance & progress
Improve patient outcomes Improving patient patient compliance with ERAS protocol using patient engagement and care management technology -
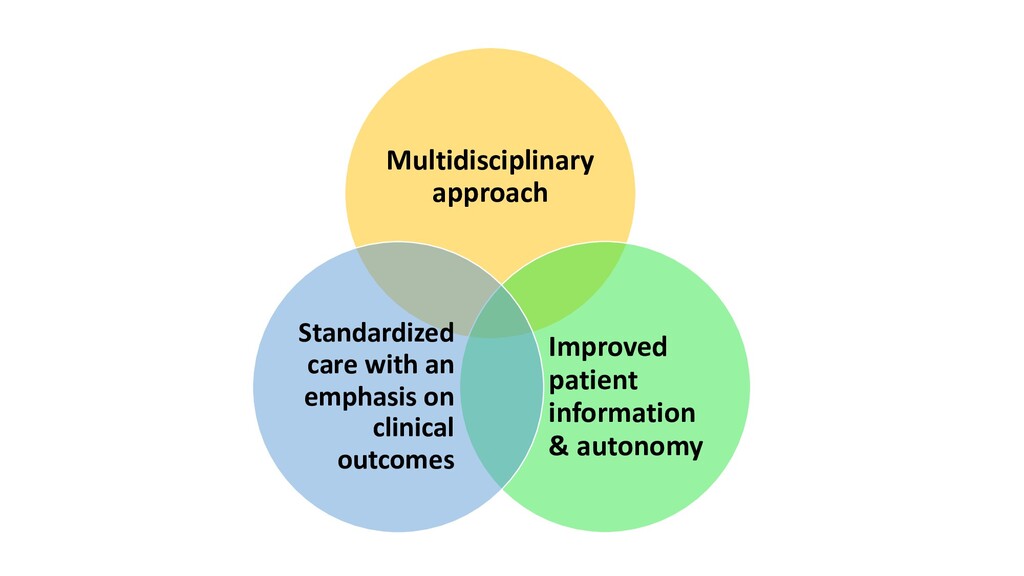
Multidisciplinary approach Improved patient information & autonomy Standardized care with
an emphasis on clinical outcomes -
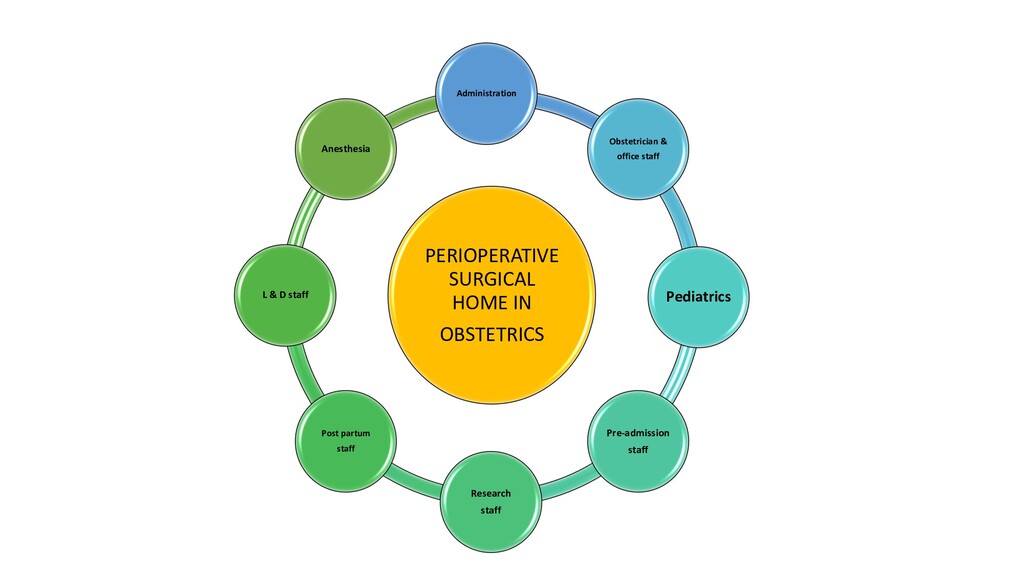
PERIOPERATIVE SURGICAL HOME IN OBSTETRICS Administration Obstetrician & office staff
Pediatrics Pre-admission staff Research staff Post partum staff L & D staff Anesthesia -
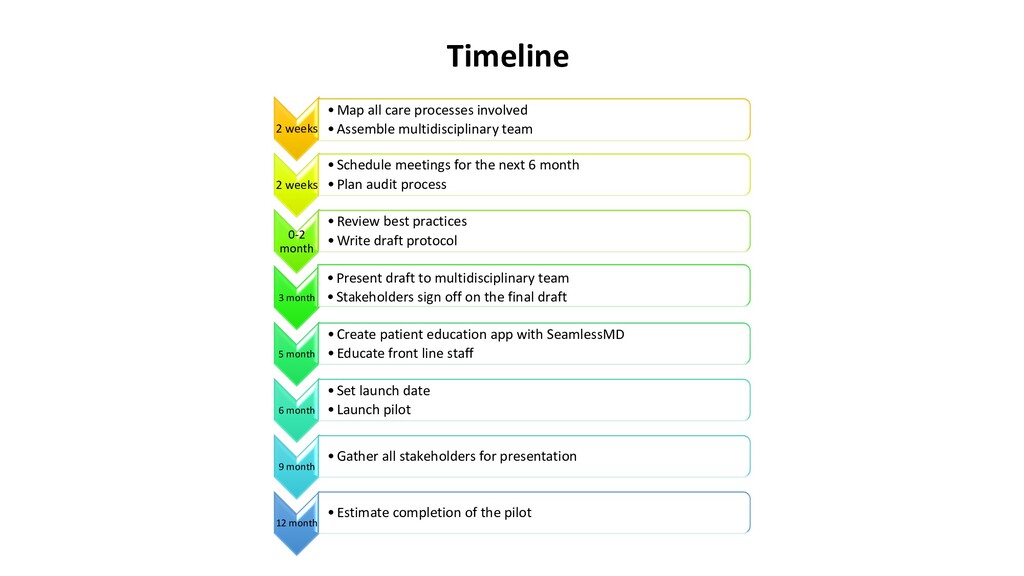
2 weeks •Map all care processes involved •Assemble multidisciplinary team
2 weeks •Schedule meetings for the next 6 month •Plan audit process 0-2 month •Review best practices •Write draft protocol 3 month •Present draft to multidisciplinary team •Stakeholders sign off on the final draft 5 month •Create patient education app with SeamlessMD •Educate front line staff 6 month •Set launch date •Launch pilot 9 month •Gather all stakeholders for presentation 12 month •Estimate completion of the pilot Timeline -
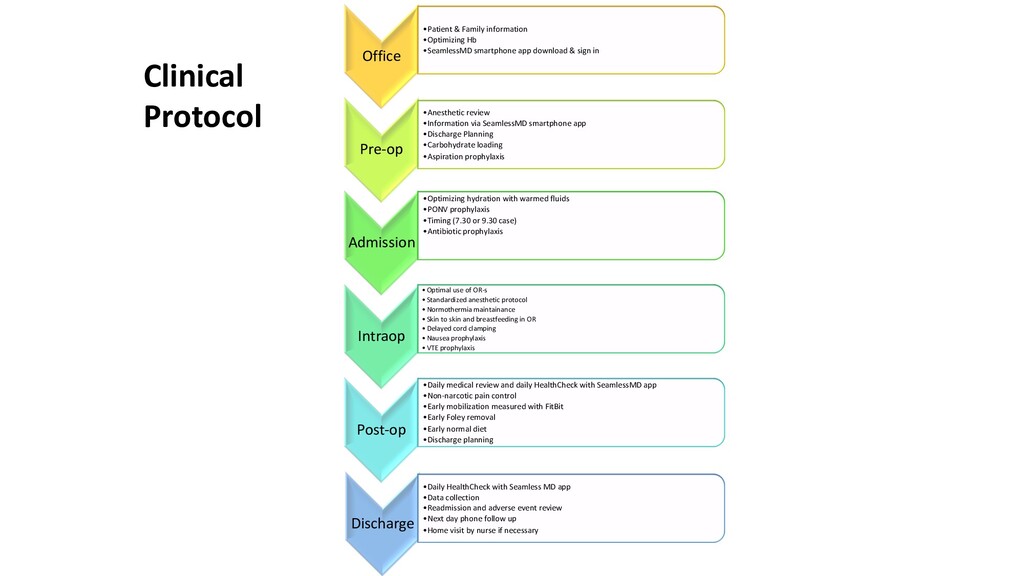
Office •Patient & Family information •Optimizing Hb •SeamlessMD smartphone app
download & sign in Pre-op •Anesthetic review •Information via SeamlessMD smartphone app •Discharge Planning •Carbohydrate loading •Aspiration prophylaxis Admission •Optimizing hydration with warmed fluids •PONV prophylaxis •Timing (7.30 or 9.30 case) •Antibiotic prophylaxis Intraop •Optimal use of OR-s •Standardized anesthetic protocol •Normothermia maintainance •Skin to skin and breastfeeding in OR •Delayed cord clamping •Nausea prophylaxis •VTE prophylaxis Post-op •Daily medical review and daily HealthCheck with SeamlessMD app •Non-narcotic pain control •Early mobilization measured with FitBit •Early Foley removal •Early normal diet •Discharge planning Discharge •Daily HealthCheck with Seamless MD app •Data collection •Readmission and adverse event review •Next day phone follow up •Home visit by nurse if necessary Clinical Protocol -
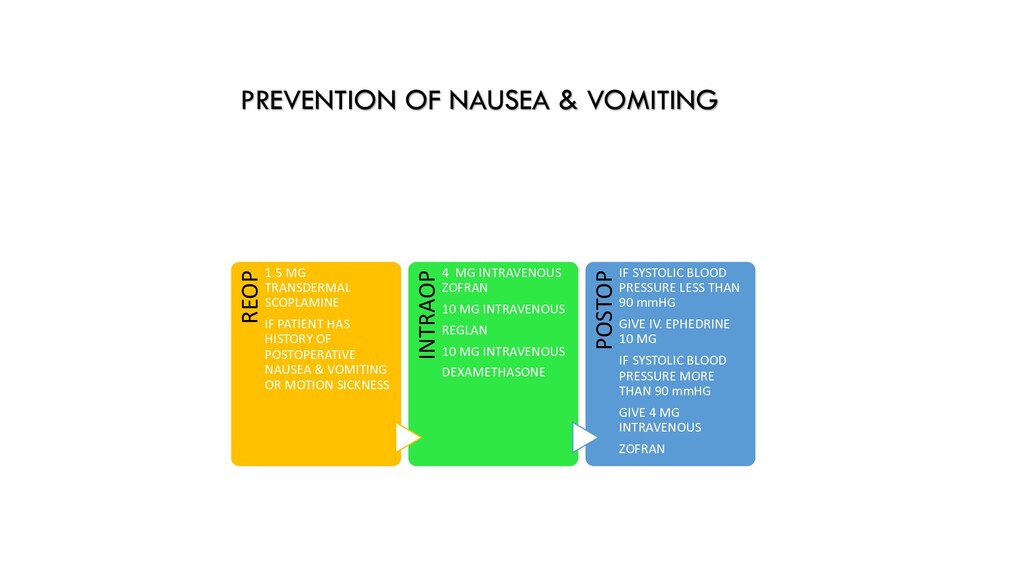
PREVENTION OF NAUSEA & VOMITING REOP 1.5 MG TRANSDERMAL SCOPLAMINE
IF PATIENT HAS HISTORY OF POSTOPERATIVE NAUSEA & VOMITING OR MOTION SICKNESS INTRAOP 4 MG INTRAVENOUS ZOFRAN 10 MG INTRAVENOUS REGLAN 10 MG INTRAVENOUS DEXAMETHASONE POSTOP IF SYSTOLIC BLOOD PRESSURE LESS THAN 90 mmHG GIVE IV. EPHEDRINE 10 MG IF SYSTOLIC BLOOD PRESSURE MORE THAN 90 mmHG GIVE 4 MG INTRAVENOUS ZOFRAN -
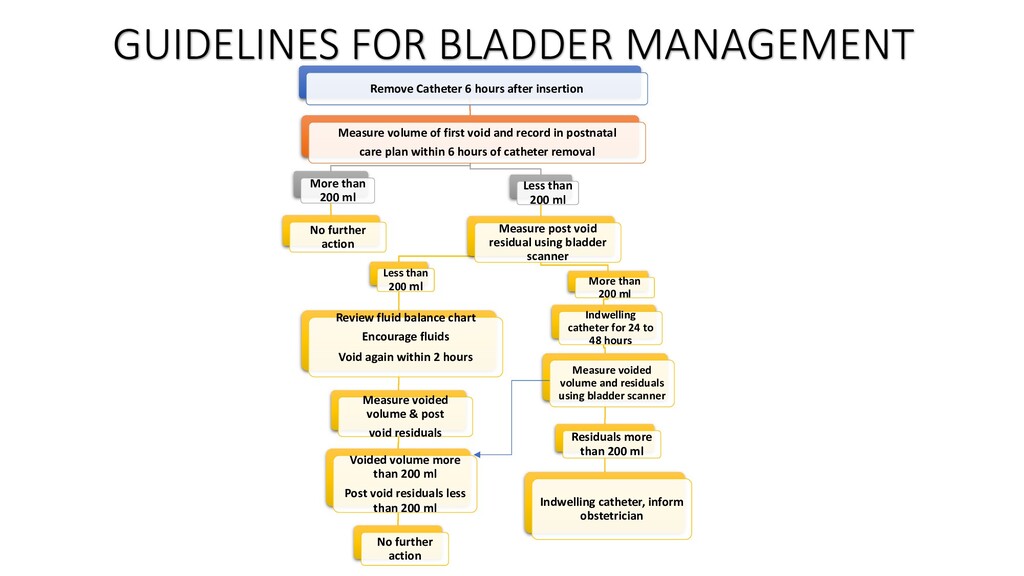
Remove Catheter 6 hours after insertion Measure volume of first
void and record in postnatal care plan within 6 hours of catheter removal More than 200 ml No further action Less than 200 ml Measure post void residual using bladder scanner Less than 200 ml Review fluid balance chart Encourage fluids Void again within 2 hours Measure voided volume & post void residuals Voided volume more than 200 ml Post void residuals less than 200 ml No further action More than 200 ml Indwelling catheter for 24 to 48 hours Measure voided volume and residuals using bladder scanner Residuals more than 200 ml Indwelling catheter, inform obstetrician GUIDELINES FOR BLADDER MANAGEMENT -
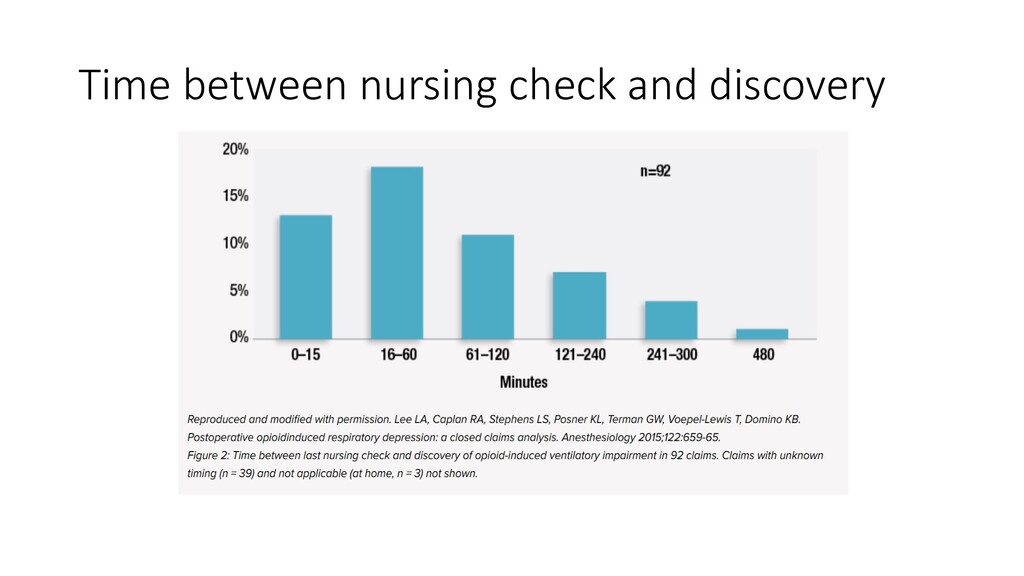
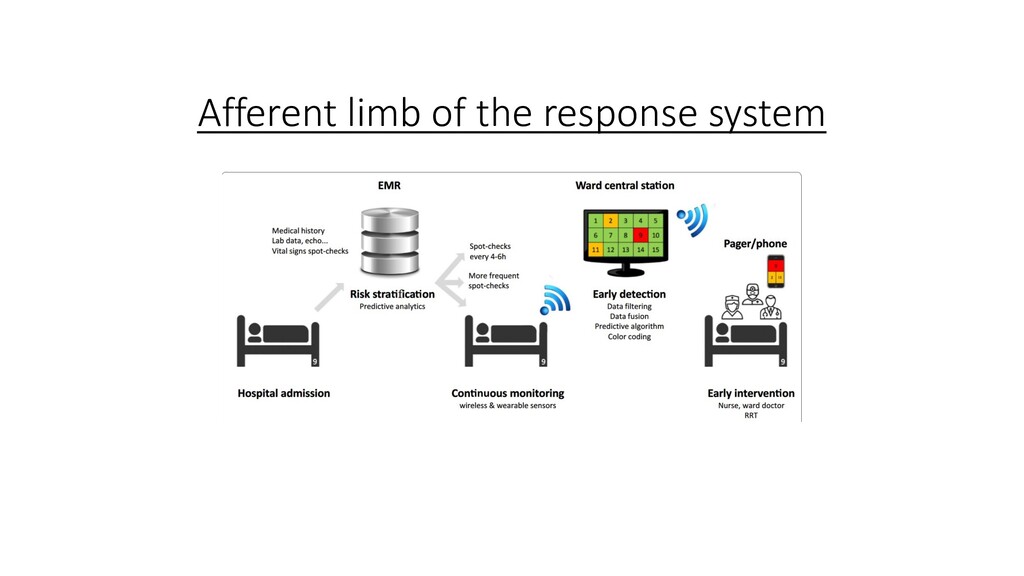
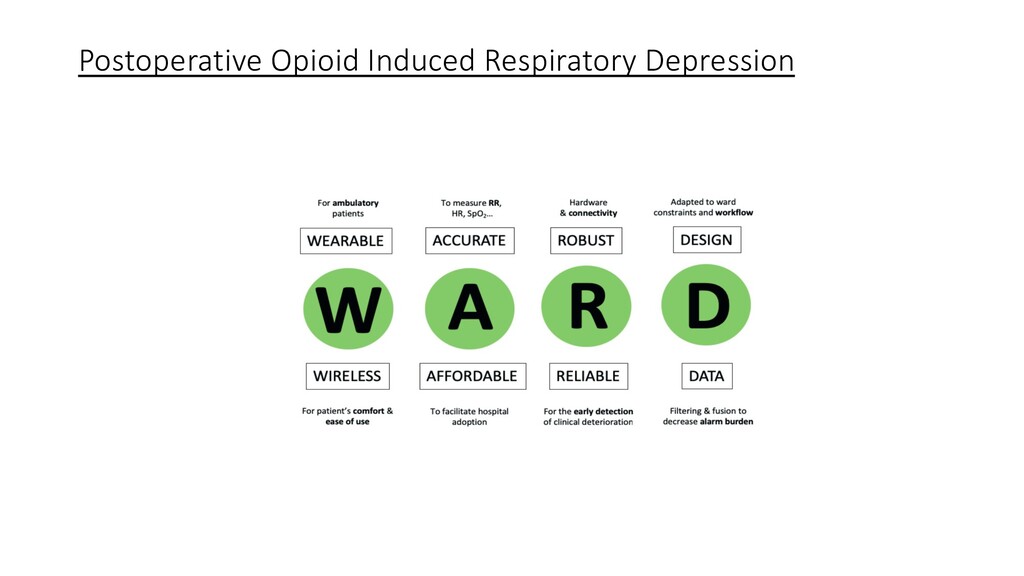
Postoperative Opioid Induced Respiratory Depression Finding patients before they rapidly
deteriorate and suffer a major adverse event might be the next major opportunity to improve patient safety. -
Postoperative Opioid Induced Respiratory Depression Solution It seems likely that
continuous ward monitoring should be the standard-of-care for high risk patients since vital signs at 4- to 6-h intervals clearly miss many (and probably most) rescue opportunities and 90% of the adverse events are happening on POD 1. -
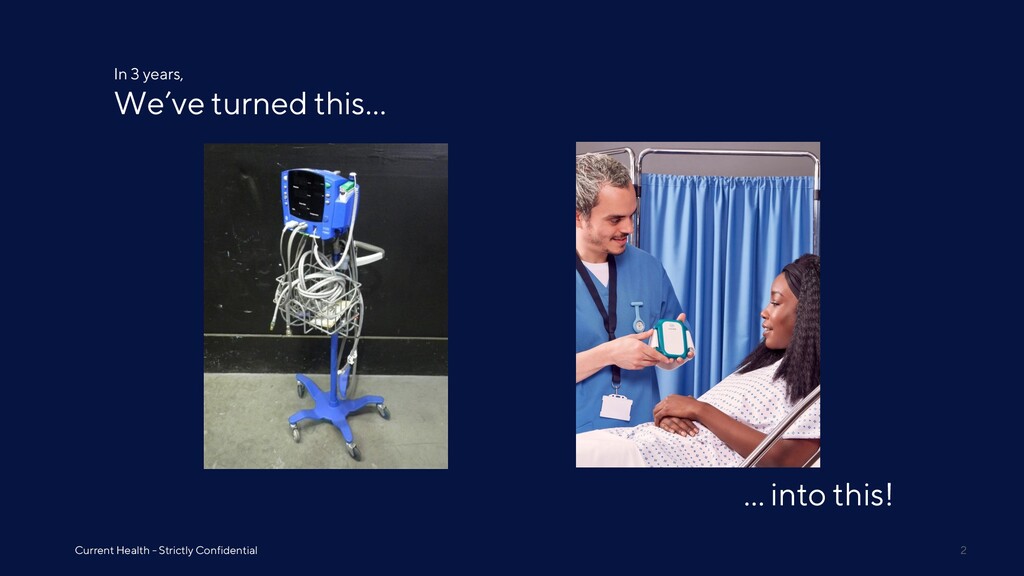
Current Health - Strictly Confidential 2 We’ve turned this… …
into this! In 3 years, Current Health - Strictly Confidential 2 We’ve turned this… … into this! In 3 years, -
A mechanism to acquire real-time data. Current Health - Strictly
Confidential 10 The most accurate FDA-cleared all-in- one device on the market. Respiration Rate Pulse Rate Oxygen Saturation Skin Temperature Mobility A ubiquitous hub for increasing data capture. Integrated devices include BP, weight and spirometry. Glucose and INR coming soon. -
Postoperative Opioid Induced Respiratory Depression Solution Finding patients before they
rapidly deteriorate and suffer a major adverse event might be the next major opportunity to improve patient safety.