Share
Embed

Transcript
58 slides
-
PAIN MANAGEMENT IN CANCER PATIENTS RUTGERS RWJUH DEPARTMENT OF ANESTHESIOLOGY
AND PAIN MEDICINE MAY 11, 2022 -
OBJECTIVES Discuss epidemiology of cancer pain Review pathophysiology
of cancer pain Discuss pharmacologic treatment options, including anti-inflammatories, anticonvulsants, antidepressants Discuss intrathecal delivery system Discuss neurolysis for cancer pain, including alcohol and phenol Discuss neurosurgical options for cancer pain -
Epidemiology of Cancer Pain Average age at cancer diagnosis
is 65 60-90% of pts will have pain Pain from disease or treatment? In pediatrics, it is more commonly from treatment Pain as first sx of cancer tends to indicate advanced disease and is an independent predictor of poor prognosis -
Special Populations In pediatrics, pain is more commonly from
treatment In geriatric population, comorbidities and drug-drug interactions need to be taken into effect In patients with substance abuse history, there is greater reliance on diagnostic imaging Inmates have higher rates of cancer, increased mortality, and undertreated symptoms -
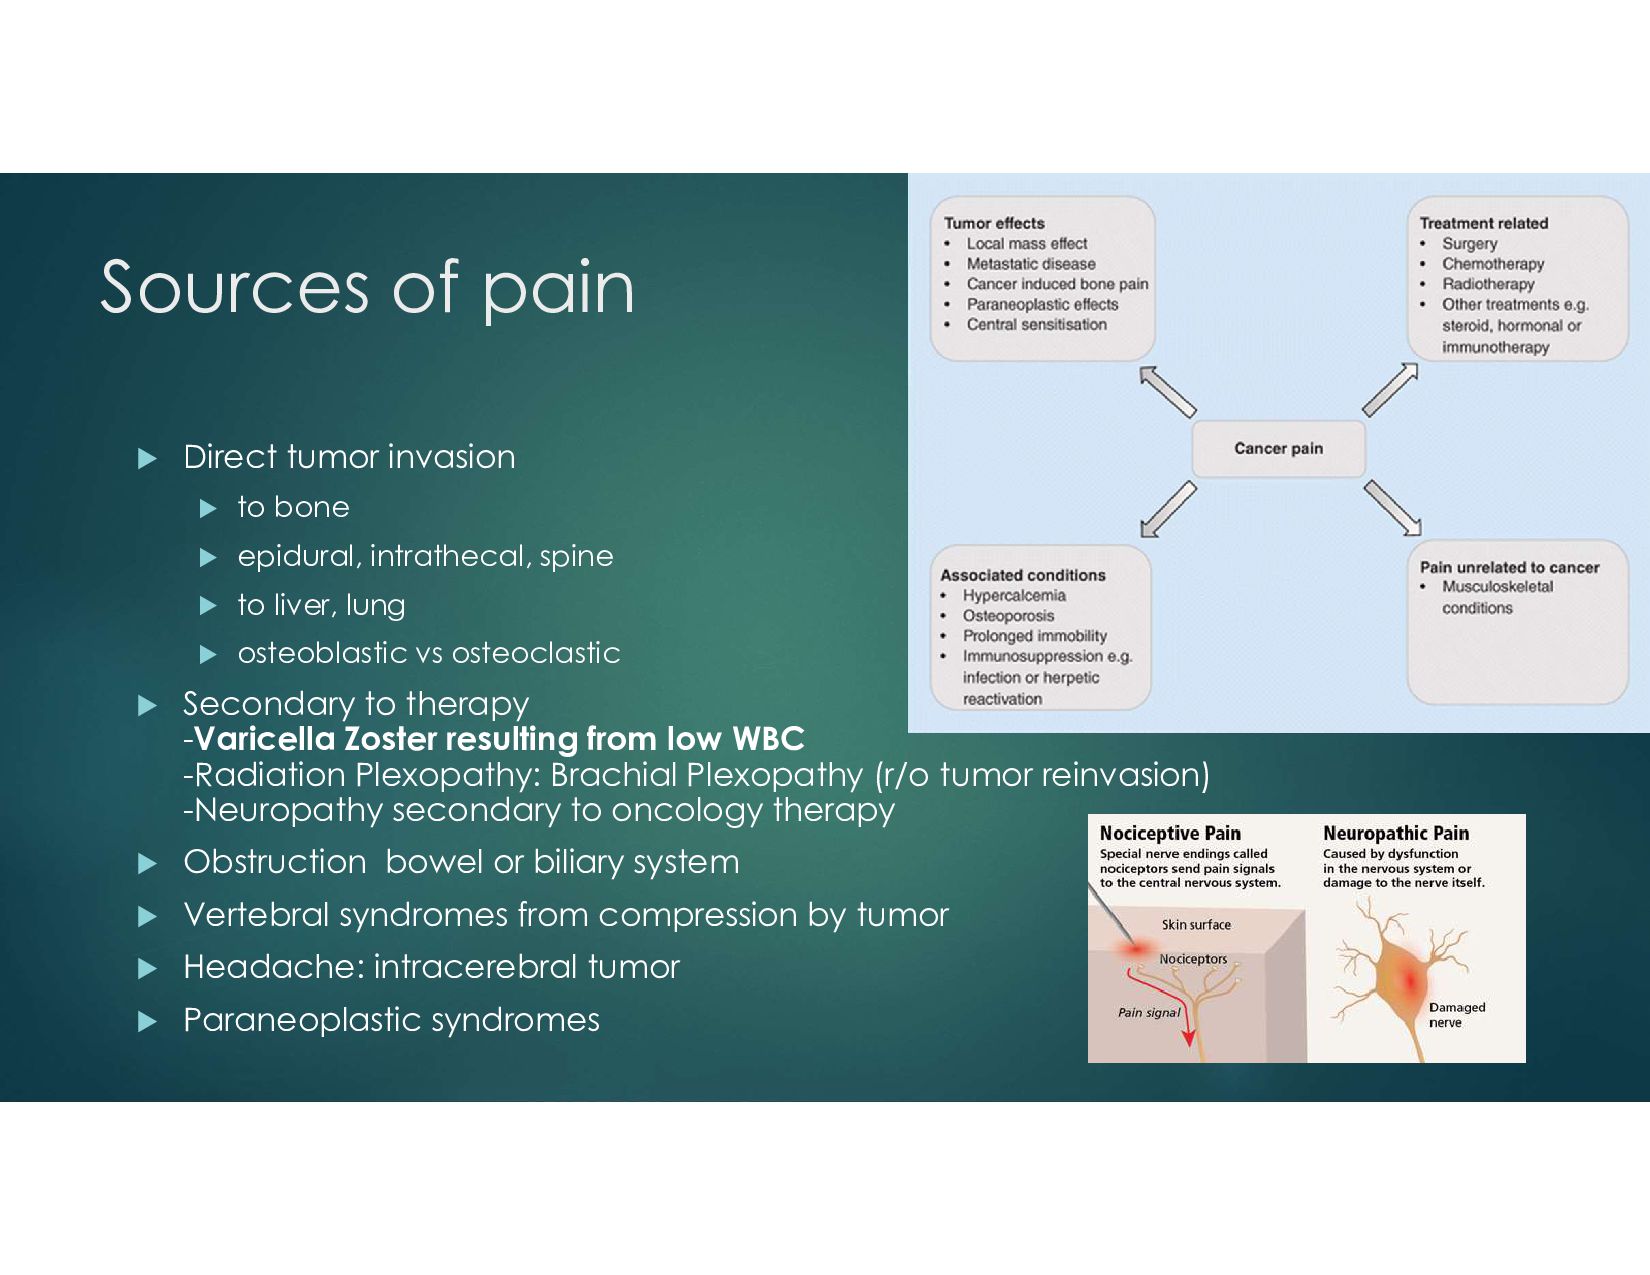
Sources of pain Direct tumor invasion to bone
epidural, intrathecal, spine to liver, lung osteoblastic vs osteoclastic Secondary to therapy -Varicella Zoster resulting from low WBC -Radiation Plexopathy: Brachial Plexopathy (r/o tumor reinvasion) -Neuropathy secondary to oncology therapy Obstruction bowel or biliary system Vertebral syndromes from compression by tumor Headache: intracerebral tumor Paraneoplastic syndromes -
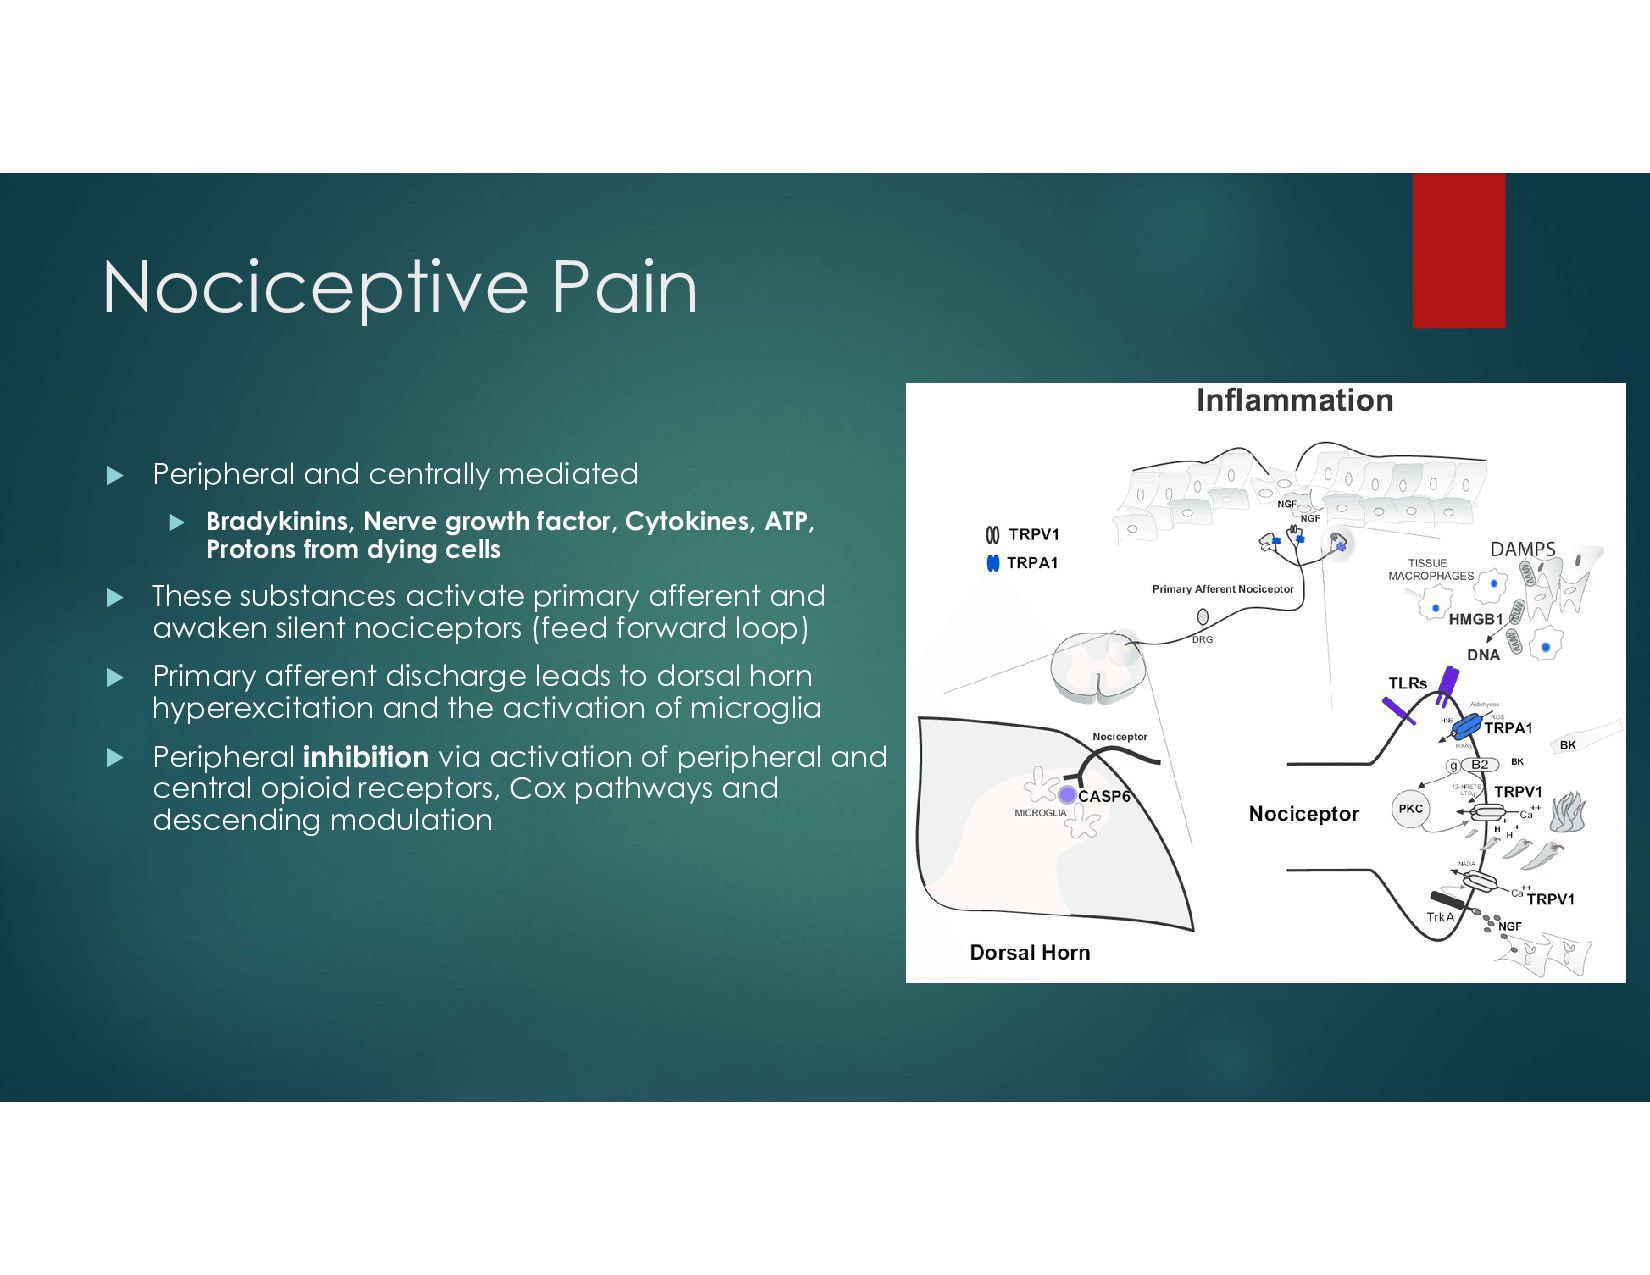
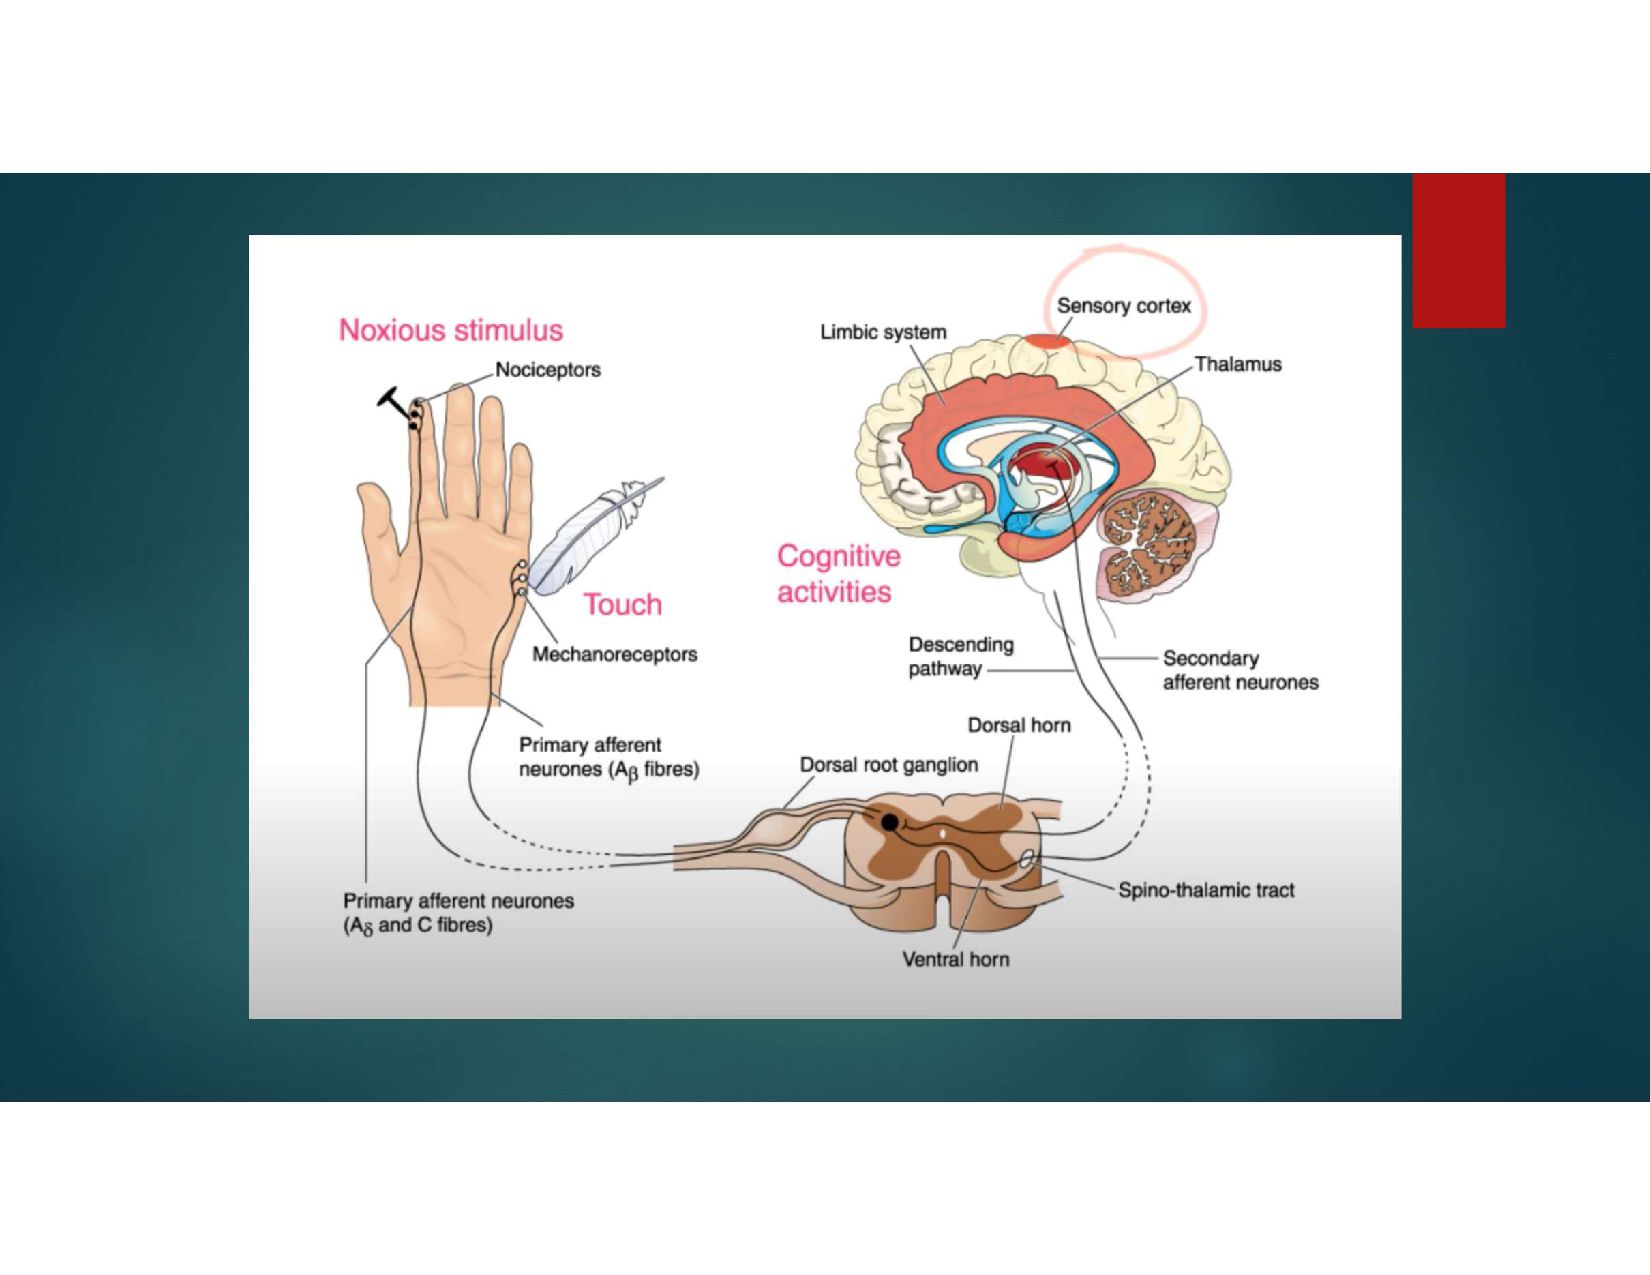
Nociceptive Pain Peripheral and centrally mediated Bradykinins, Nerve
growth factor, Cytokines, ATP, Protons from dying cells These substances activate primary afferent and awaken silent nociceptors (feed forward loop) Primary afferent discharge leads to dorsal horn hyperexcitation and the activation of microglia Peripheral inhibition via activation of peripheral and central opioid receptors, Cox pathways and descending modulation -
Neuropathic pain Damage to neurons either peripheral or central
(via compression or ischemia/ hemorrhage, chemical or transection). Peripheral damage accumulation of abnormal sodium and calcium channels at the site of injury Alterations to gene expression of receptors Damaged neurons discharge spontaneously and there is cross-talk to normal fibers and recruitment of silent nociceptors Excessive or absent discharge from primary afferents within the dorsal horn results in overall excitation an alteration in expression of NMDA receptors and functional loss of opioid and gabaminergic systems There is resultant hyperexcitation with increased receptive fields primary and secondary hyperalgesia, and allodynia Dorsal columns relay predominately to thalamus, giving rise to strong autonomic responses and efferent responses -
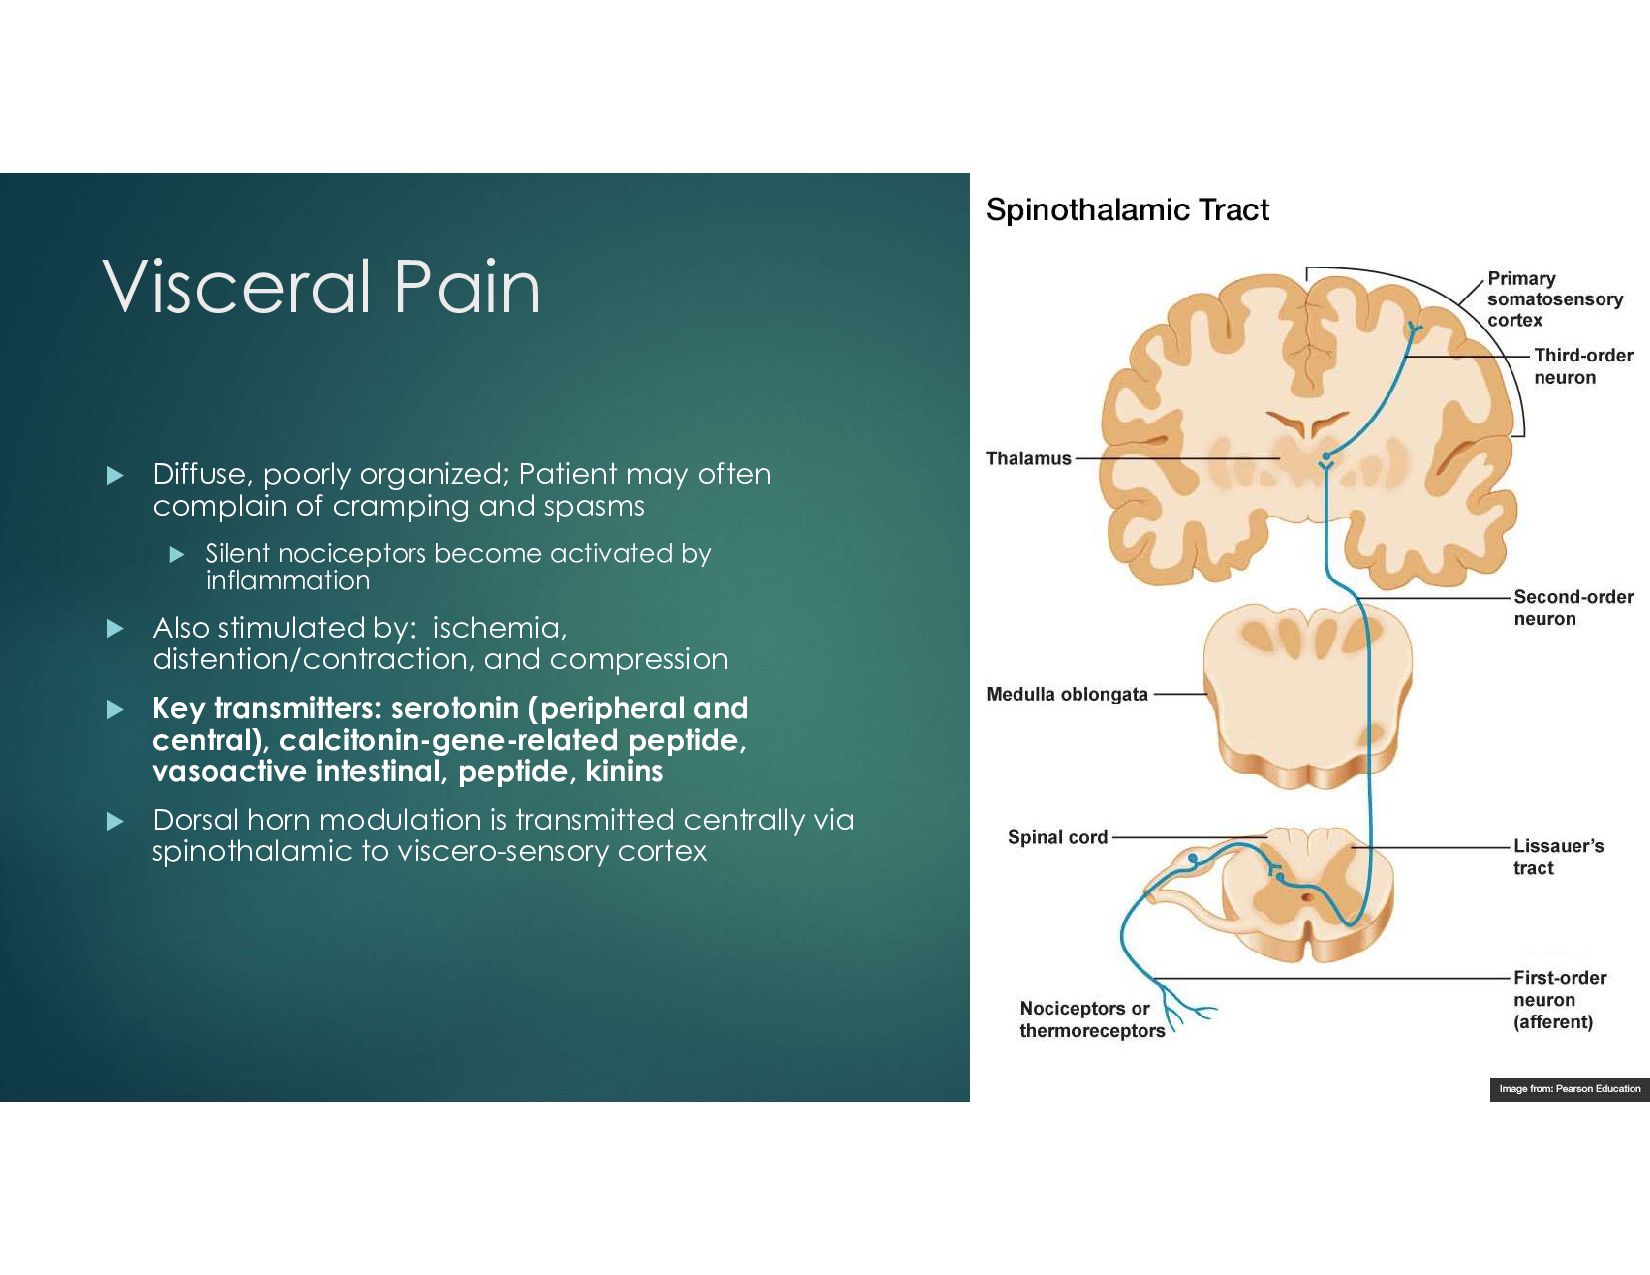
Visceral Pain Diffuse, poorly organized; Patient may often complain
of cramping and spasms Silent nociceptors become activated by inflammation Also stimulated by: ischemia, distention/contraction, and compression Key transmitters: serotonin (peripheral and central), calcitonin-gene-related peptide, vasoactive intestinal, peptide, kinins Dorsal horn modulation is transmitted centrally via spinothalamic to viscero-sensory cortex -
Pharmacologic treatment Antipyretic Analgesic- acetaminophen NSAIDS - OTC
ibuprofen - Non specific - sulindac - Cyclooxygenase II specific Celecoxib and Meloxicam Anticonvulsant Agents Antidepressants Mixed mu agonists Mu agonists Alpha 2 agonists -
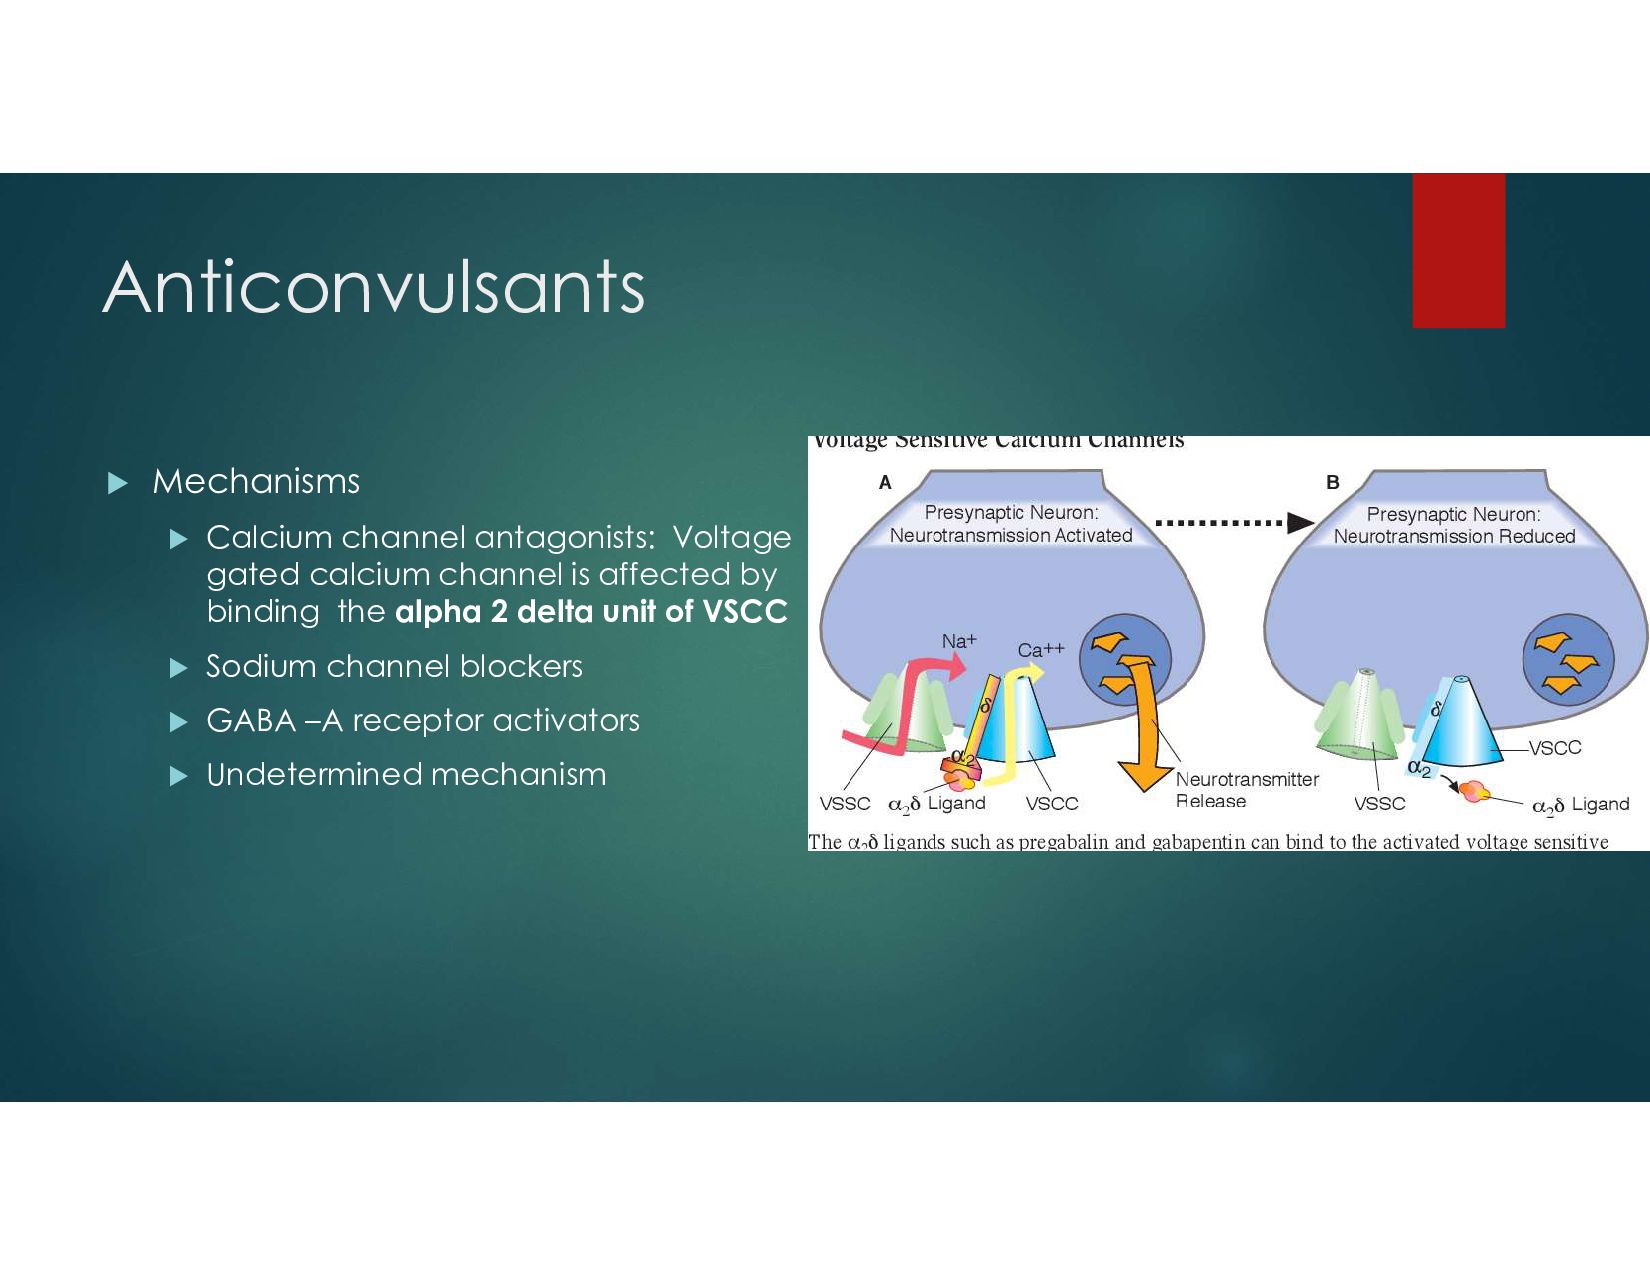
Anticonvulsants Mechanisms Calcium channel antagonists: Voltage gated calcium
channel is affected by binding the alpha 2 delta unit of VSCC Sodium channel blockers GABA –A receptor activators Undetermined mechanism -
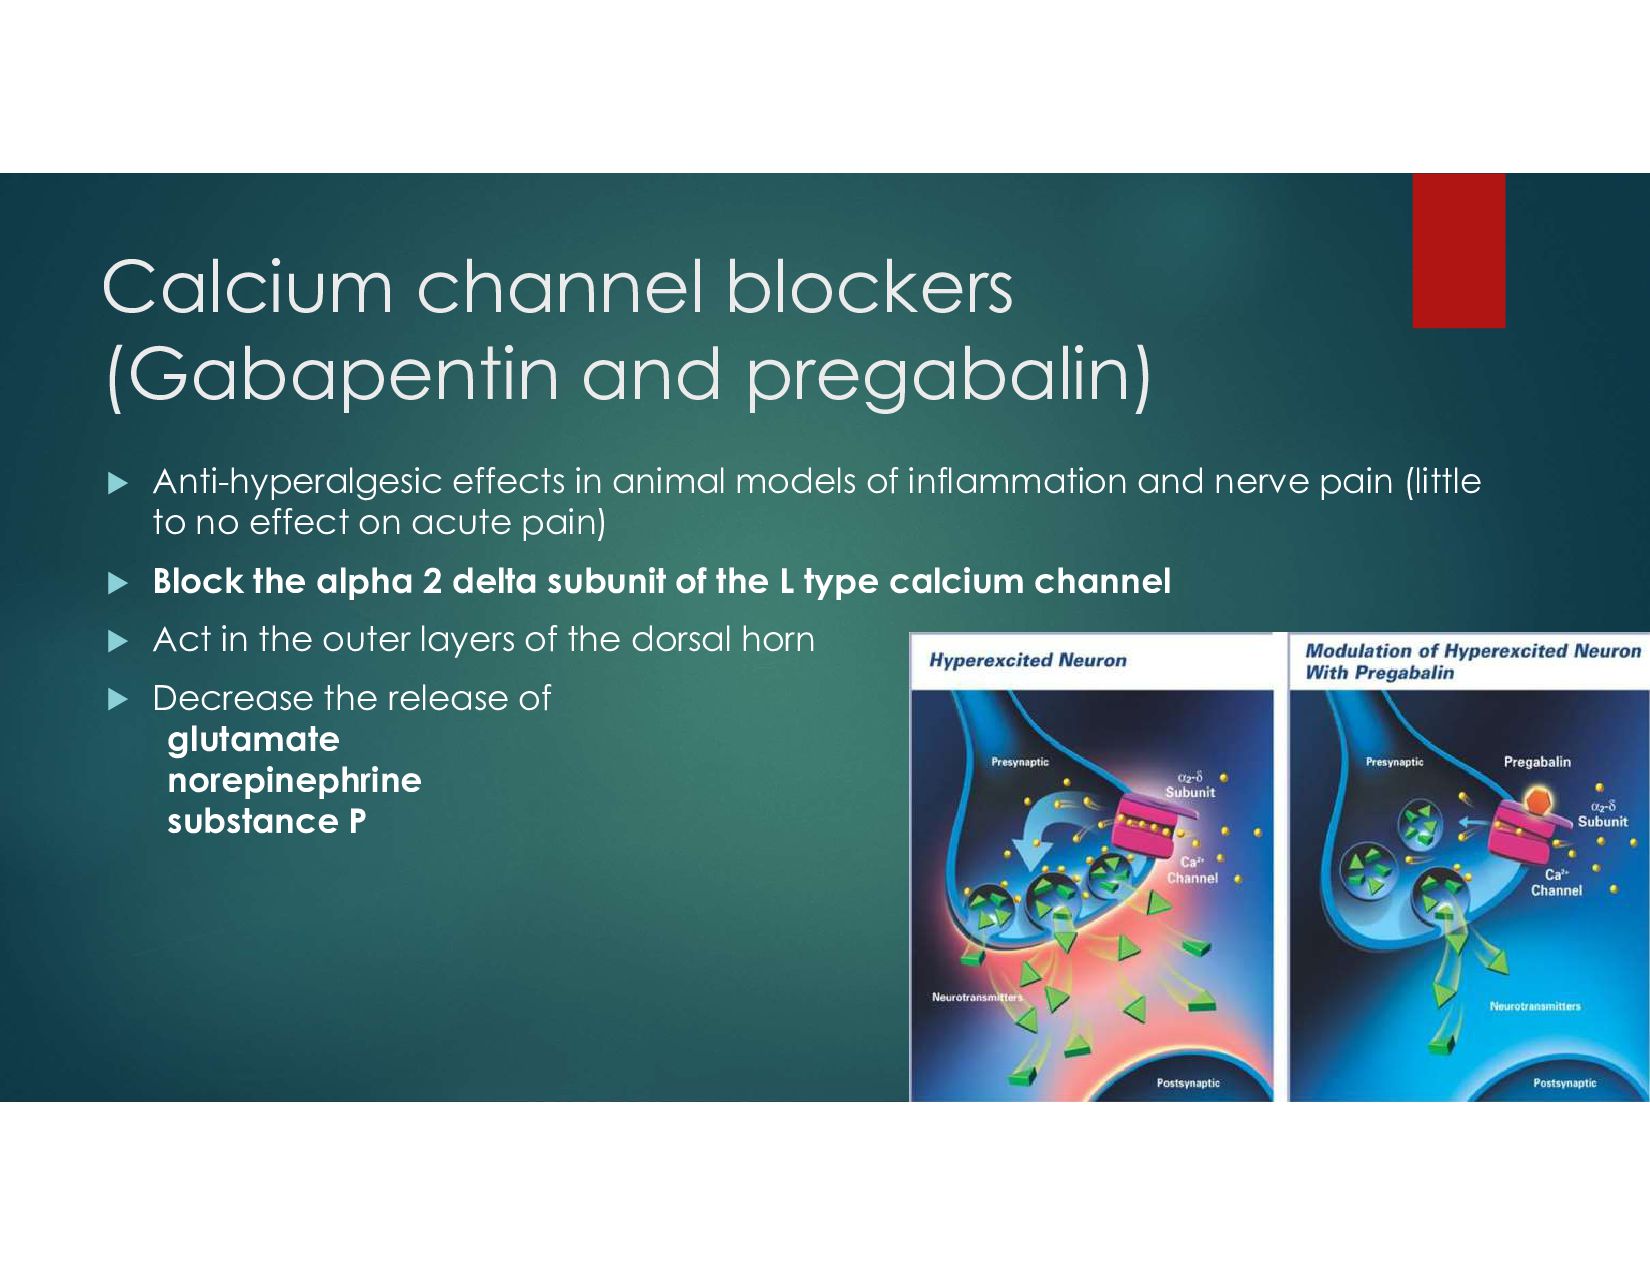
Calcium channel blockers (Gabapentin and pregabalin) Anti-hyperalgesic effects in
animal models of inflammation and nerve pain (little to no effect on acute pain) Block the alpha 2 delta subunit of the L type calcium channel Act in the outer layers of the dorsal horn Decrease the release of glutamate norepinephrine substance P -
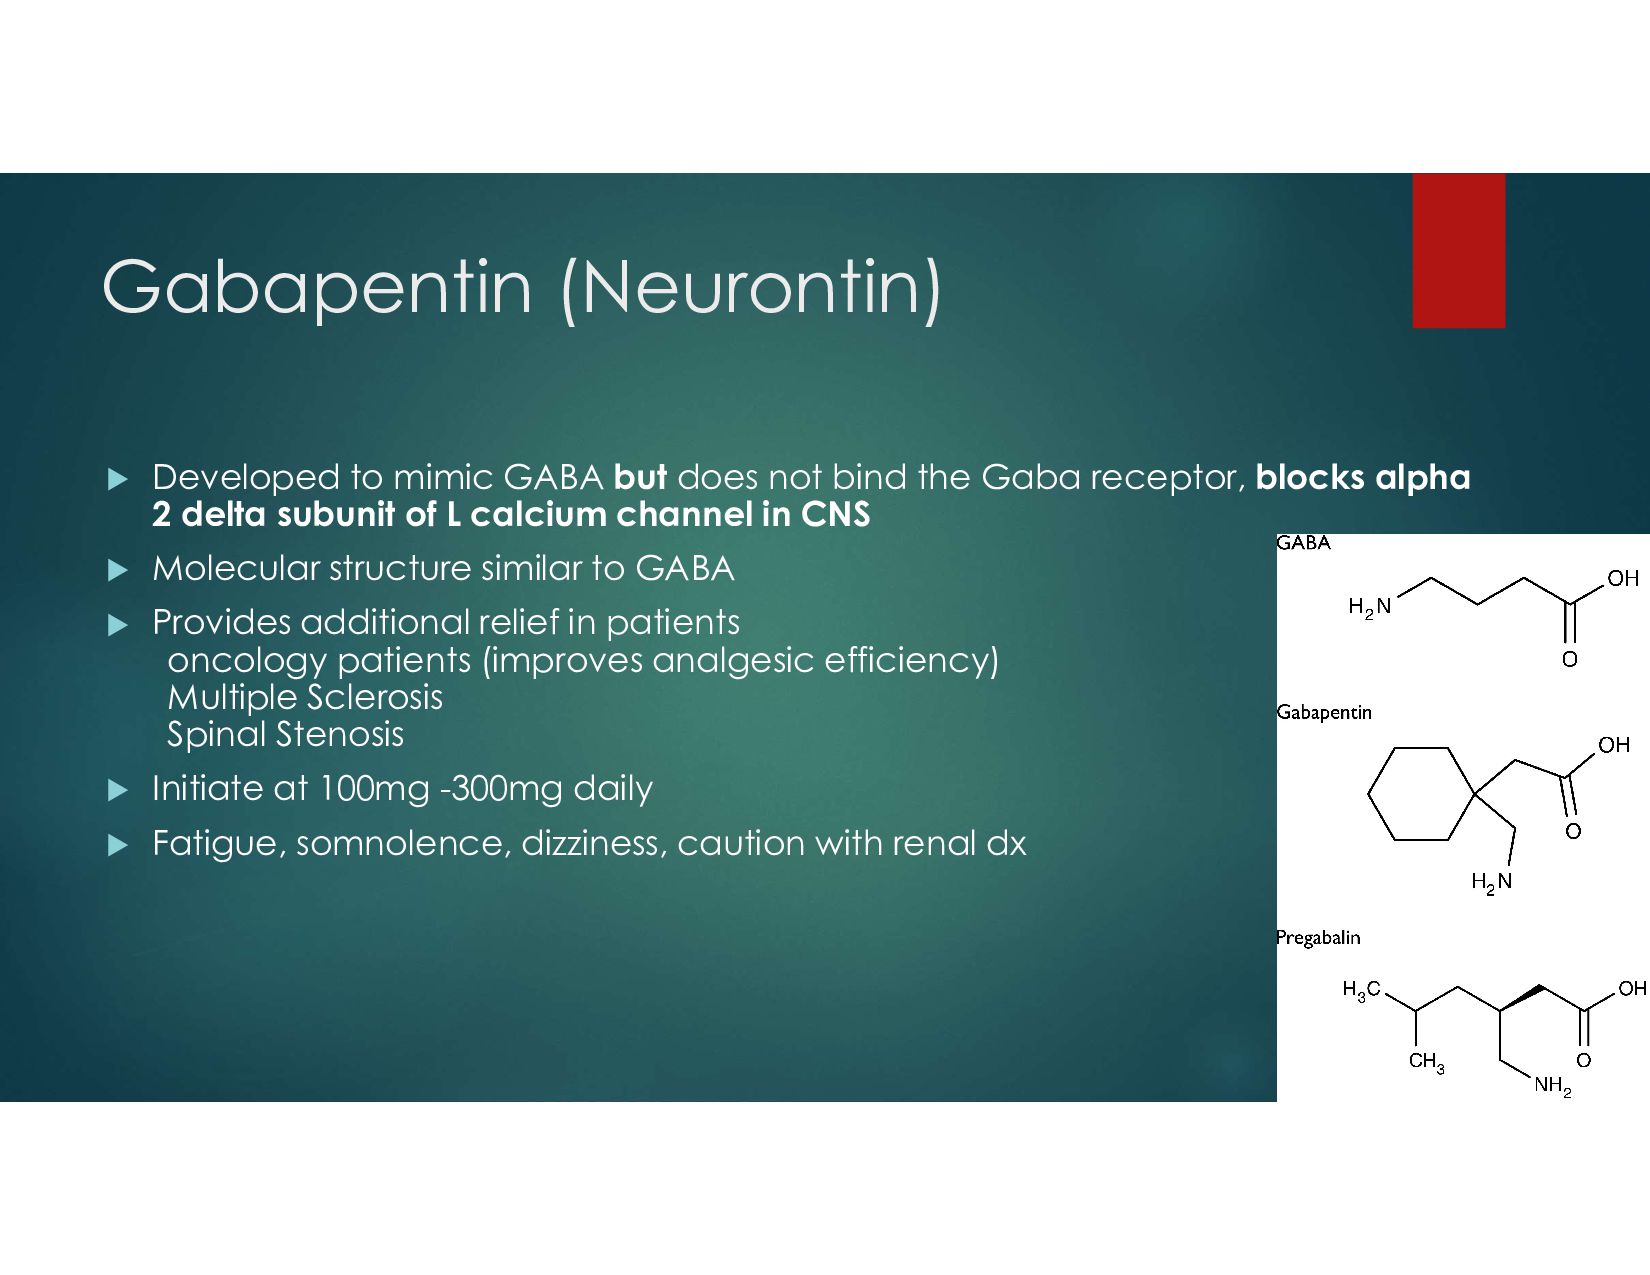
Gabapentin (Neurontin) Developed to mimic GABA but does not
bind the Gaba receptor, blocks alpha 2 delta subunit of L calcium channel in CNS Molecular structure similar to GABA Provides additional relief in patients oncology patients (improves analgesic efficiency) Multiple Sclerosis Spinal Stenosis Initiate at 100mg -300mg daily Fatigue, somnolence, dizziness, caution with renal dx -
Pregabalin (Lyrica) More rapid onset than gabapentin, with max
efficacy at 2 weeks vs 2 months Fewer side effects, but still caution in renal disease Dosed : 25 – 75 mg QHS in elderly to max of 150 mg po/day In Diabetic Neuropathy: NNT =6.3 -
Sodium Channel blockers These are Proven therapy for trigeminal
neuralgia, PHN, DN, CRPS Inhibit development of ectopic discharges Anti-epileptiform/Anticonvulsants Local anesthetics Tricyclic Antidepressants Anti-arrhythmics -
Carbamazepine (Tegretol) Mech: Na channel blockade, selectively blocks active
fibers with no effect on normal functioning A-delta and C-fibers Dose Initial 100mg po bid to tid Side effects: PANCYTOPENIA - agranulocytosis and aplastic anemia; CBC necessary every three weeks (blood tests 2-4 months) Steven Johnson Syndrome Toxic Epidermal Necrolysis Dizziness and gait disturbance Treatment models TG neuralgia- NNT<2, NNH 24 post CVA pain -
Oxycarbamazepine (trileptal) Mech- Na channel blockade Titrate to
600 mg/day Side effects: hyponatremia (<125) dizziness, somnolence, N/V can also suppress bone marrow Treatment models: Diabetic neuropathy, Trigeminal Neuralgia -
Phenytoin (Dilantin) Mech: Na channel blockade, prevents glutamate release
Dose: 100mg Bid Side effects: Change in facial features (coarsening) Gingival hyperplasia sedation changes in motion stability Treatment models: Still used in recalcitrant oncology related pain Increases activity of cP450, decreasing efficacy of methadone, fentanyl, tramadol, mexiletine, lamotrigine, carbamazepine When co-administered with antidepressants, and valproic acid, the decreased activity of p450 will produce increased concentration of phenytoin -
Lamotrigine (lamictal) Mech: stabilizes the slow Na channel >
suppress glutamate release Dose 25mg bid Side effects: Skin rash rare Steven Johnsons Syndrome, (noted when combined with valproic acid in children) Treatment models: TN, Diabetic Neuropathy, distal sensory polyneuropathy of HIV disease -
Topiramate (Topamax) Mech: Na channel blocker increases GABA activity
inhibits AMPA-type excitatory glutamate receptor Dose start 25 mg QHS Side effects: sedation kidney stones (topiramate inhibits carbonic anhydrase) glaucoma -
Levetiracetam (Keppra) Mech: undetermined Dose 250mg-500mg bid
Not metabolized by p450 Side effects asthenia, dizziness, somnolence, headache -
Mexiletine Dose 150 BID Mech: Na channel blocker
Side effects: nausea blurred vision irritability Class 1B antiarrhythmic (stabilizes membranes) -
Valproate (Depakote) Dose needs to be titrated with blood
levels approximating 50-100 mcg/ml but these doses are never used when treating chronic pain Mech: GABA–A receptor agonist Side effects: CNS depression Target treatment groups: Change in migraine therapy, suppress cns compression by tumor -
Mechanism local anesthetic, Na channel block 12on/12off, rotate
patch Useful near drain sites, chest tubes, recent large incisions Side effects include dizziness and blurred vision and at concentrations of 10mcg/ml, seizure and 25 mcg/ml cardiac depression, but these plasma levels do not result from the patches Lidocaine Patch -
Antidepressants Anti depressants have been used to treat depression
associated with chronic pain or resulting from the chronic painful condition There are three basic categories: TCA - example Elavil (amitriptyline) SSRI - example Prozac (fluoxetine; rarely used in oncology patients due to serotonin syndrome) SNRI – example Cymbalta (duloxetine) -
TCA (Tricyclic Antidepressants) Older forms inhibit reuptake of serotonin
and norepi, increasing synaptic levels of these meds They have independent analgesic properties at lower doses Differ in terms of side effects: anticholinergic, (dry mouth, constipation, blurred vision, urinary retention) antihistamine effects (sedation) -
TCA pharmacology Quinidine like properties make them proarrhythmic
TCAs prolong the QT interval TCA decrease seizure threshold Some TCAs have documented analgesic properties All TCAs cause urinary retention, dry mouth, postural hypotension, weight gain Hepatic clearance involves the p450 system Meds which compete for the enzyme will increase levels when co-administered (SSRI, cimetidine, methylphenidate) P450 enzyme inducers will decrease serum TCA levels (phenobarbital, carbamazepine, cigarette smoking) -
SSRI (Selective Serotonin Reuptake Inhibitors) Lower side effect profile
than TCA, but decrease seizure threshold Associated with easy bruising and osteoporosis Side effects include decreased libido, impotence, dystonia, akathisia, rare SIADH Few independent pain properties Never proven to be opioid sparing when compared to TCA Taper off slowly -
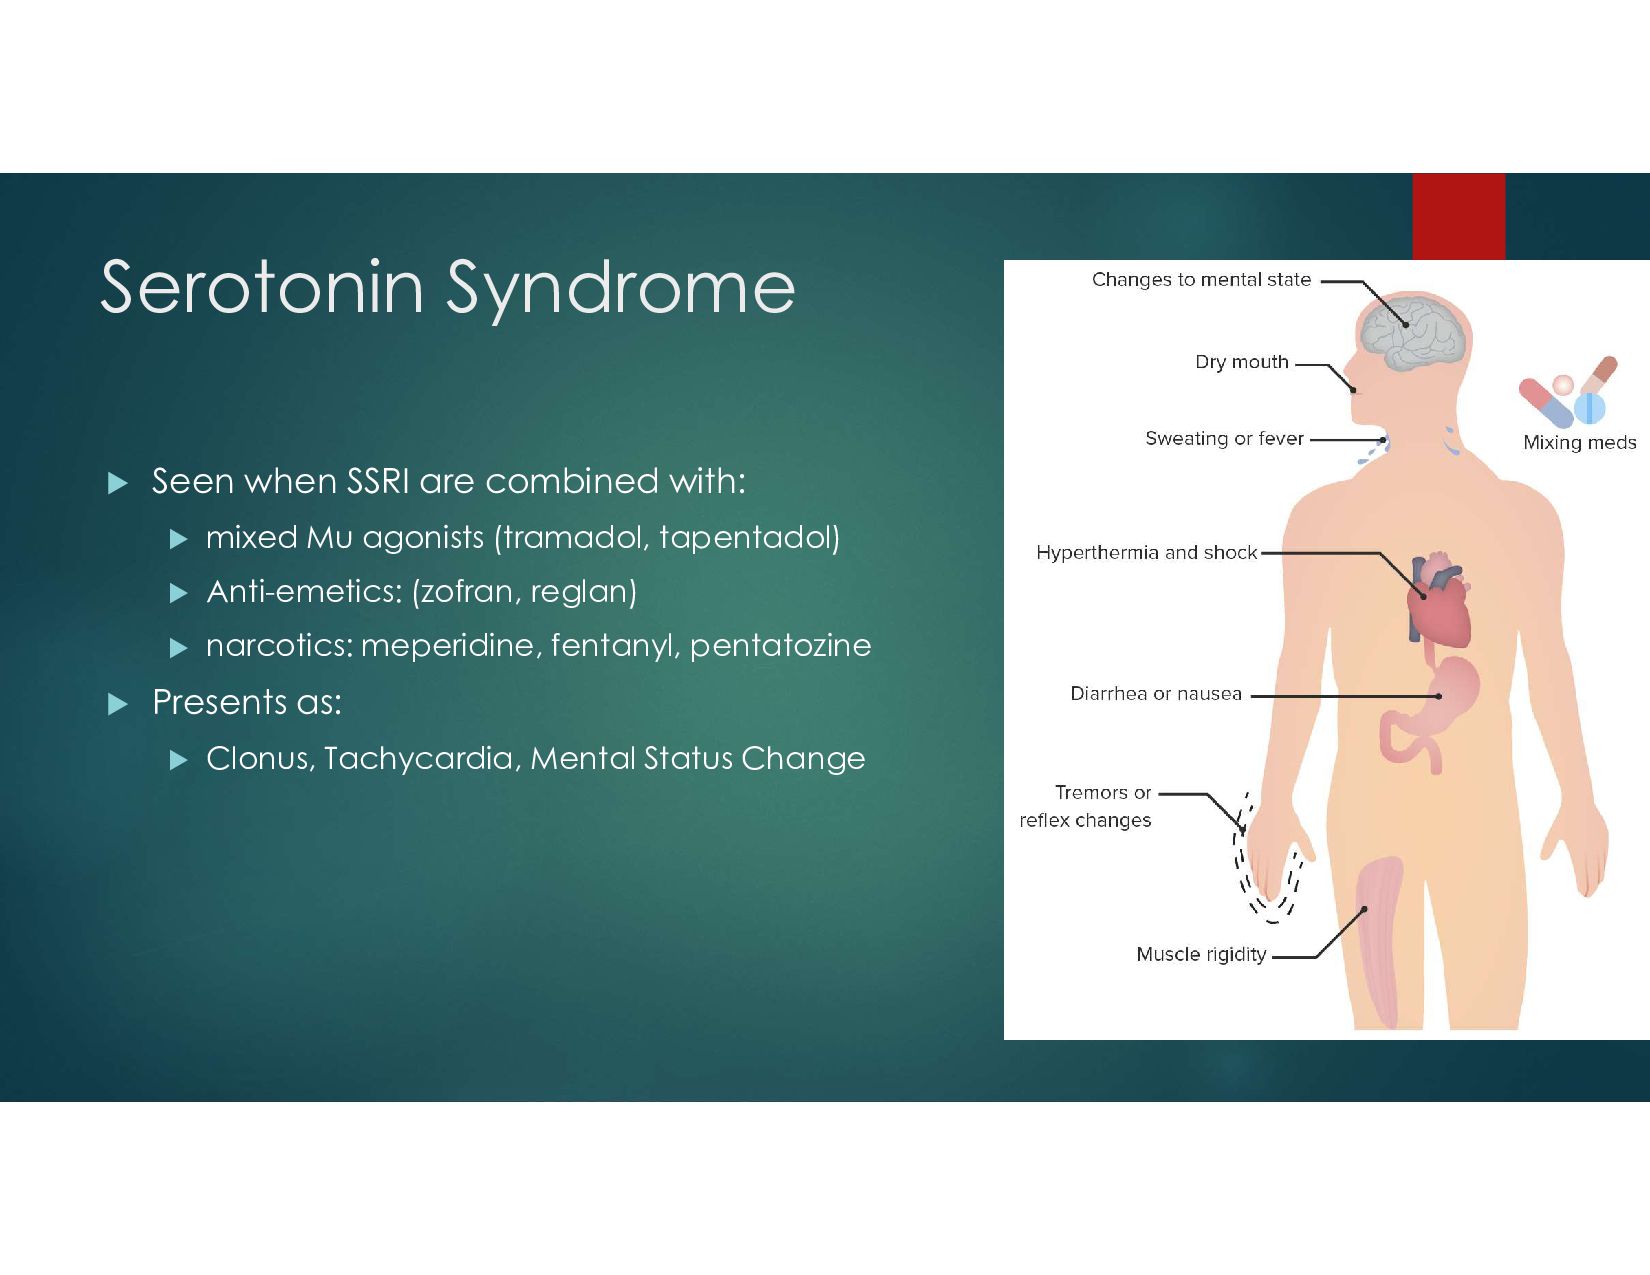
Serotonin Syndrome Seen when SSRI are combined with:
mixed Mu agonists (tramadol, tapentadol) Anti-emetics: (zofran, reglan) narcotics: meperidine, fentanyl, pentatozine Presents as: Clonus, Tachycardia, Mental Status Change -
SNRI (Serotonin and Norepinephrine Reuptake Inhibitors) Inhibit reabsorption of
serotonin and norepinephrine Duloxetine (Cymbalta) indicated for tx of diabetic neuropathy and fibromyalgia Starting dose: 30mg PO Side-effects: dry mouth, dizziness, constipation, 2d6 inhibitor -
Commonly Used Blocks for Abdominal Pain Celiac Plexus Block
Superior Hypogastric Plexus Block Uses: Pancreatitis, acute and chronic Diagnostic Treatment of abdominal ischemia Treatment of acute pain after arterial embolization for cancer pain Treatment of pain secondary to upper abdominal malignancy -
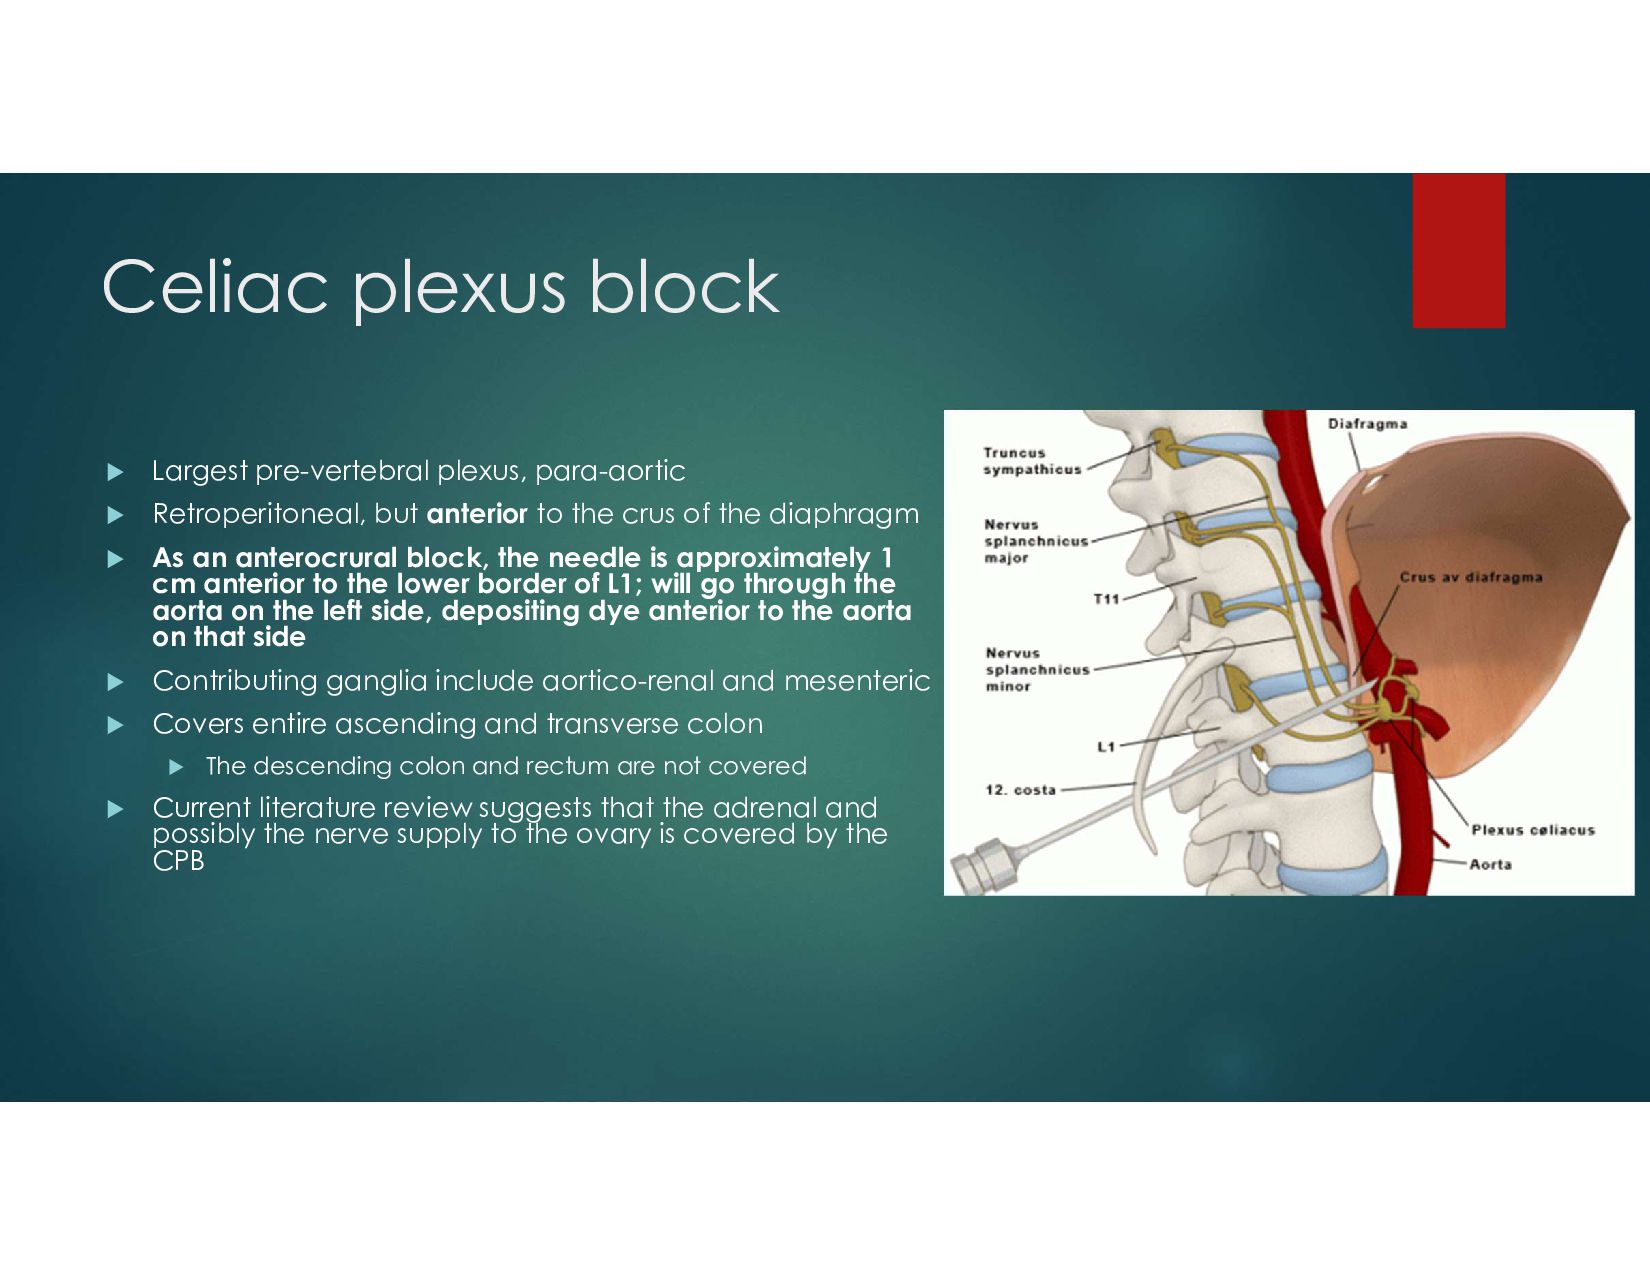
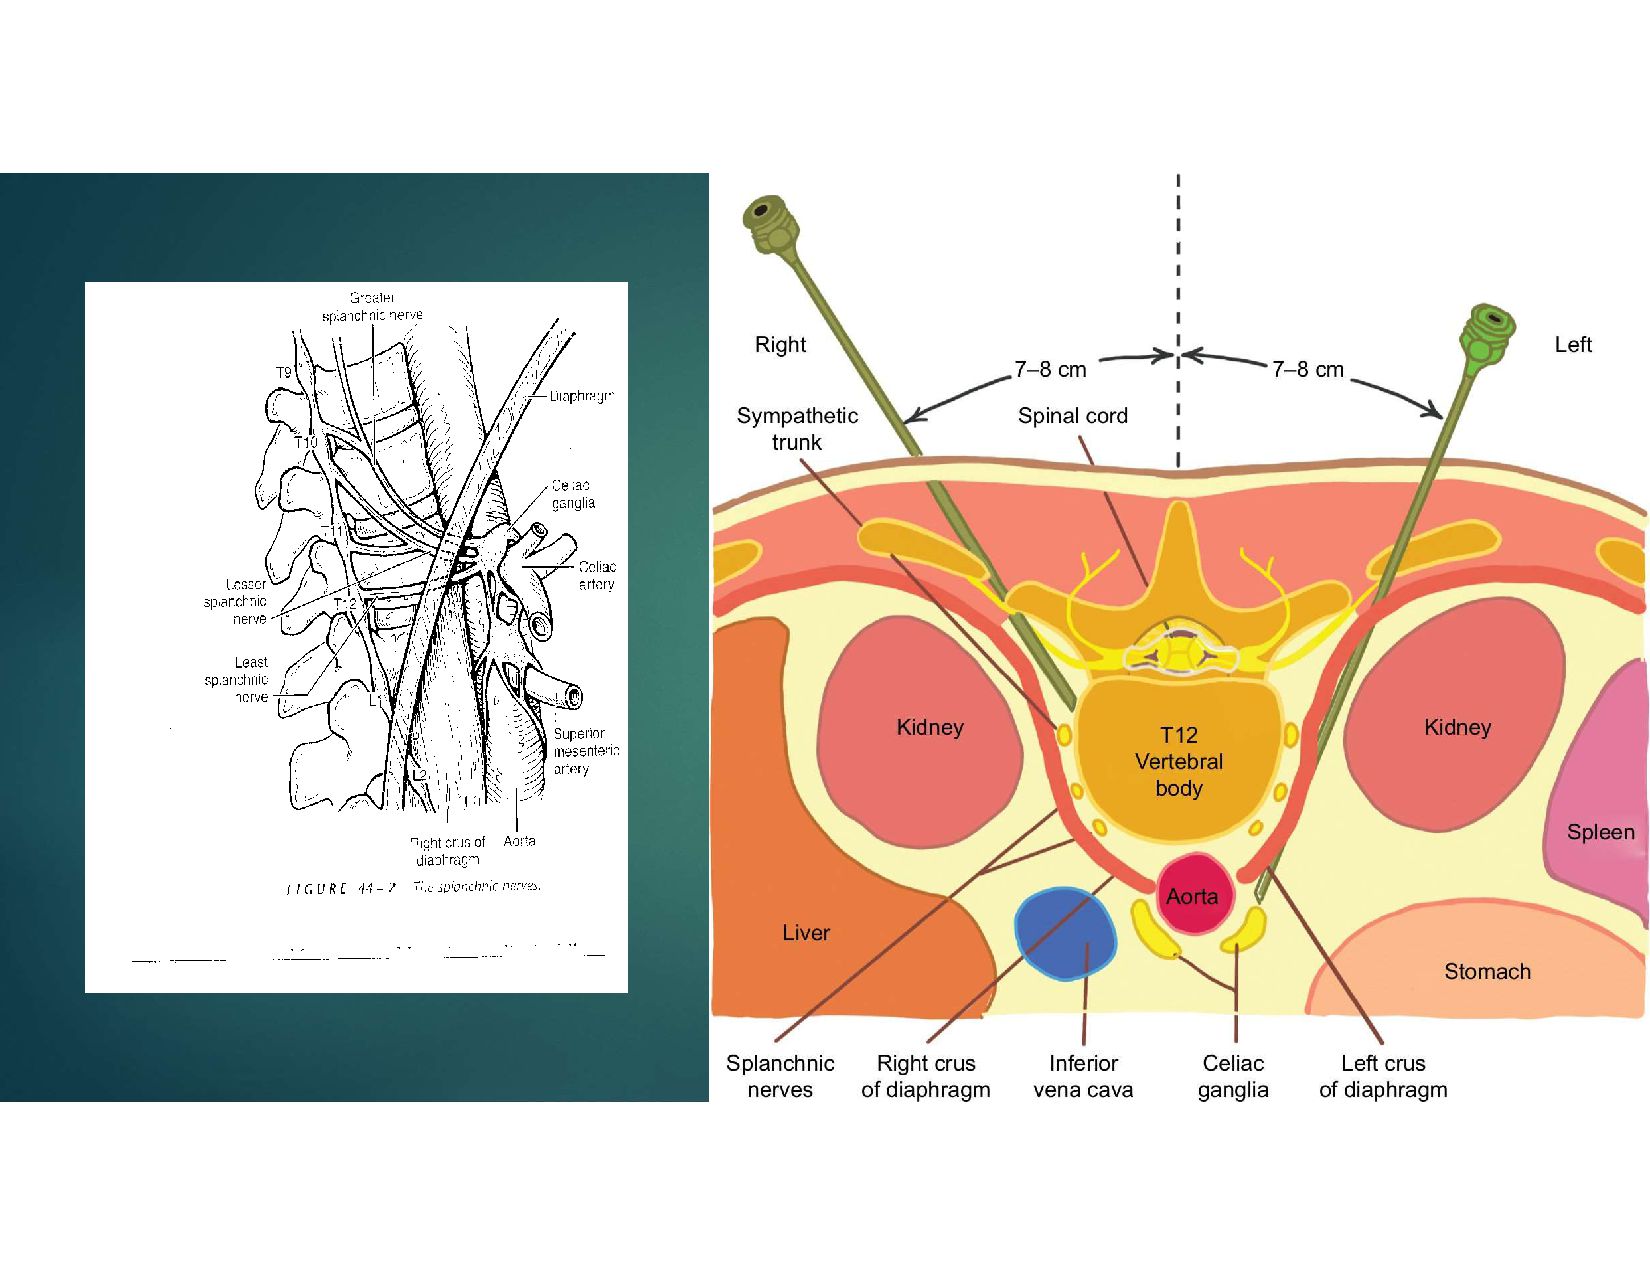
Celiac plexus block Largest pre-vertebral plexus, para-aortic Retroperitoneal,
but anterior to the crus of the diaphragm As an anterocrural block, the needle is approximately 1 cm anterior to the lower border of L1; will go through the aorta on the left side, depositing dye anterior to the aorta on that side Contributing ganglia include aortico-renal and mesenteric Covers entire ascending and transverse colon The descending colon and rectum are not covered Current literature review suggests that the adrenal and possibly the nerve supply to the ovary is covered by the CPB -
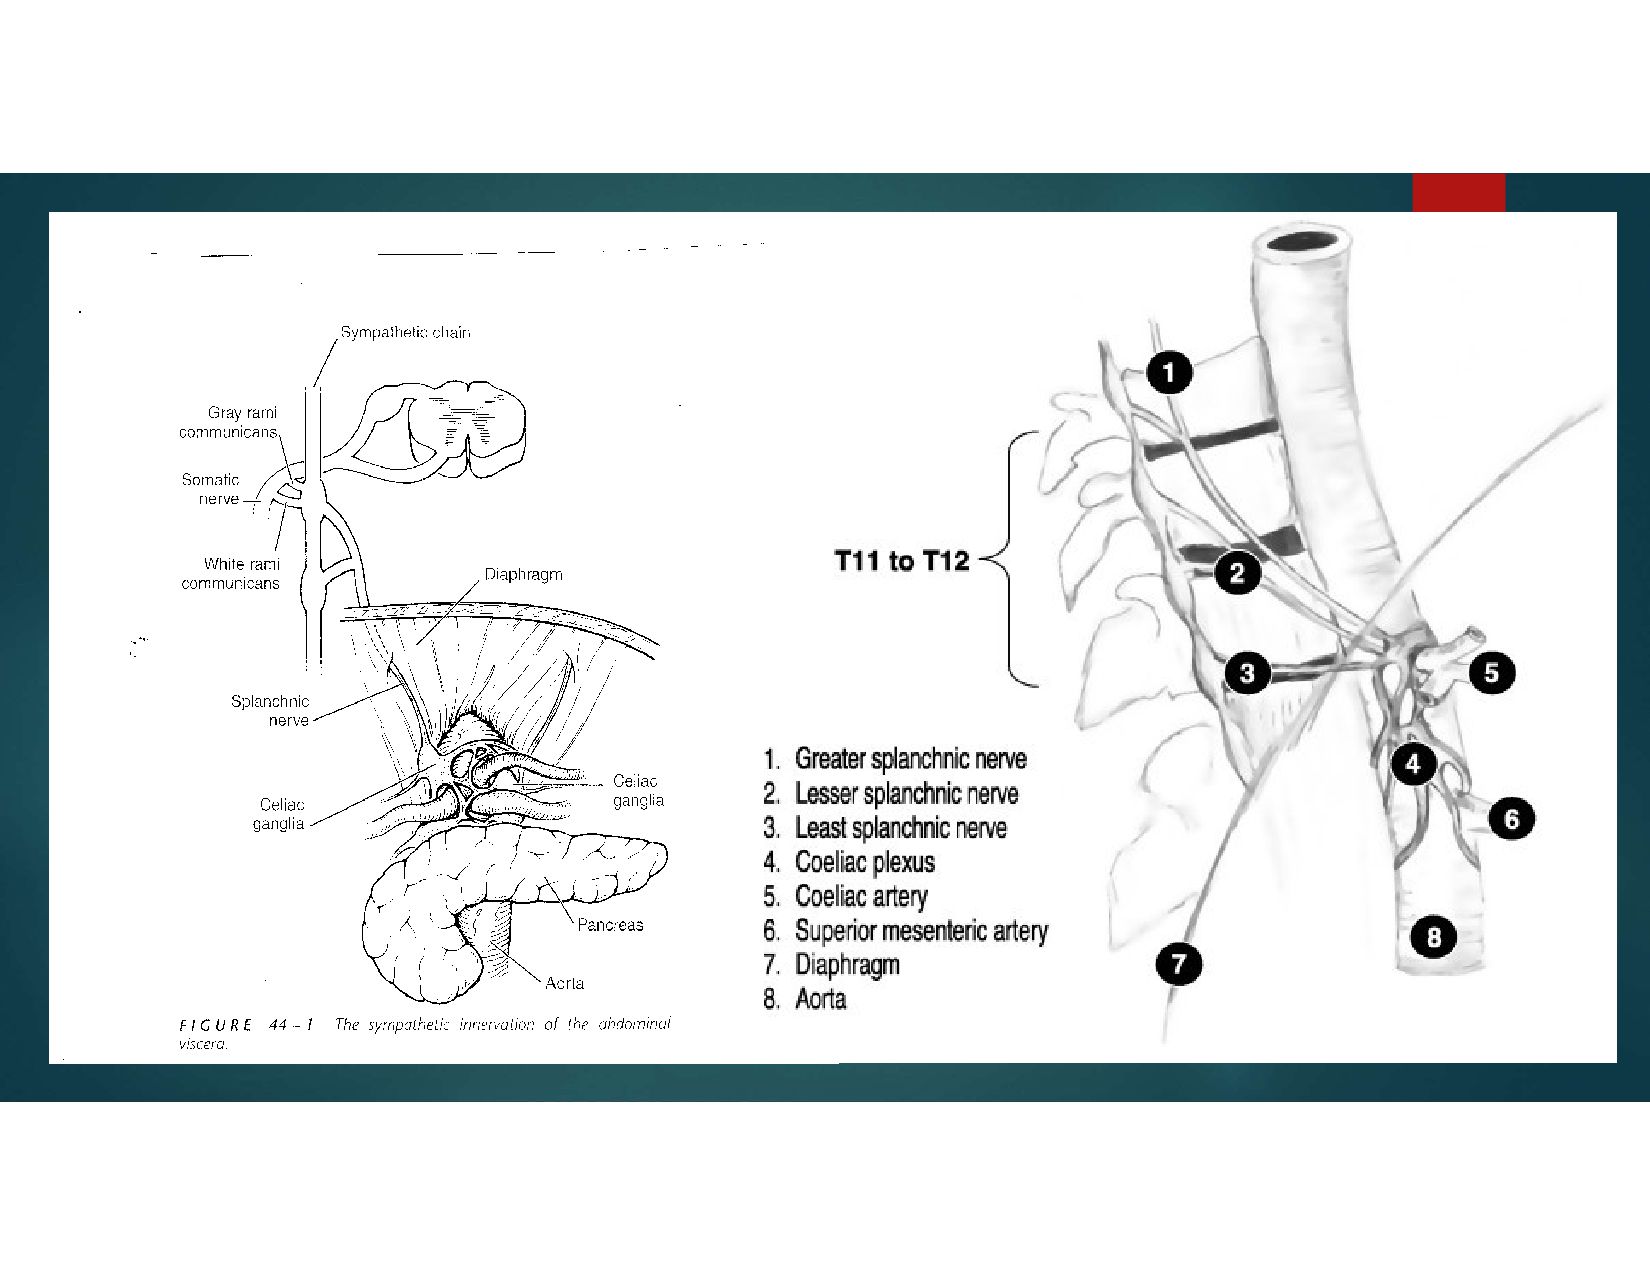
Nerve supply to celiac plexus SYMPATHETIC EFFERENT fibers become
the SPLANCHNIC NERVES Afferent sensory fibers C type silent nociceptors which run with the above fibers Parasympathetic fibers from the vagus nerve Sympathetic afferents -
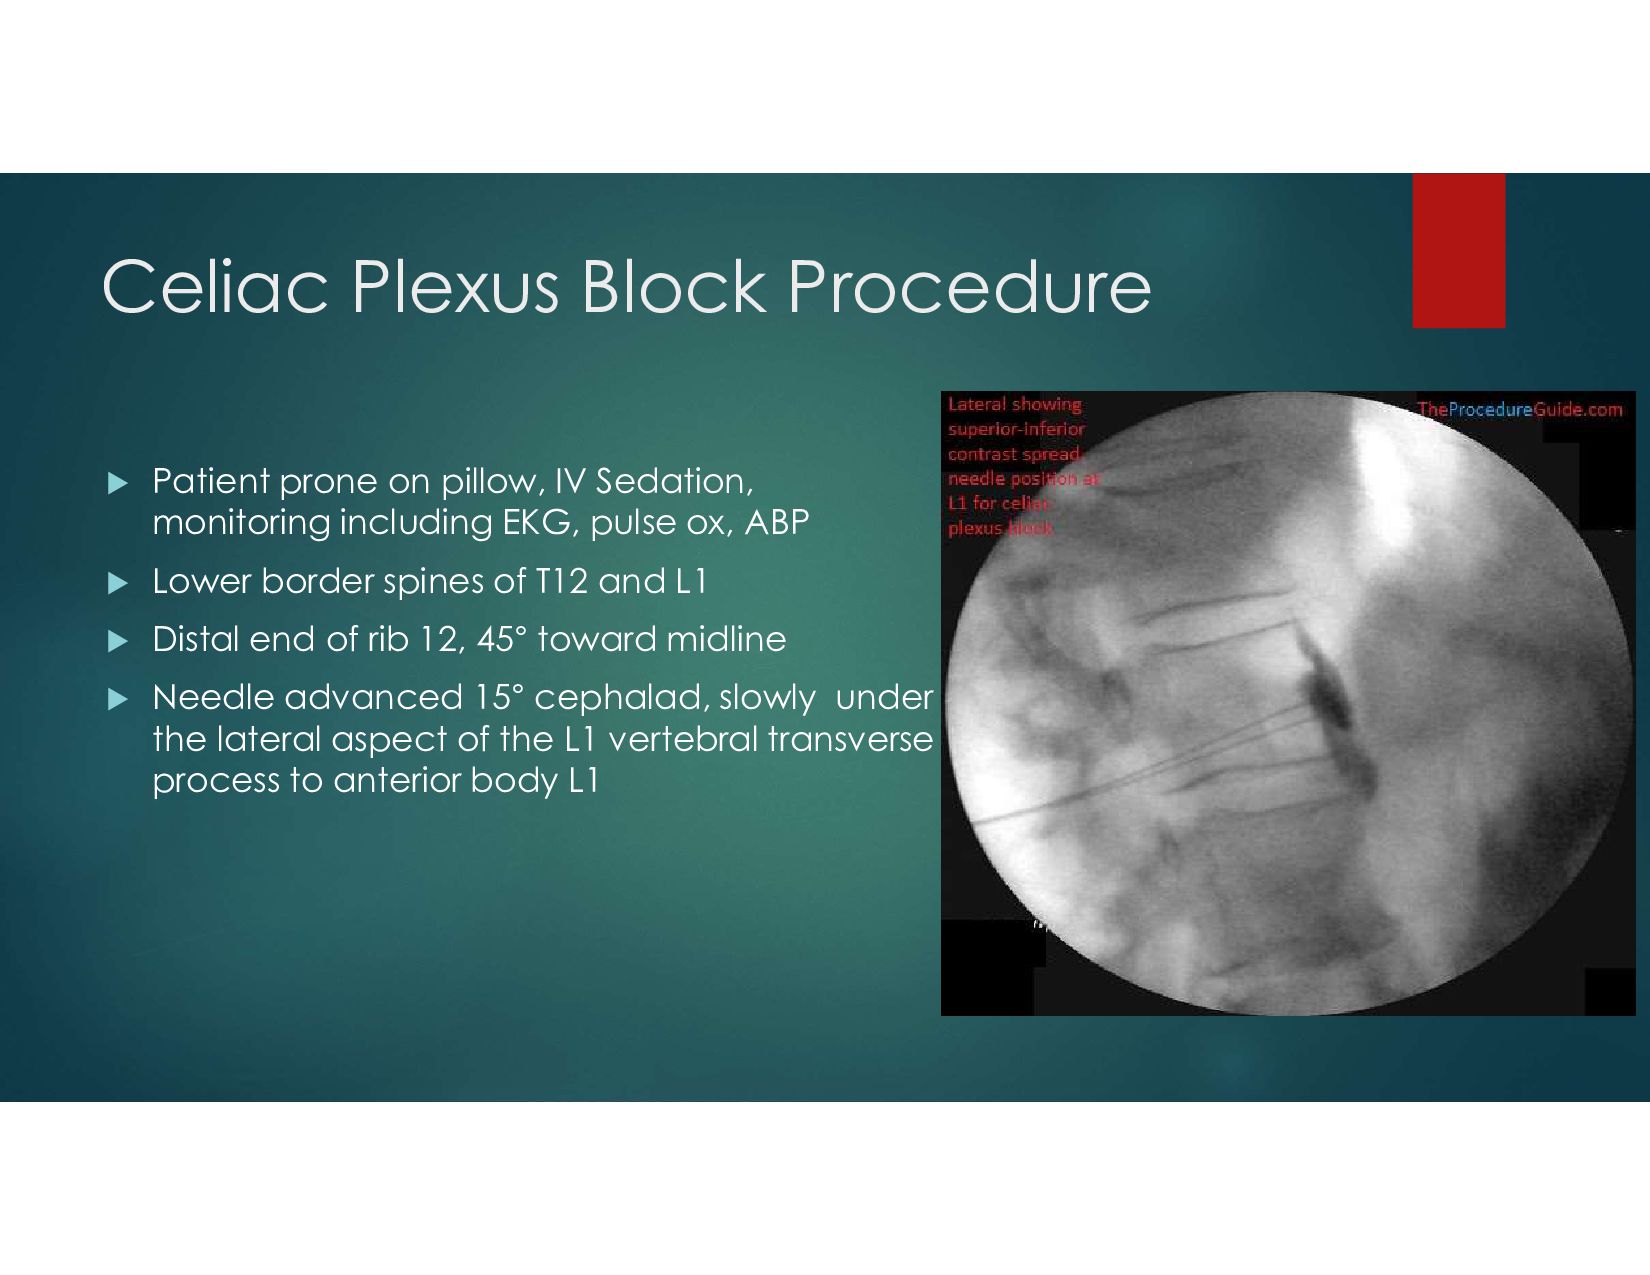
Celiac Plexus Block Procedure Patient prone on pillow, IV
Sedation, monitoring including EKG, pulse ox, ABP Lower border spines of T12 and L1 Distal end of rib 12, 45° toward midline Needle advanced 15° cephalad, slowly under the lateral aspect of the L1 vertebral transverse process to anterior body L1 -
Injection agents Diagnostic nerve block 30ml of dilute
local anesthetic + steroid Neurolytic same volume of phenol or alcohol after successful block following contrast dye study Phenol 6%-12% anesthetic hyperbaric delayed effects Alcohol painful on injection hypobaric immediate effects alcohol has been associated with spasm of the major spinal arteries causing transient paralysis -
Complications Hypotension from sympathetic block Puncture of abdominal
blood vessels Pneumothorax Diarrhea Persistent Hypotension (after lysis) Silent Abdomen Alcohol migration across diaphragm Intravascular alcohol uptake Infection Bleeding -
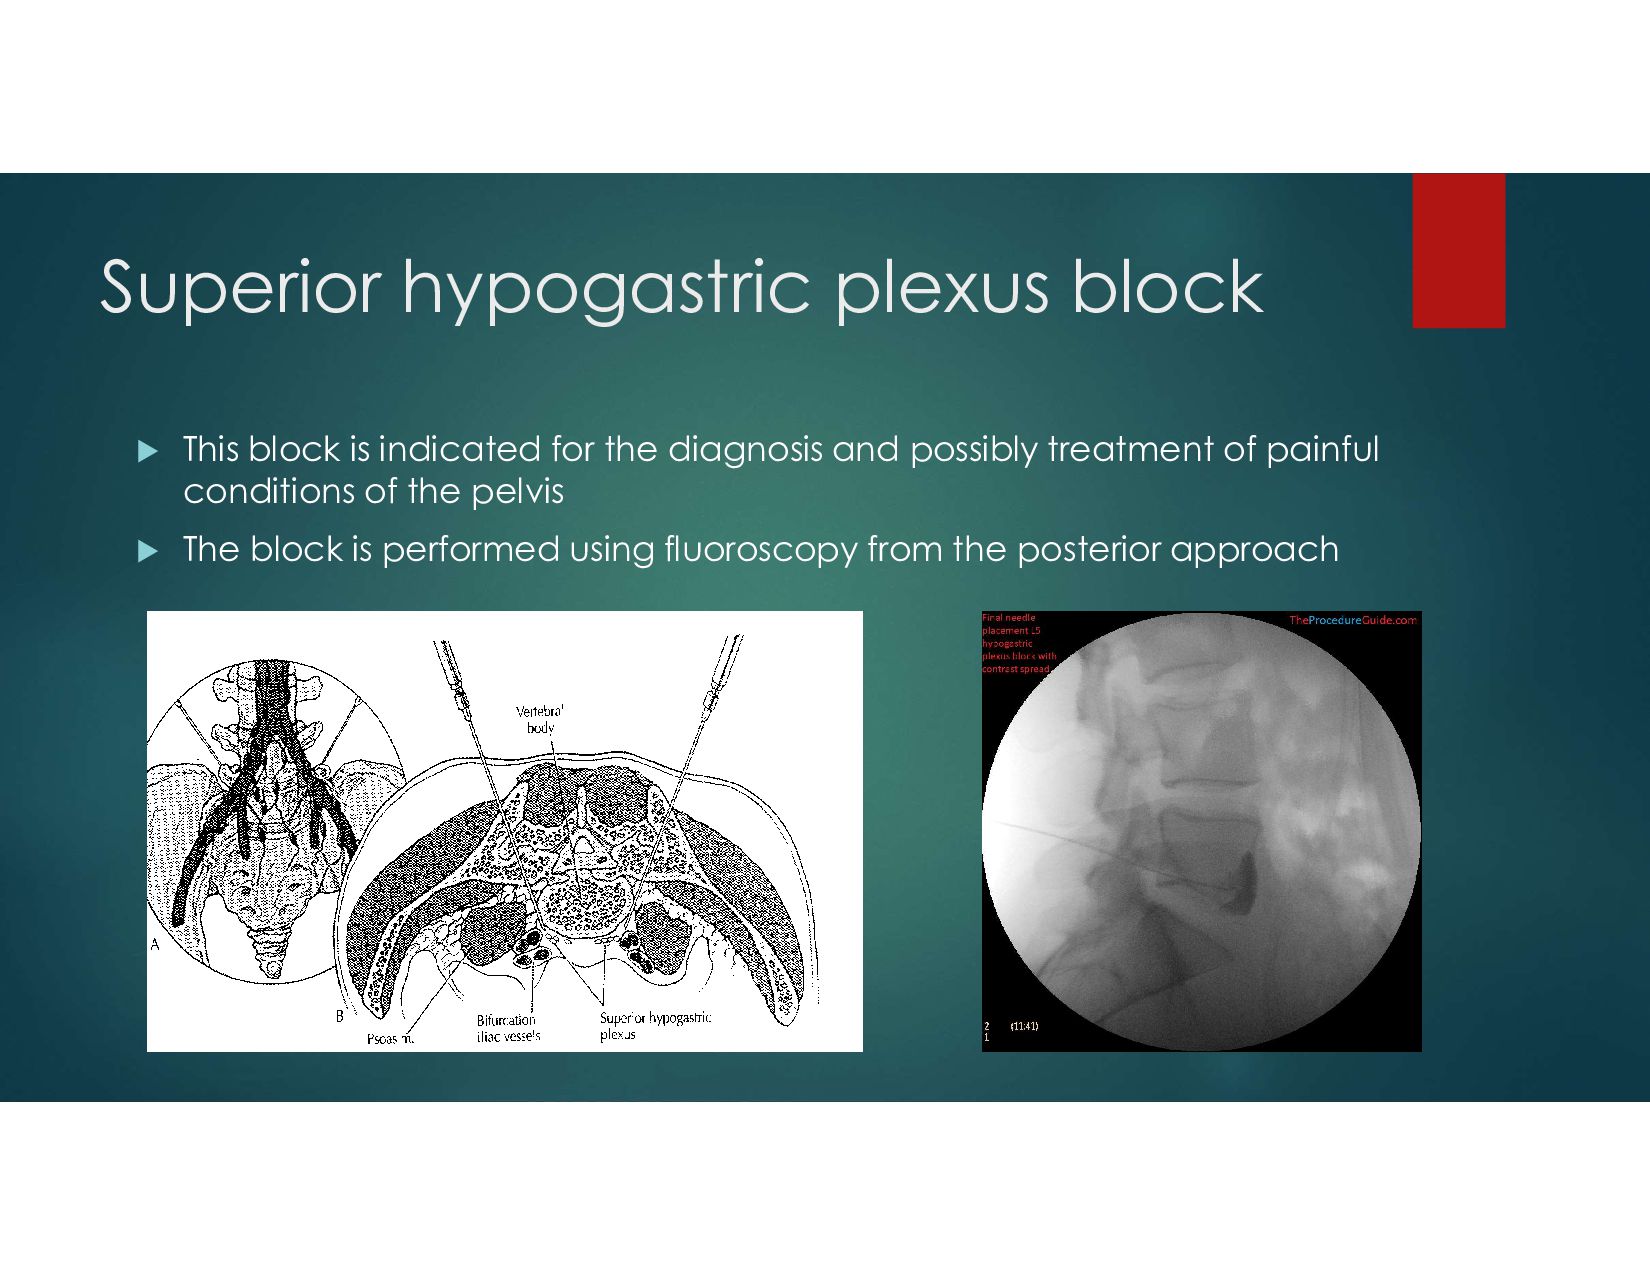
Superior hypogastric plexus block This block is indicated for
the diagnosis and possibly treatment of painful conditions of the pelvis The block is performed using fluoroscopy from the posterior approach -
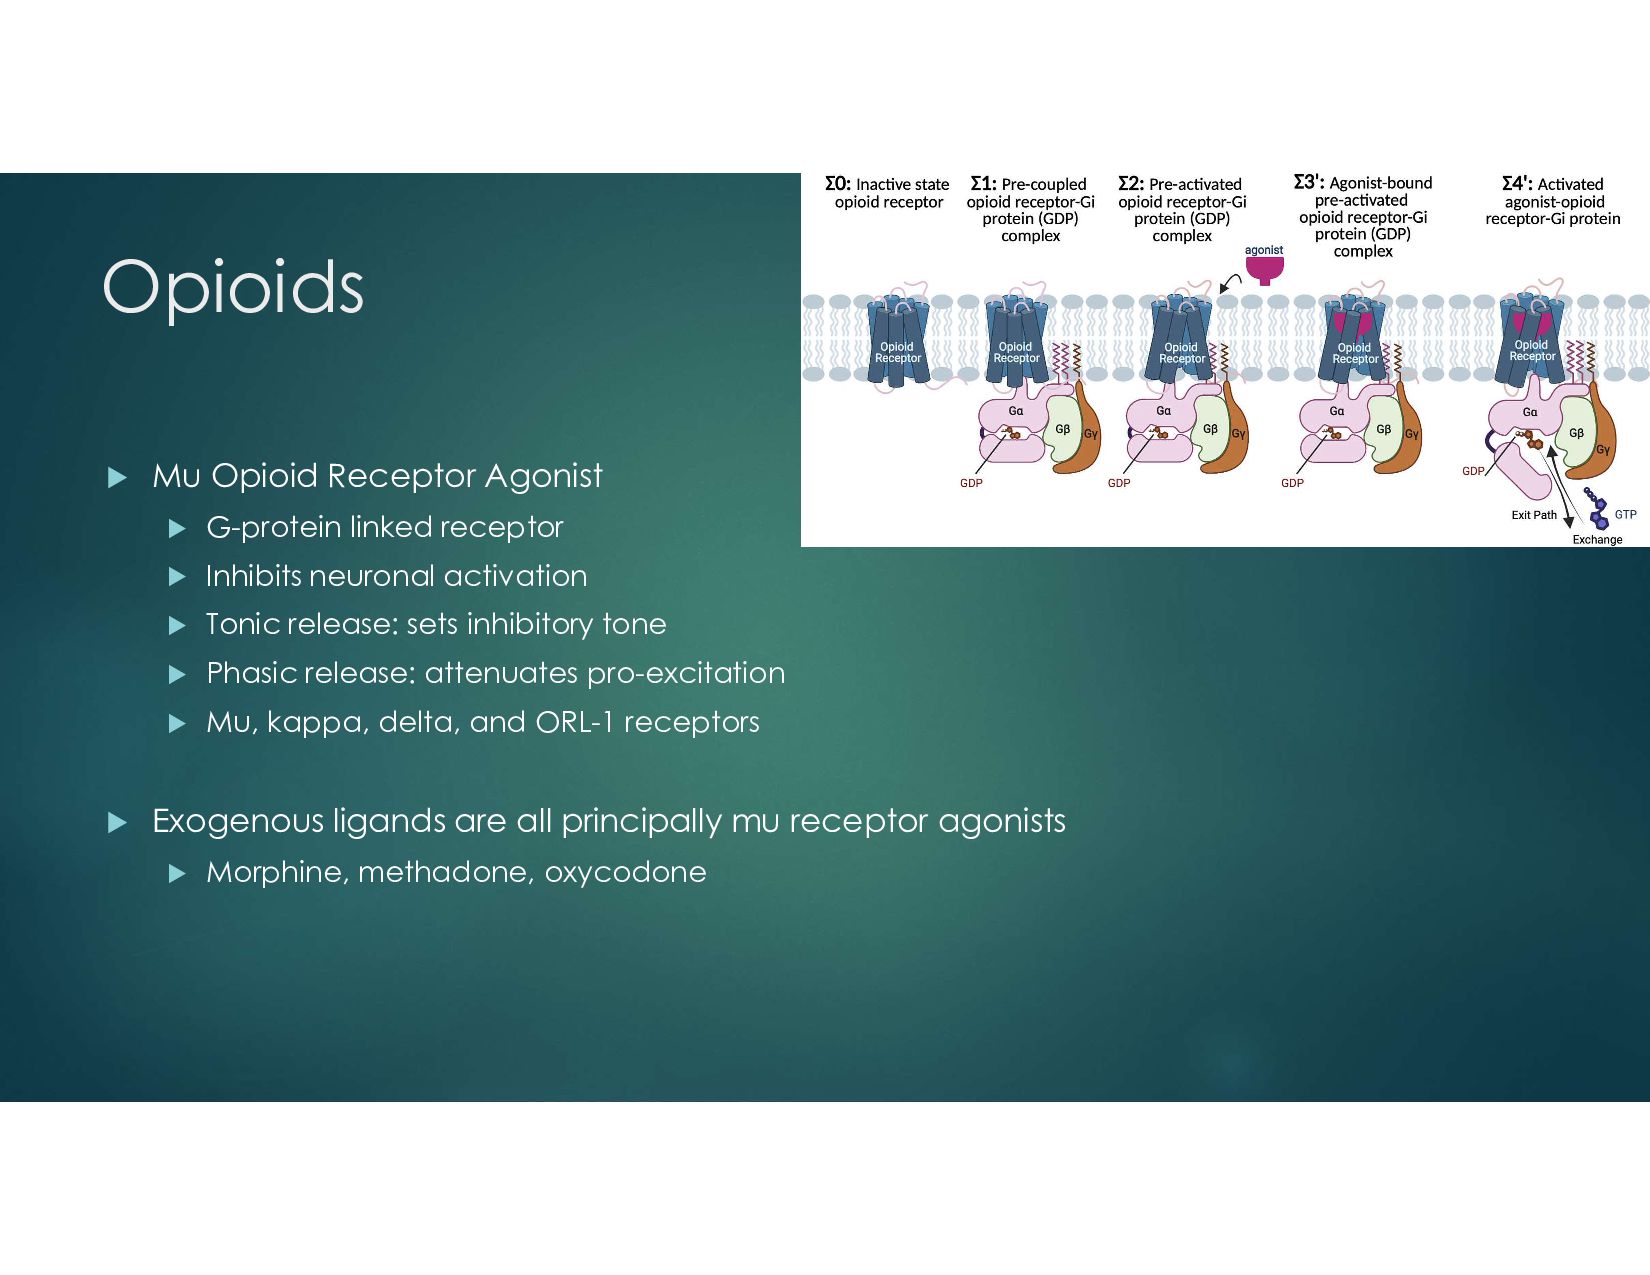
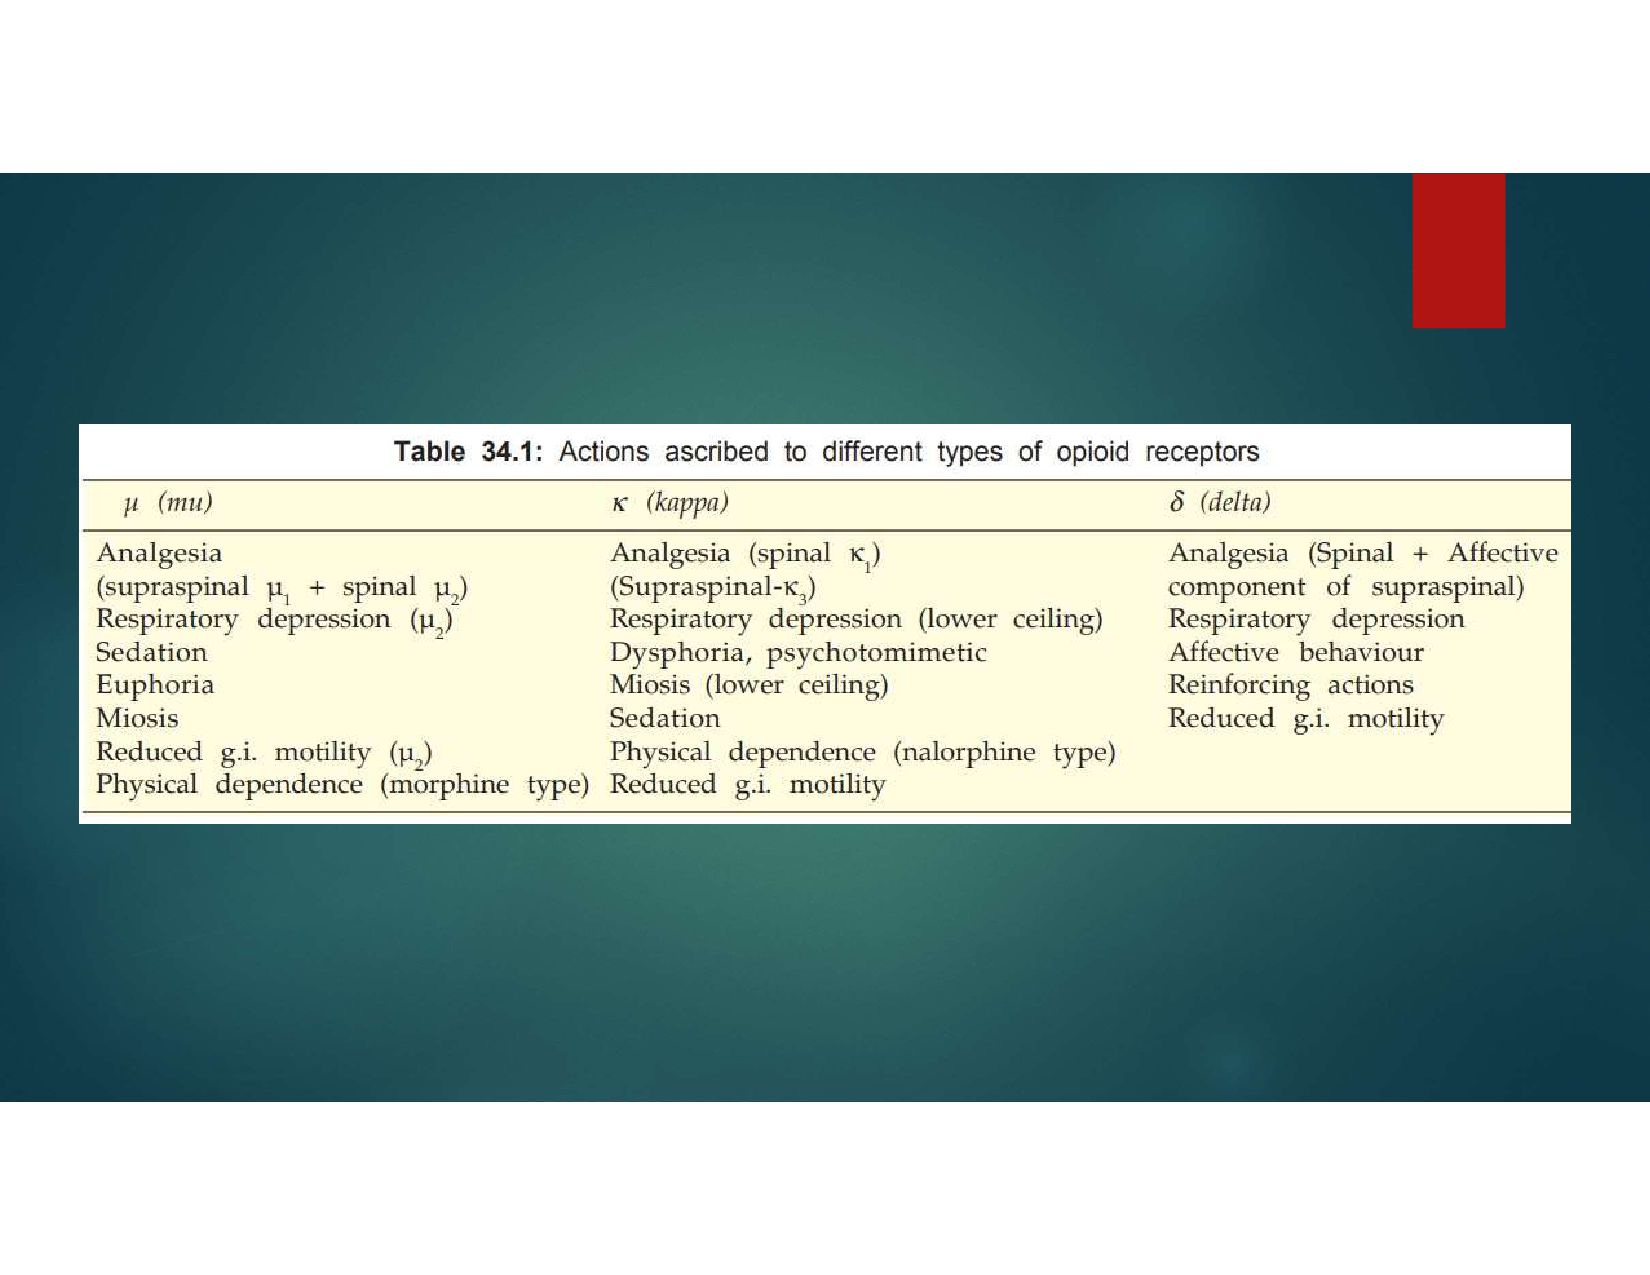
Opioids Mu Opioid Receptor Agonist G-protein linked receptor
Inhibits neuronal activation Tonic release: sets inhibitory tone Phasic release: attenuates pro-excitation Mu, kappa, delta, and ORL-1 receptors Exogenous ligands are all principally mu receptor agonists Morphine, methadone, oxycodone -
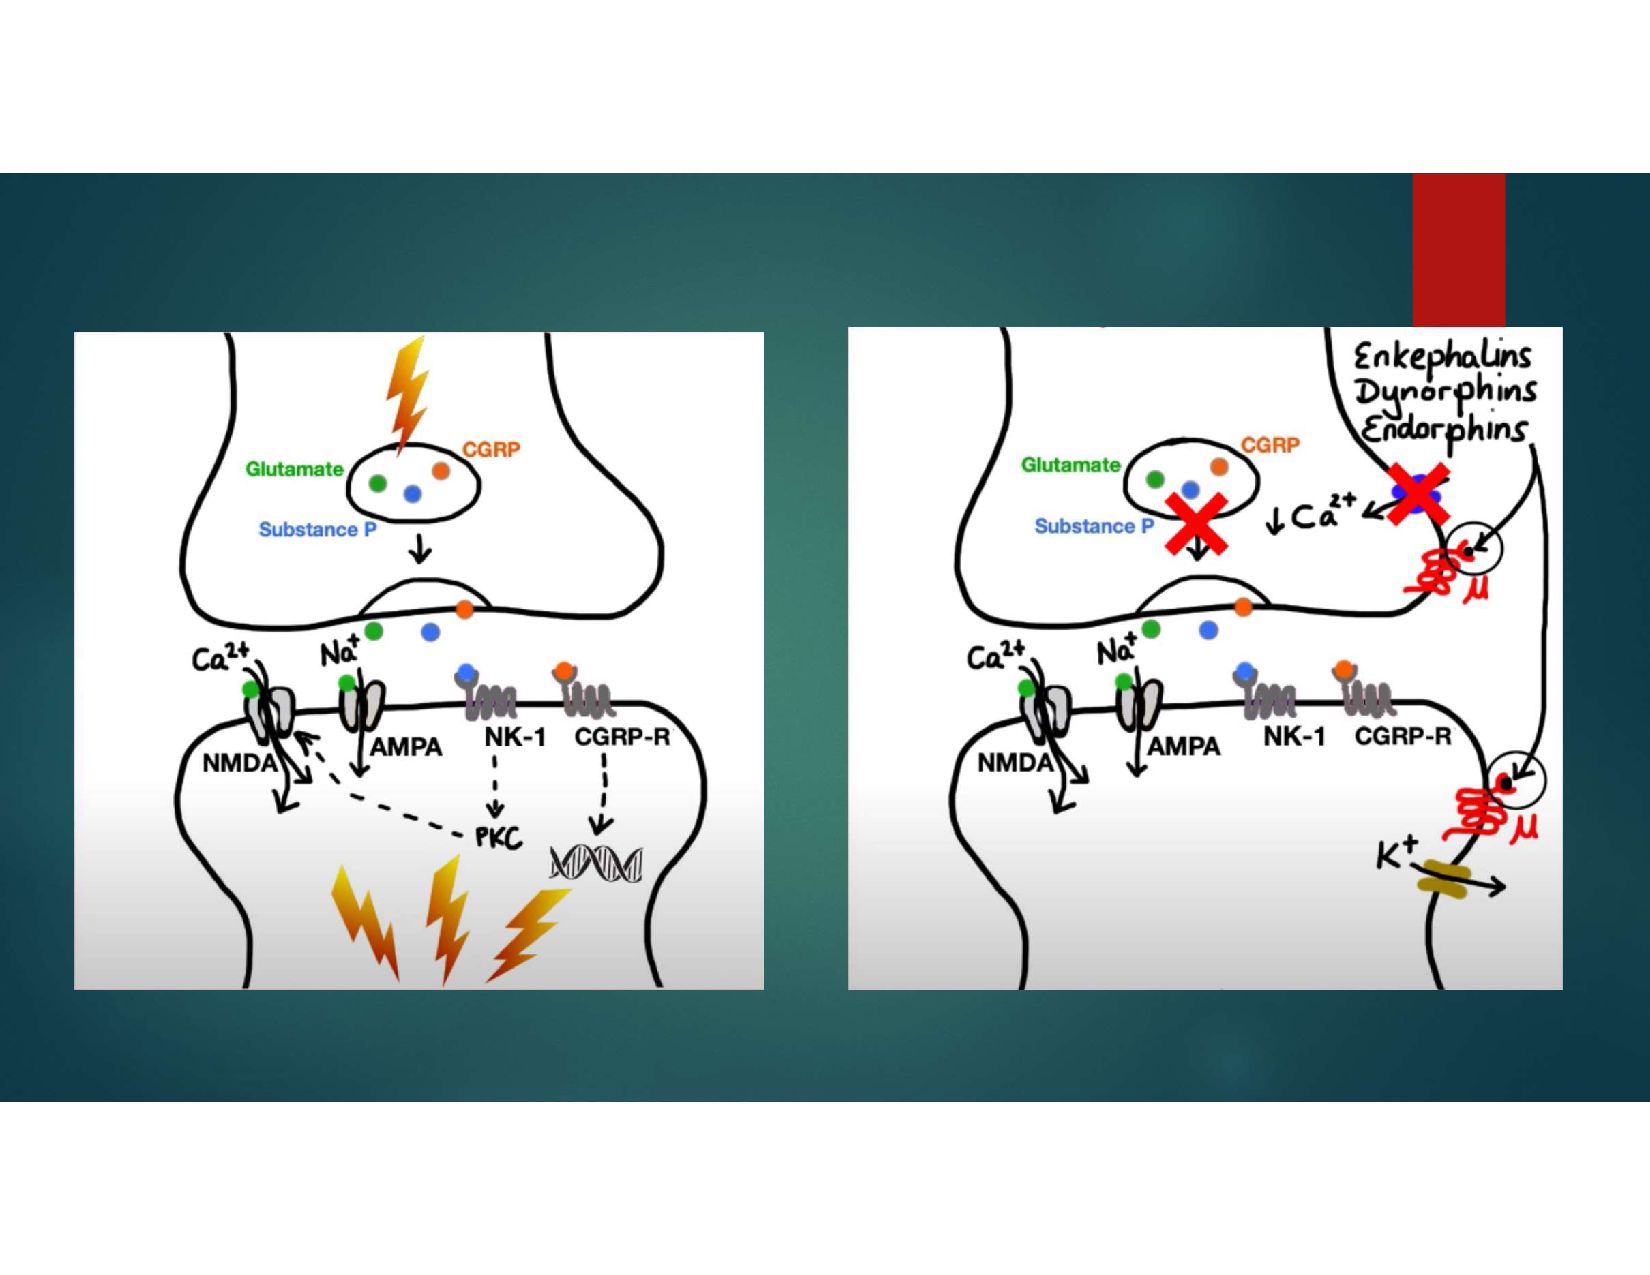
Opioids Opioids mimic the actions of endogenous opioid peptides
by interacting with mu, delta or kappa opioid receptors The opioid receptors are coupled to G1 proteins and the actions of the opioids are mainly inhibitory They close N-type voltage-operated calcium channels and open calcium- dependent inwardly-rectifying potassium channels This results in hyperpolarization and a reduction in neuronal excitability They also decrease intracellular cAMP which modulates the release of nociceptive neurotransmitters (e.g. substance P) -
Other Treatments Neurolytic Blocks Antineoplastic therapies Radiation
therapy Surgical decompression for spinal tumors Non surgical decompression- Cryotherapy, RFA Chemical Denervation of tumor involved areas Augmentation of tumor involved areas Spinal Cord Stimulation Intrathecal Pumps -
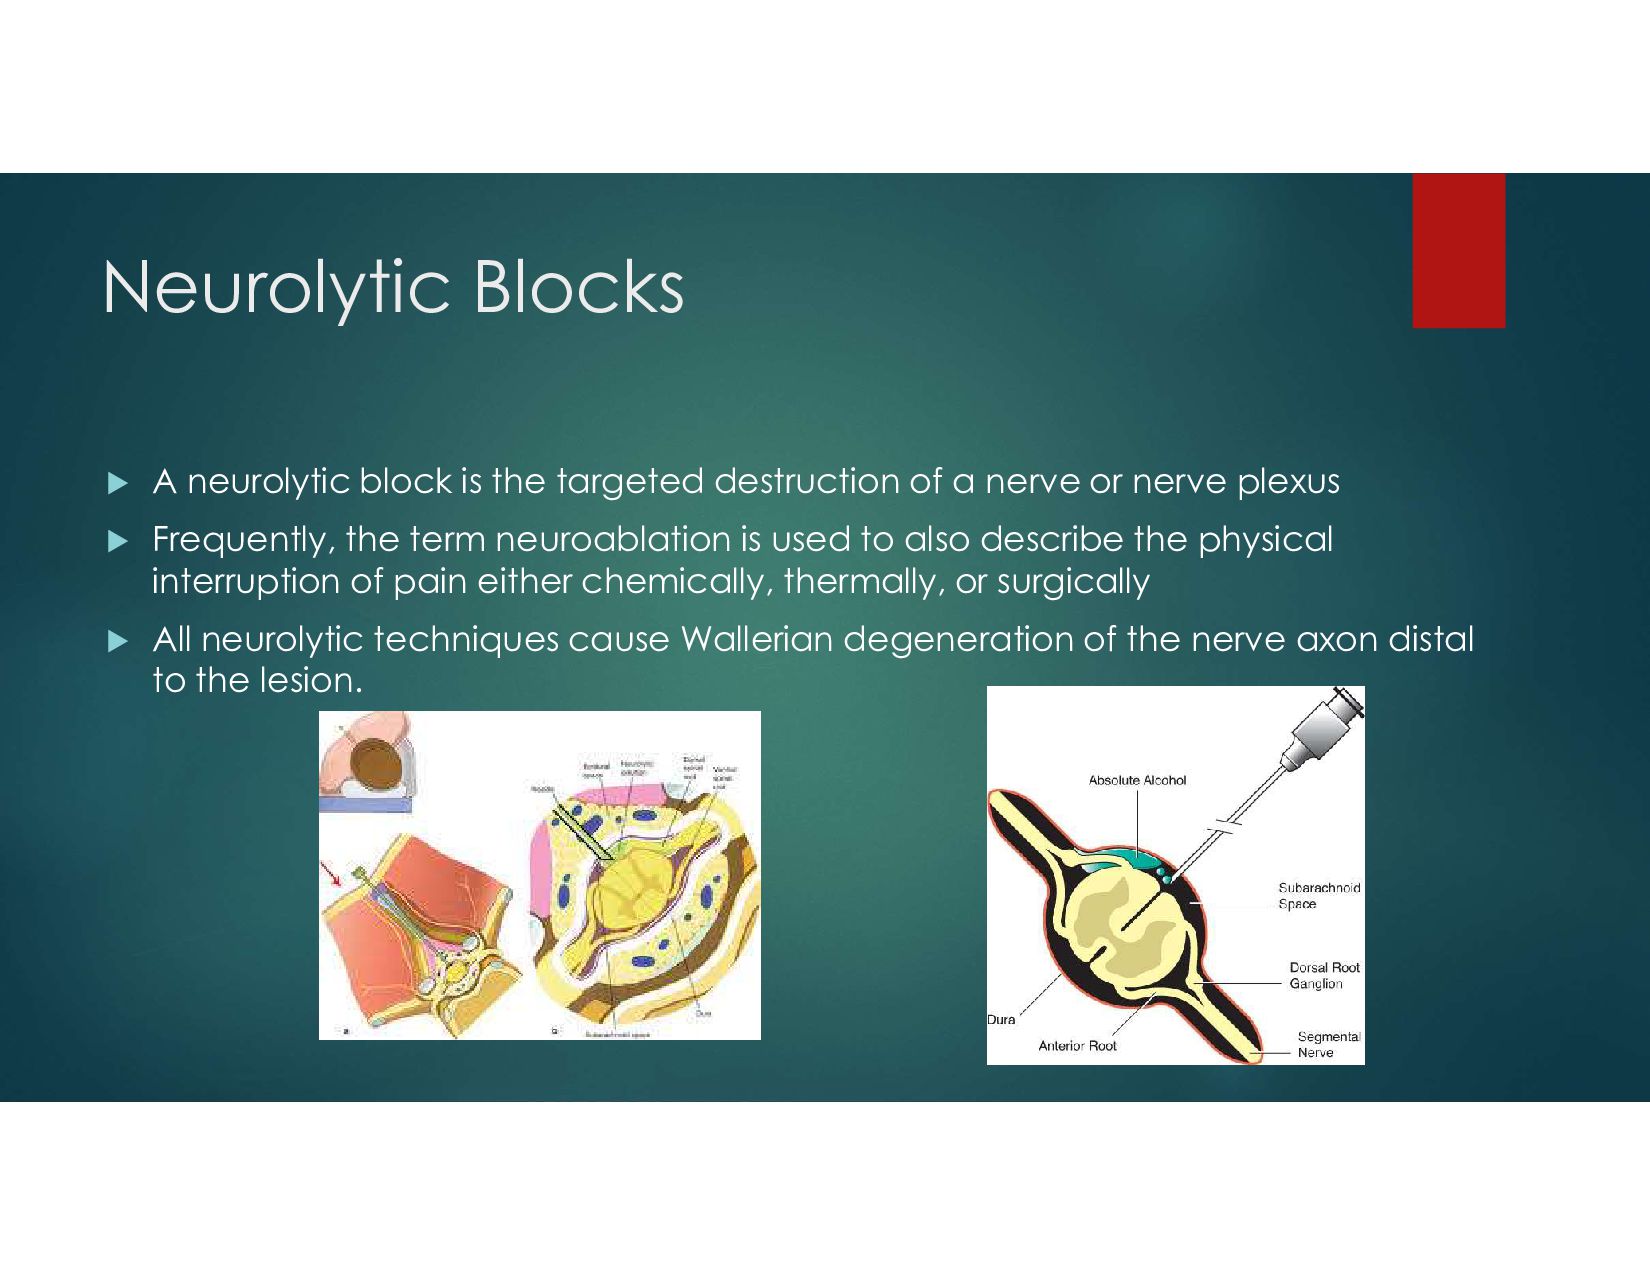
Neurolytic Blocks A neurolytic block is the targeted destruction
of a nerve or nerve plexus Frequently, the term neuroablation is used to also describe the physical interruption of pain either chemically, thermally, or surgically All neurolytic techniques cause Wallerian degeneration of the nerve axon distal to the lesion. -
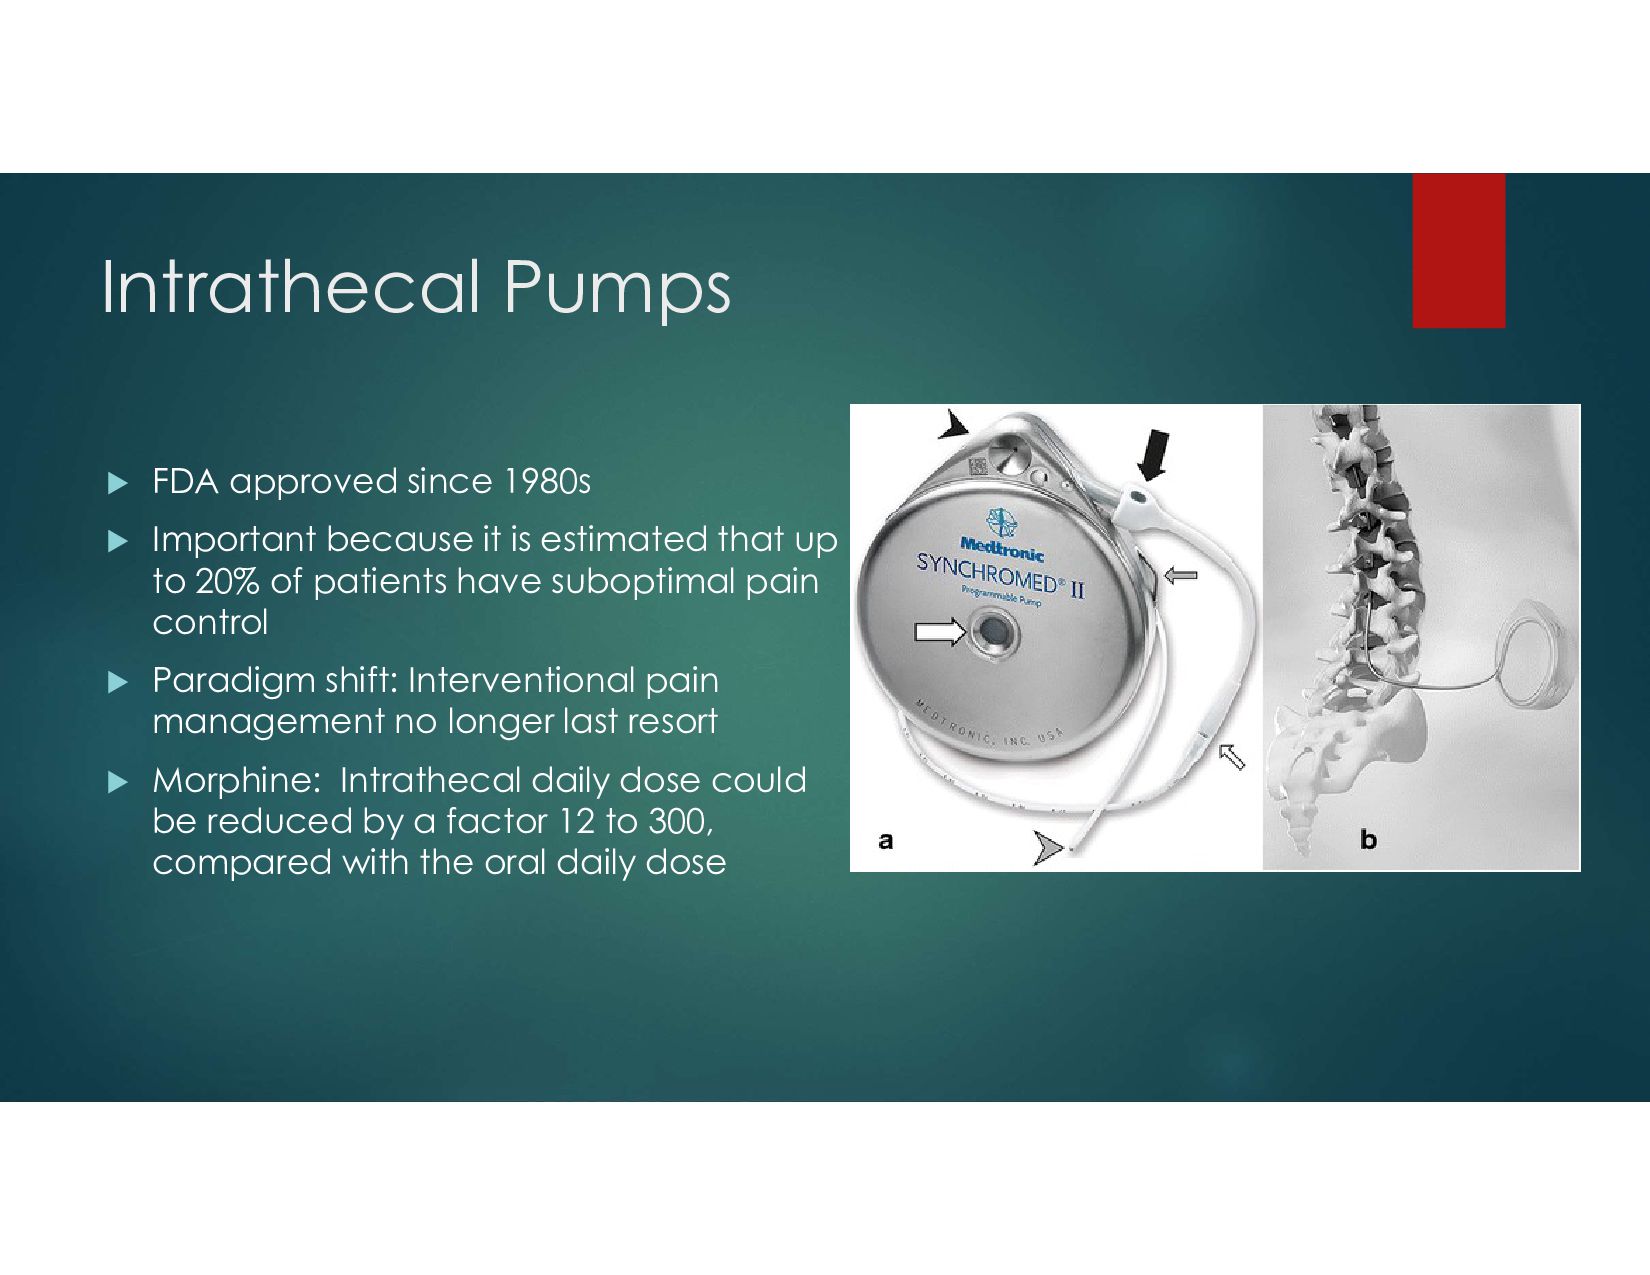
Intrathecal Pumps FDA approved since 1980s Important because
it is estimated that up to 20% of patients have suboptimal pain control Paradigm shift: Interventional pain management no longer last resort Morphine: Intrathecal daily dose could be reduced by a factor 12 to 300, compared with the oral daily dose -
Intrathecal Pumps Intrathecal pumps deliver small doses of medication
directly to the spinal fluid It consists of a small battery-powered, programmable pump that is implanted under the subcutaneous tissue of the abdomen and connected to a small catheter tunneled to the site of spinal entry Sophisticated drug dose regimens can be instituted Implanted pumps need to be refilled every 1 to 3 months There is no evidence showing whether it is more clinically effective to use bolus or continuous dosing. -
Intrathecal Pumps Benefits: Fixed continuous rate of infusion
with bolus option for breakthrough pain Lower doses of drug generally produce fewer adverse effects sedation, cognitive deficits, fatigue, and constipation Intrathecal drug administration can provide more effective analgesia than systemically administered Early implementation may lead to improved survival (Smith, T.J. et al. 2002. Journal of Clinical Oncology) Minimize divergence of medications -
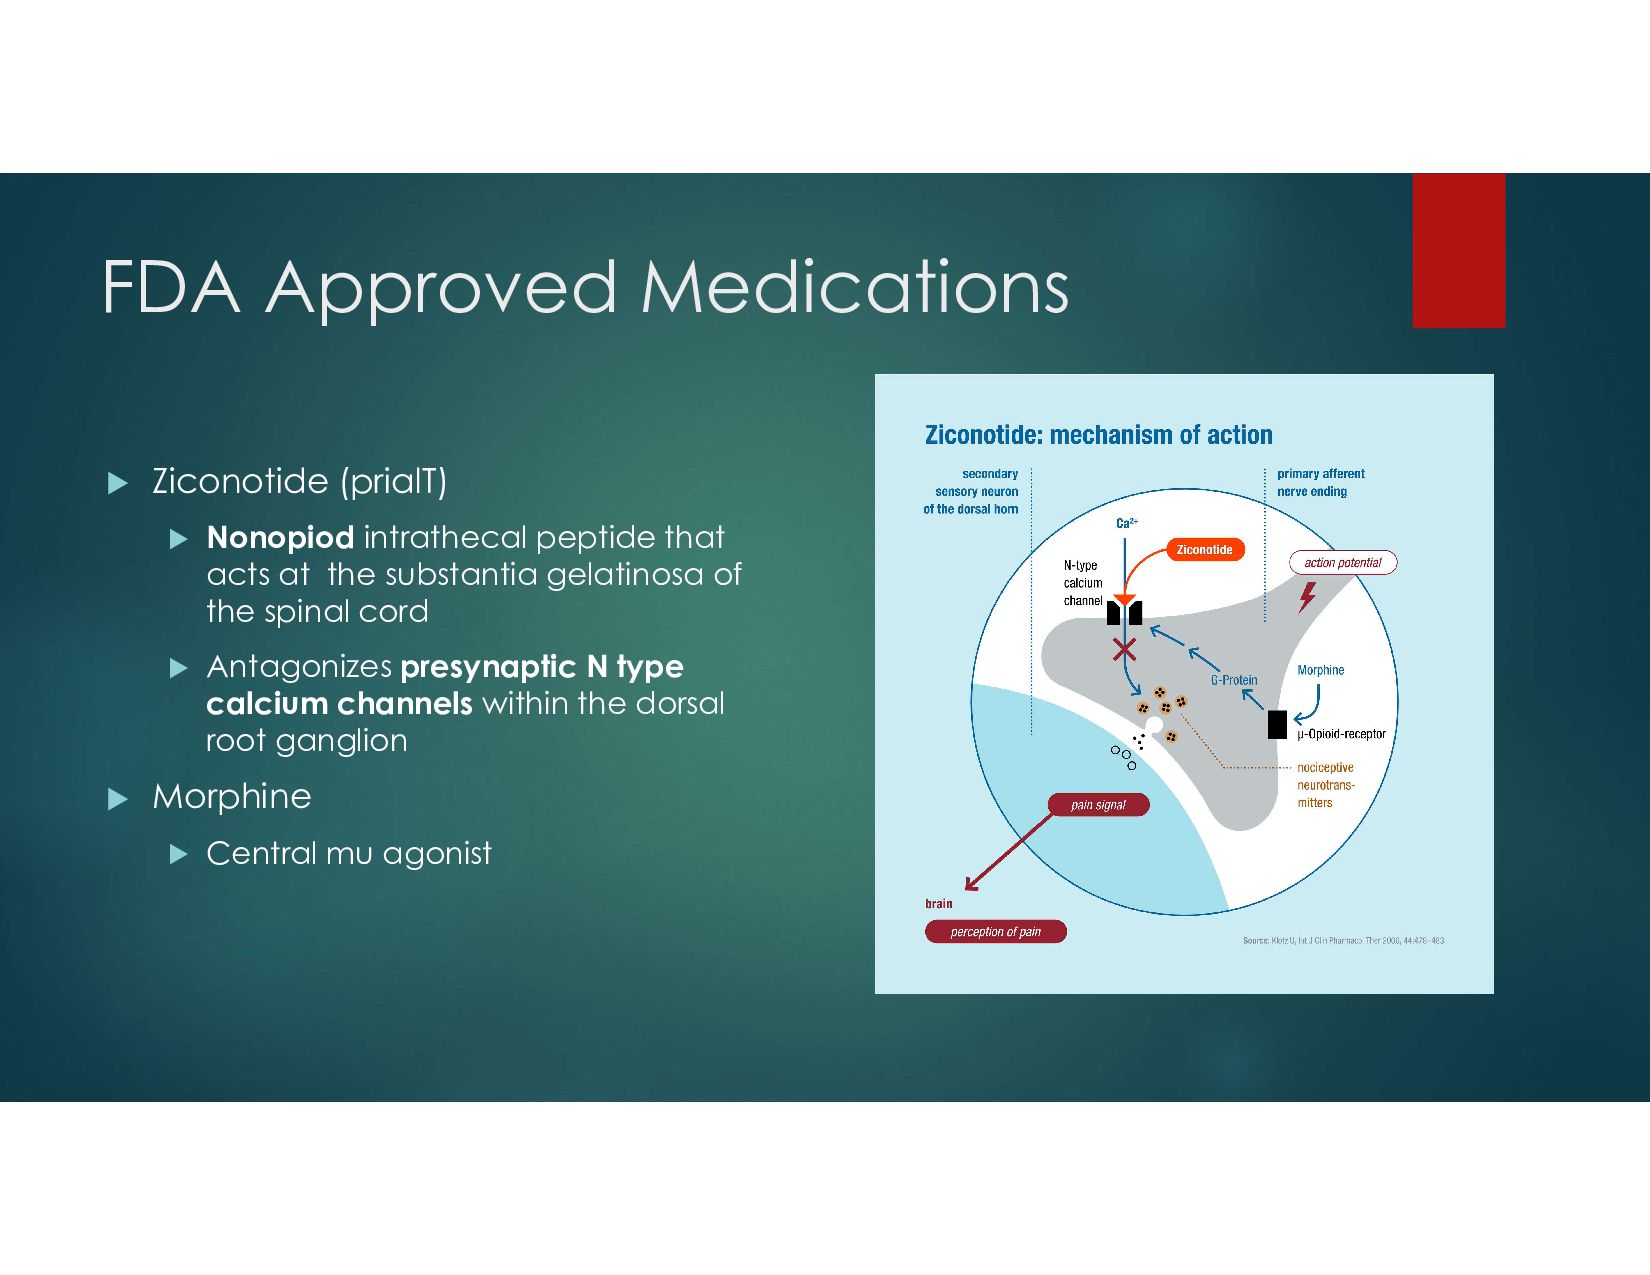
FDA Approved Medications Ziconotide (prialT) Nonopiod intrathecal peptide
that acts at the substantia gelatinosa of the spinal cord Antagonizes presynaptic N type calcium channels within the dorsal root ganglion Morphine Central mu agonist -
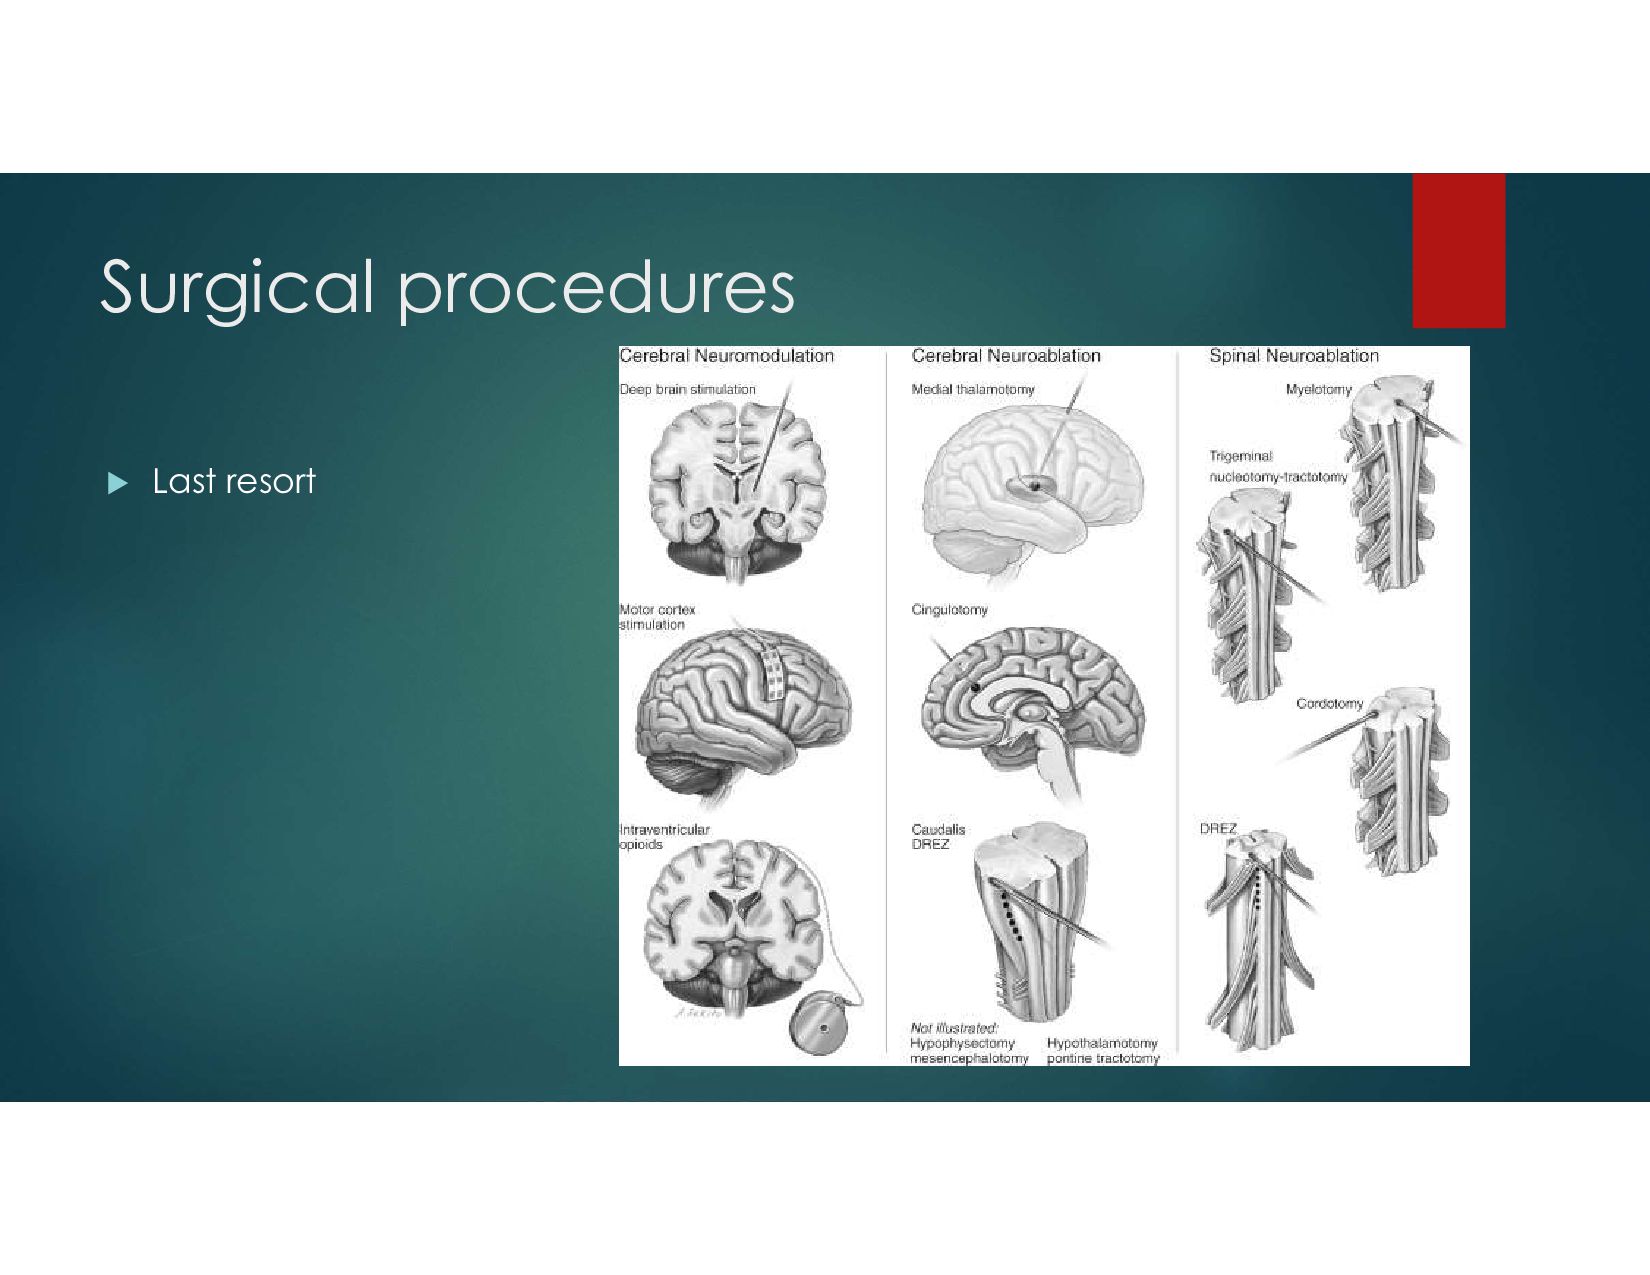
Sympathectomy Indication: visceral pain of cancer How: RF
or chemical ablation at sympathetic chains or ganglia Has been largely replaced by SCS -
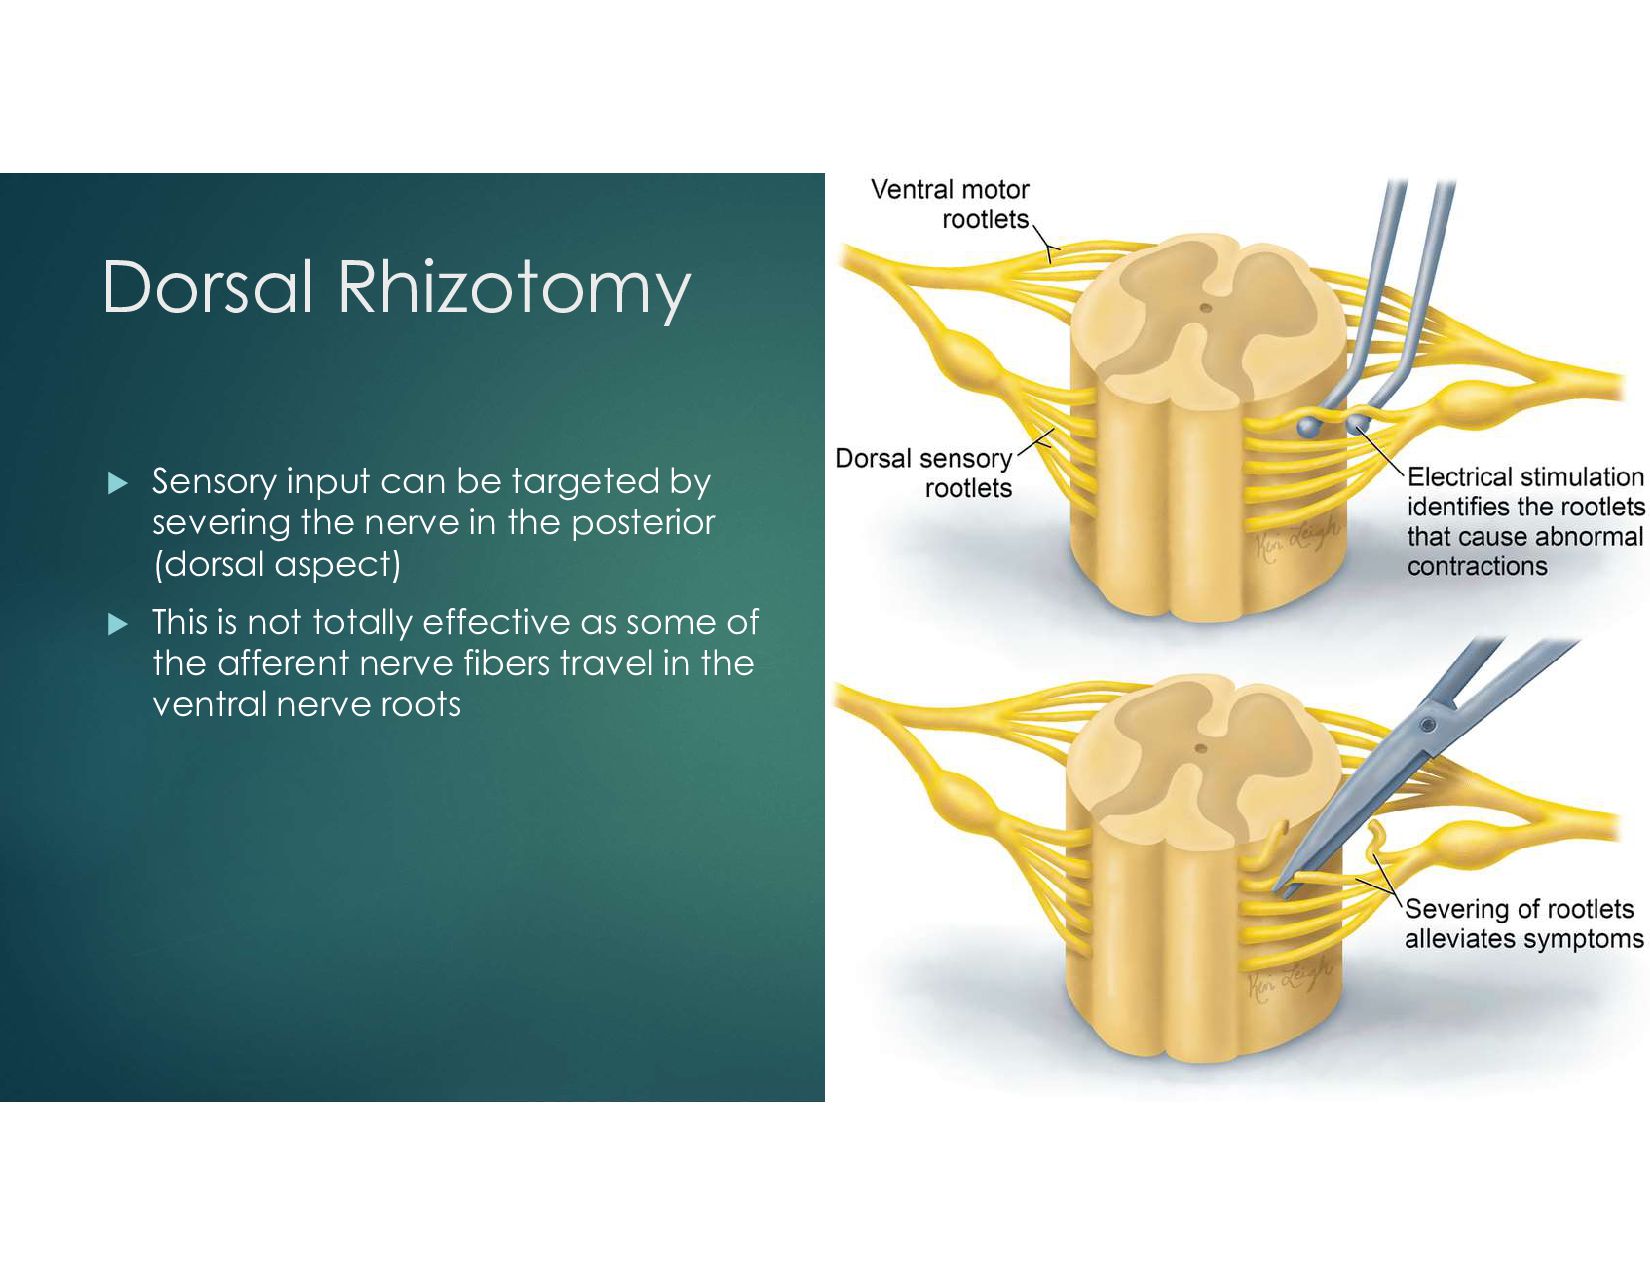
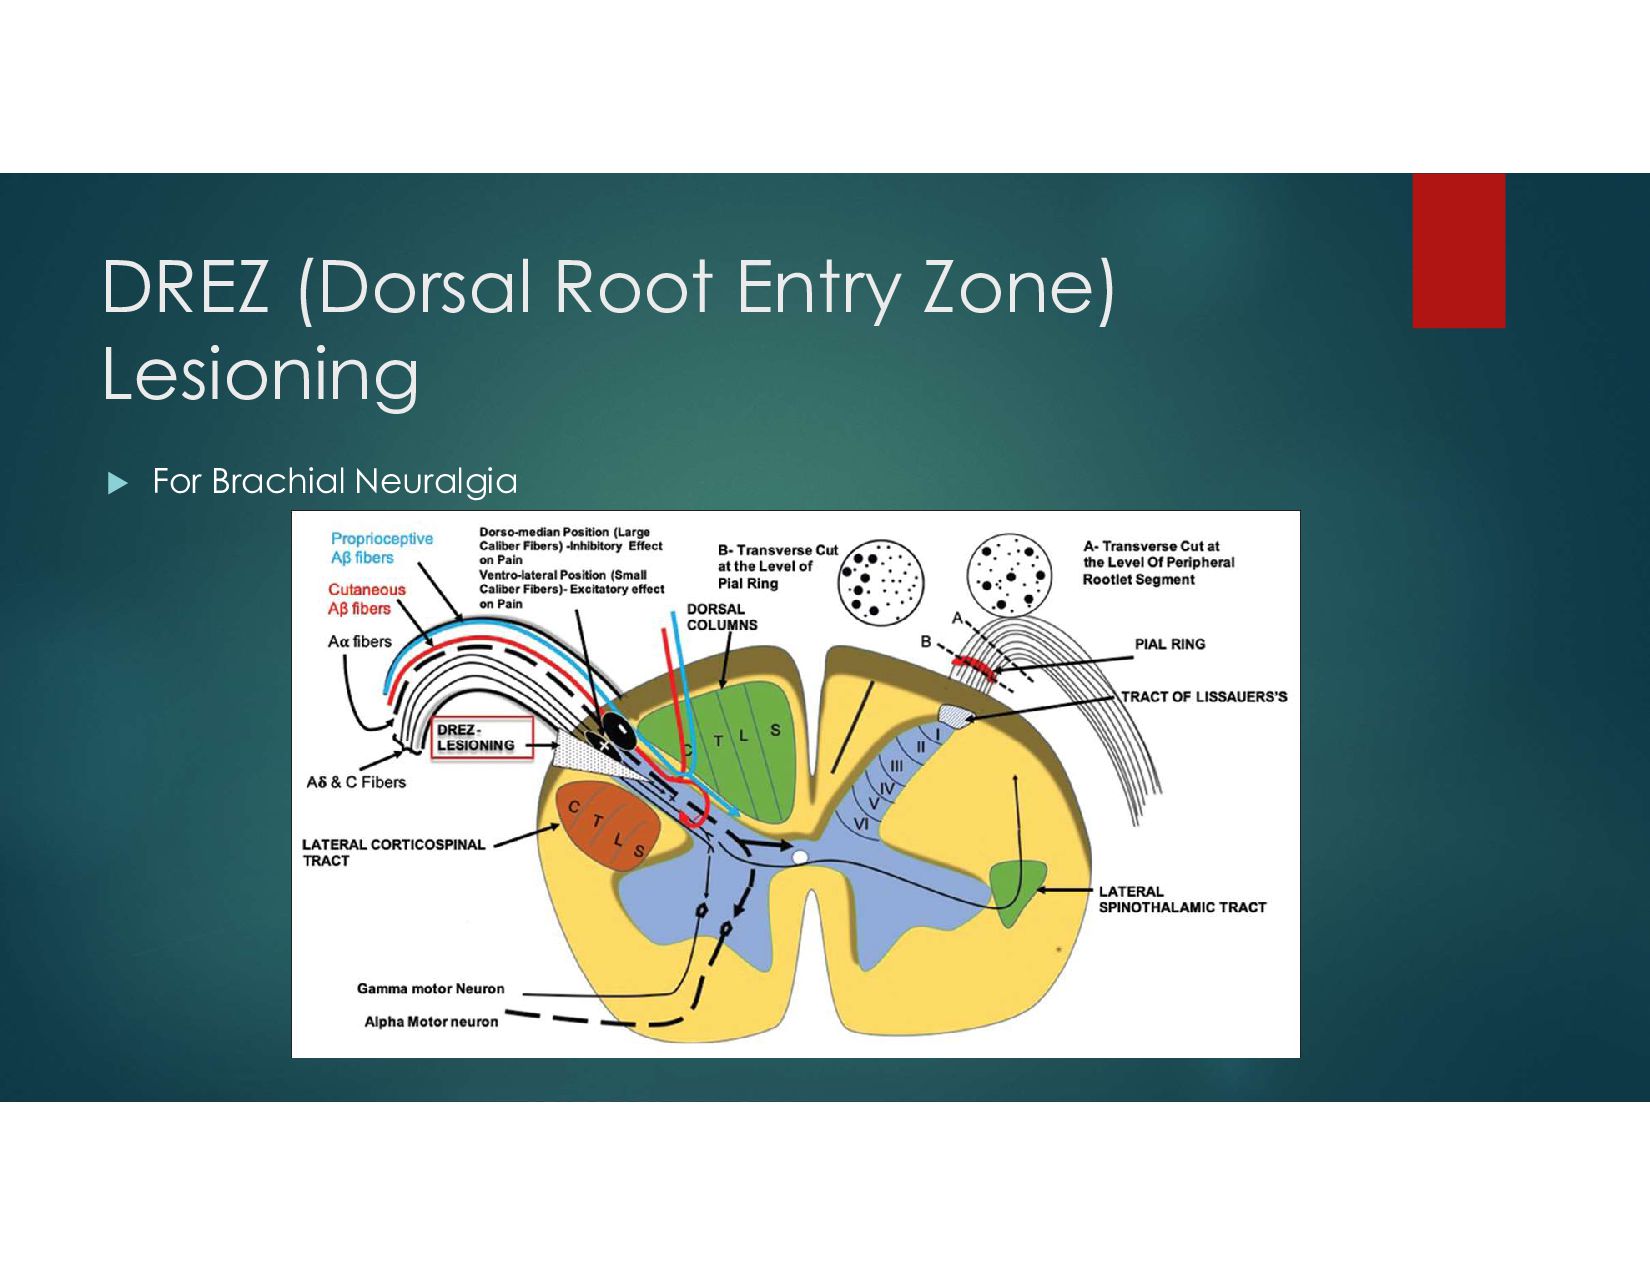
Dorsal Rhizotomy Sensory input can be targeted by severing
the nerve in the posterior (dorsal aspect) This is not totally effective as some of the afferent nerve fibers travel in the ventral nerve roots -
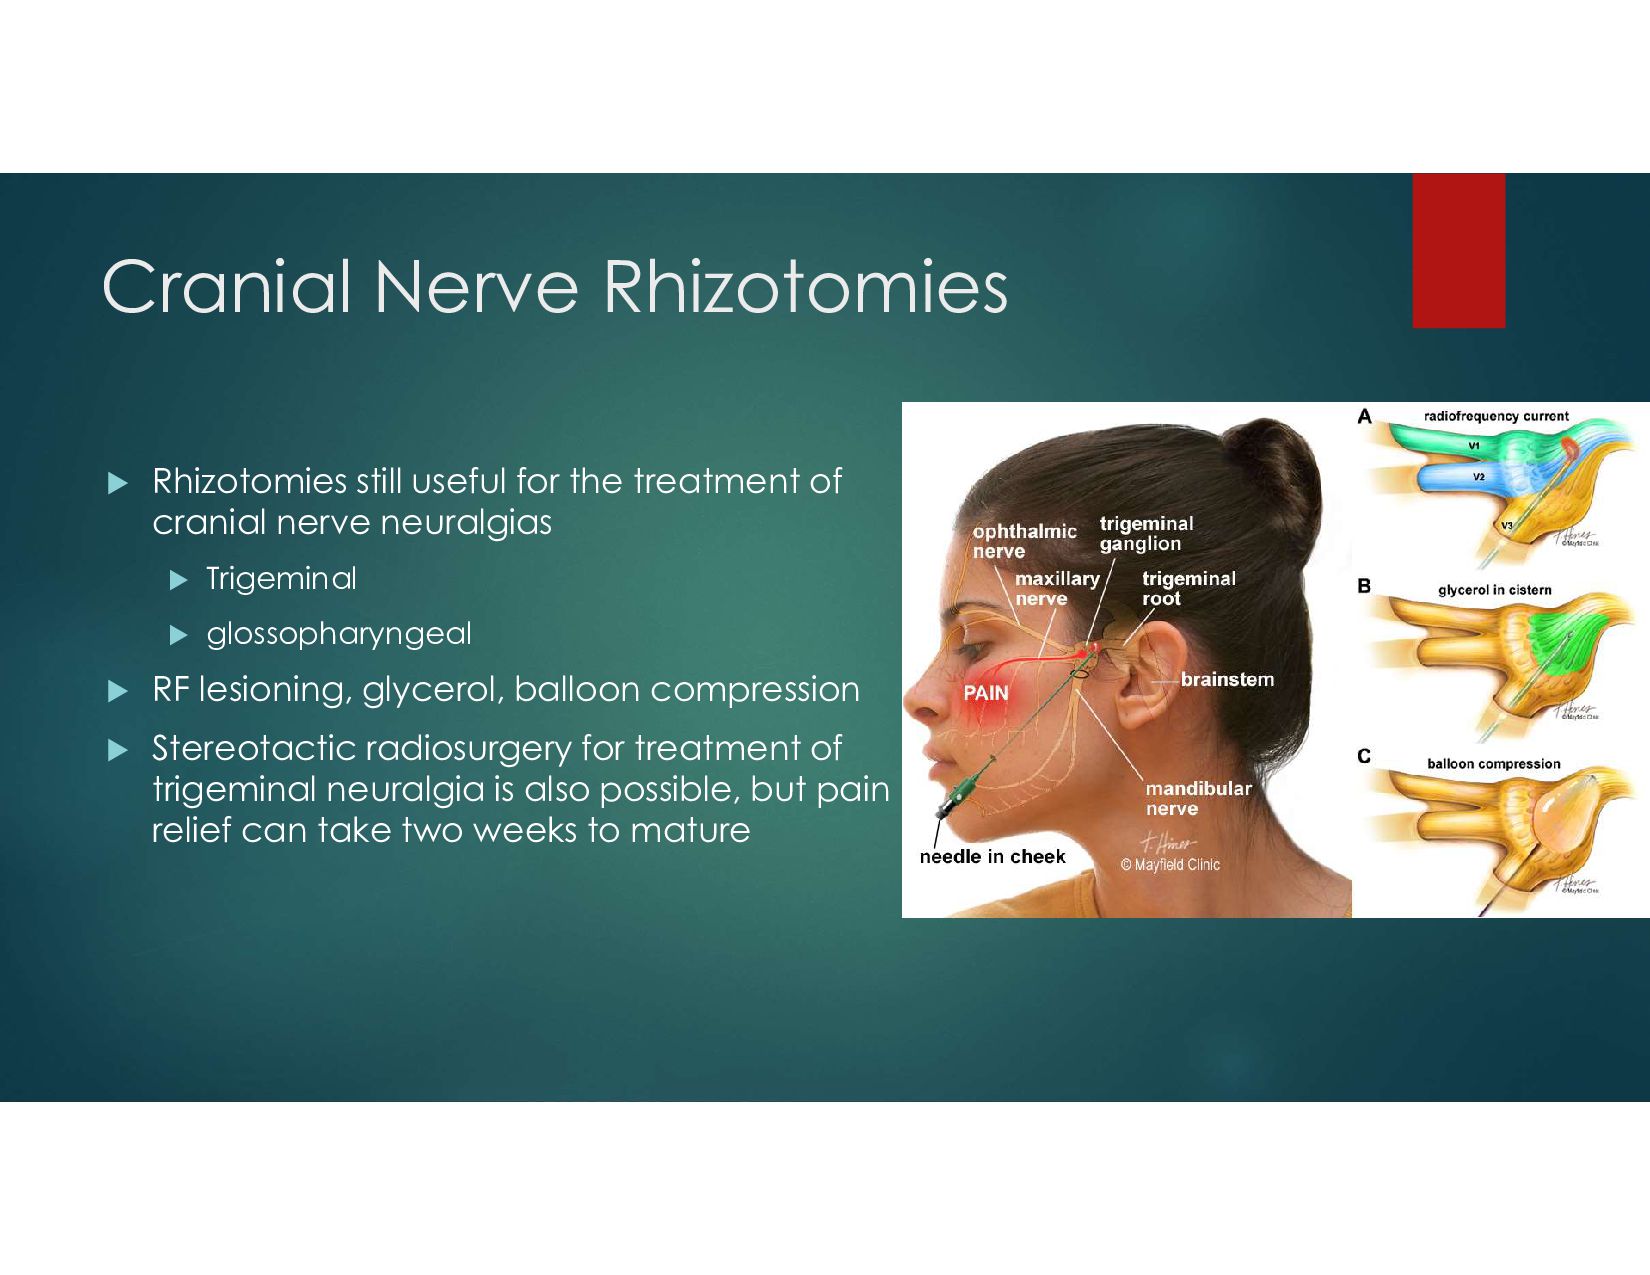
Cranial Nerve Rhizotomies Rhizotomies still useful for the treatment
of cranial nerve neuralgias Trigeminal glossopharyngeal RF lesioning, glycerol, balloon compression Stereotactic radiosurgery for treatment of trigeminal neuralgia is also possible, but pain relief can take two weeks to mature -
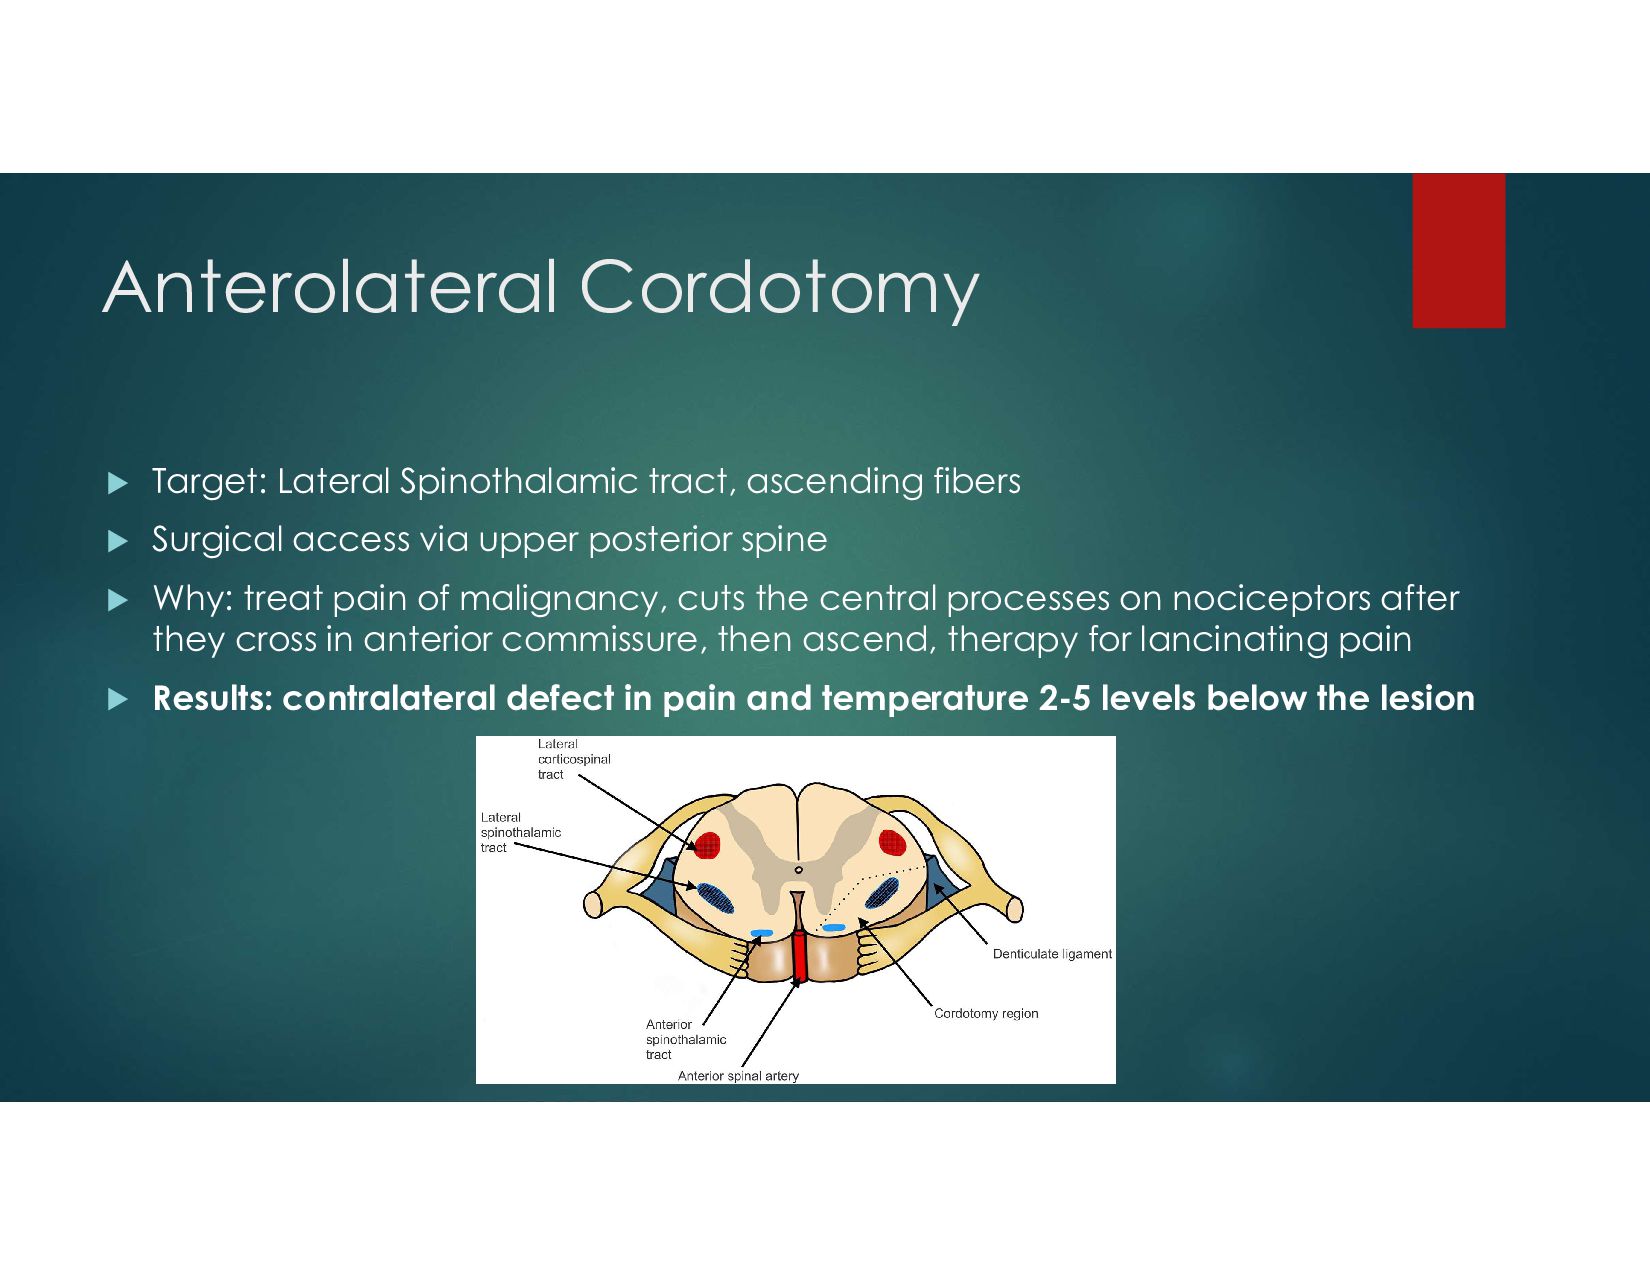
Anterolateral Cordotomy Target: Lateral Spinothalamic tract, ascending fibers
Surgical access via upper posterior spine Why: treat pain of malignancy, cuts the central processes on nociceptors after they cross in anterior commissure, then ascend, therapy for lancinating pain Results: contralateral defect in pain and temperature 2-5 levels below the lesion -
Cingulotomy Why- target “affective” components of pain, essentially a
lobotomy procedure that was perfected by Freeman and Watts RF lesions of bilateral anterior cingulate gyrus Indicated for intractable pain of malignant origin “Psychosurgery” May be used for OCD
 us414
 adeputra13
 cbtlibrary
 akiraasano
 2720japanoke
 kentaroy47
 aisw77
 sonakv
 pawan_pharm
 michielstock
 chrisshort
 leimatthew05
 ryanjones
 quramy
 lara
 reverentgeek
 greggifford
 palkan
 codingconduct
 jonrohan
 aleyda